
Bottom line
Vasopressin (argipressin) is an An entry with substantial scientific visibility or identity value. Biological rationale and non-human evidence do not establish patient benefit. Definition source: Scope and selection methodology · Glossary cyclic nonapeptide and a globally approved pharmaceutical indicated for vasodilatory shock (post-cardiotomy, septic) and central diabetes insipidus. It is a designated ISMP high-alert medication with risks including cardiac ischaemia, hyponatraemia, and tissue necrosis from extravasation. It is distinct from its synthetic analogue desmopressin (which is V2-selective). No boxed warning, but multiple serious warnings.
Identity and composition
| Field | Verified information |
|---|---|
| Preferred name | Vasopressin (INN: argipressin) |
| Key aliases | Arginine vasopressin (AVP), antidiuretic hormone (ADH), Pitressin, Vasostrict, argipressin |
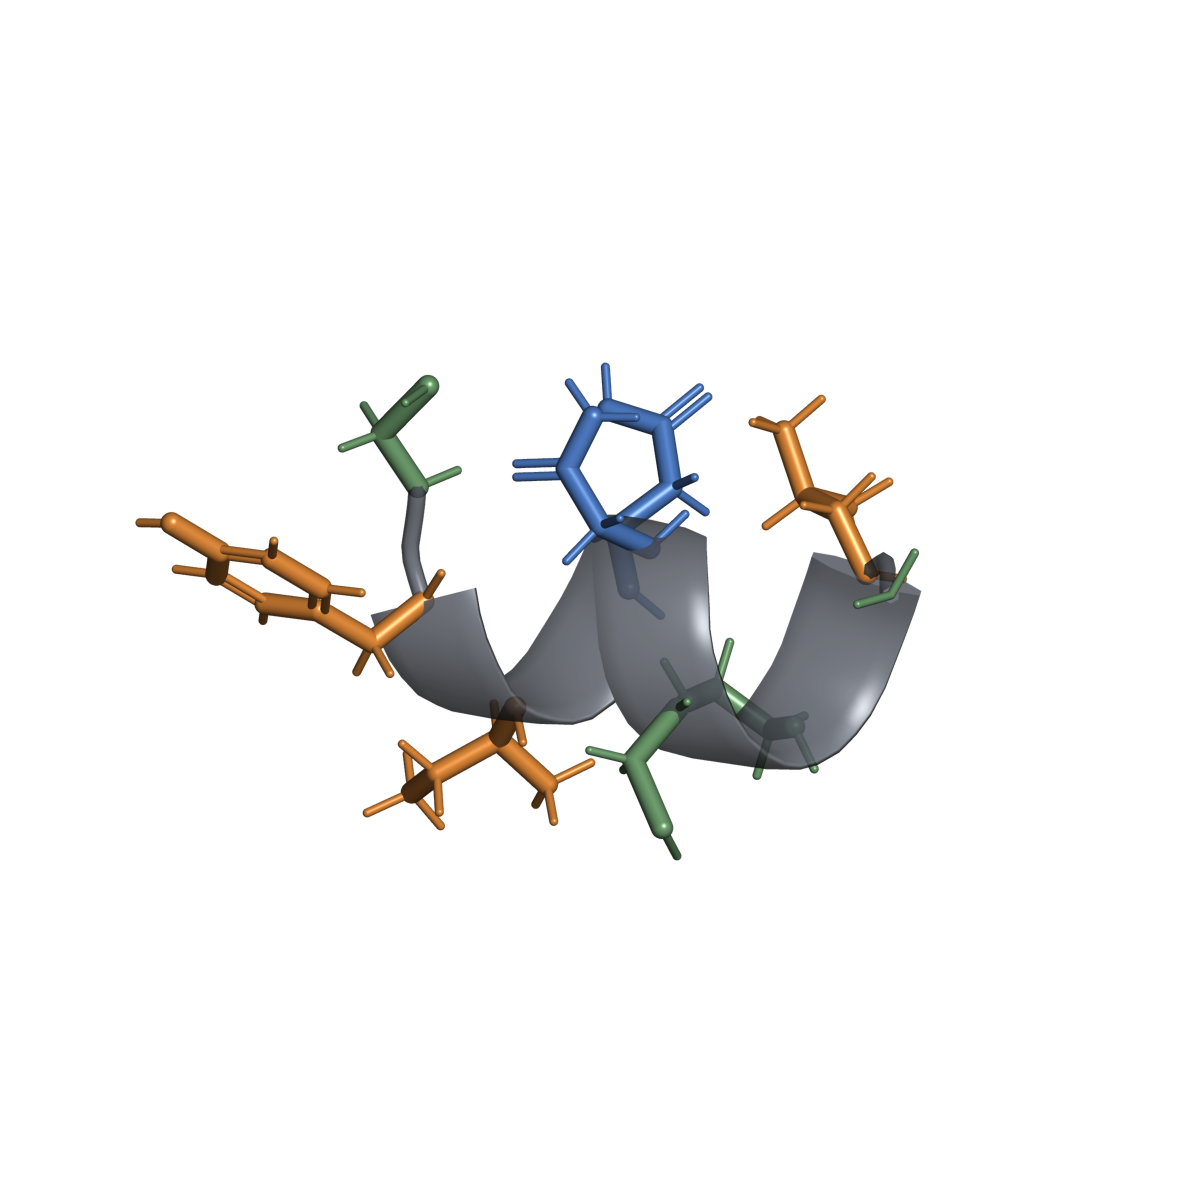
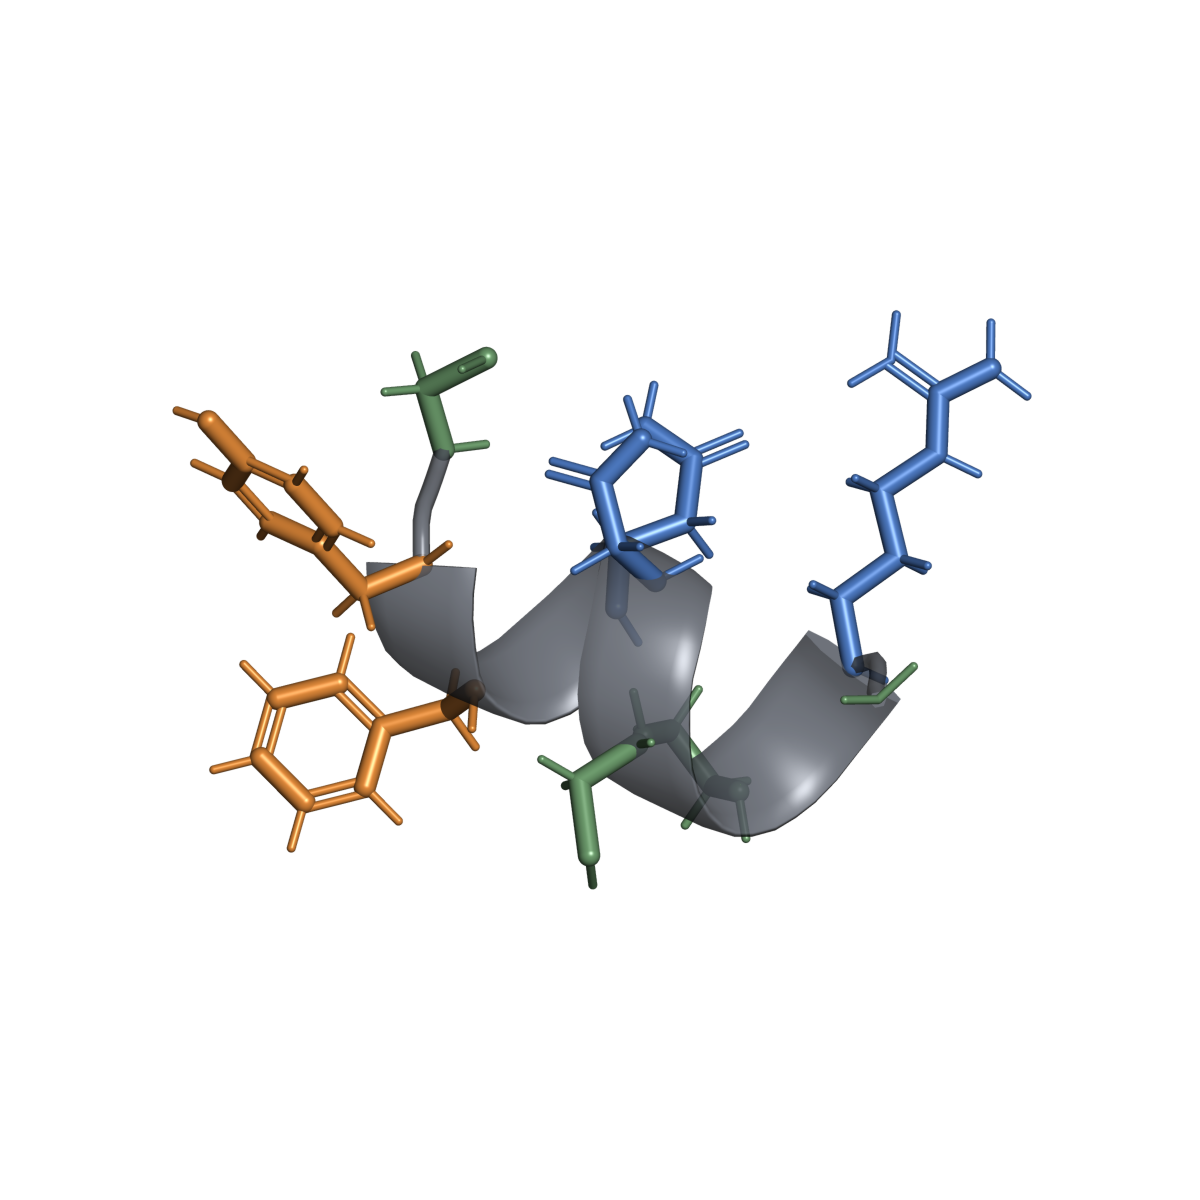
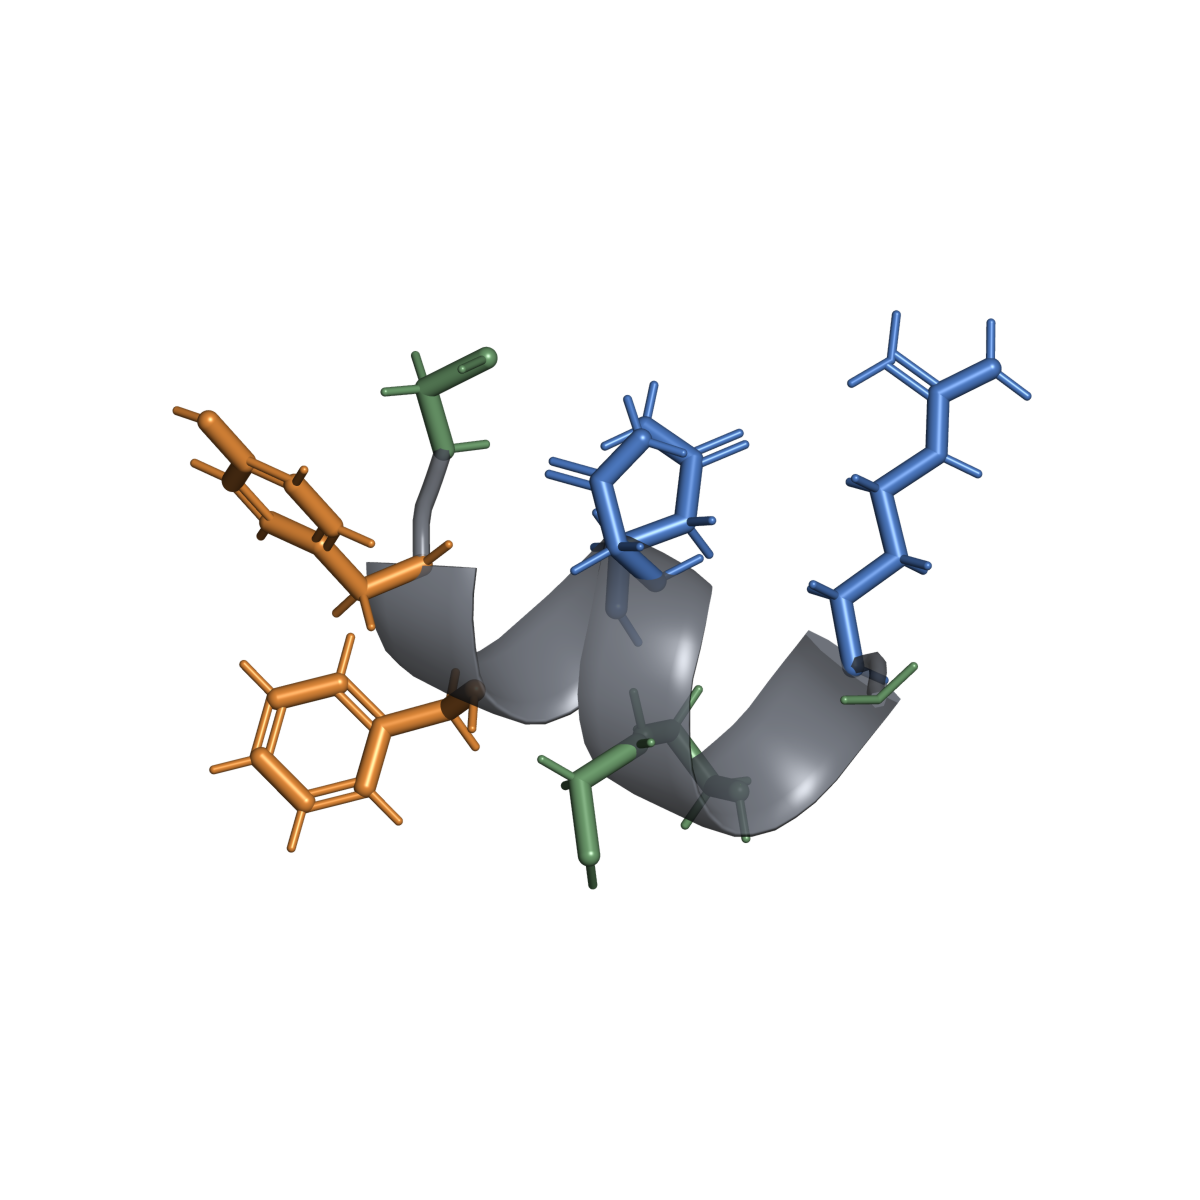
| Molecular/sequence identity | Cys-Tyr-Phe-Gln-Asn-Cys-Pro-Arg-Gly-NH₂ (cyclic nonapeptide; disulfide bridge Cys¹–Cys⁶) |
| Modifications/form | C-terminal amide; disulfide bridge between residues 1 and 6 |
| Stable identifiers | CAS 11000-17-2 (pharmaceutical); 113-79-1 (base); The record number of a compound in PubChem, the atlas's primary structure-asset source. A registry record or depiction does not authenticate a commercial sample. Definition source: Identity and structure assets methodology · Glossary 644077; DrugBank DB00067; UNII Y4907O6MFD; ATC H01BA01; ChEBI CHEBI:34543 |
| Identity caveats | An entry with substantial scientific visibility or identity value. Biological rationale and non-human evidence do not establish patient benefit. Definition source: Scope and selection methodology · Glossary human ADH — identical to mammalian arginine vasopressin; differs from oxytocin at positions 3 (Phe vs Ile) and 8 (Arg vs Leu); lysine vasopressin (lypressin) occurs in pigs and is a different INN |
Development and approval status
| Jurisdiction | Status and indication | Product/source | As of |
|---|---|---|---|
| FDA (US) | Approved — vasodilatory shock (post-cardiotomy, septic) | Vasostrict (Par Pharmaceutical, NDA 204485) | 2014 |
| FDA (US) | Approved — central diabetes insipidus, postoperative abdominal distention | Pitressin (pre-1938, DESI) | Grandfathered |
| EMA/UK | Approved — central diabetes insipidus, oesophageal varices bleeding | Argipressin (generic) | Approved |
| WHO | Listed — Essential Medicine | Various | Current |
- UNITED STATES
- FDA (US): Approved — vasodilatory shock (post-cardiotomy, septic); FDA (US): Approved — central diabetes insipidus, postoperative abdominal distention
- EU/EEA
- EMA/UK: Approved — central diabetes insipidus, oesophageal varices bleeding
- UNITED KINGDOM
- No UNITED KINGDOM row is present in the source status table
- OTHER DOCUMENTED
- WHO: Listed — Essential Medicine
Sport status: WADA: not prohibited
Mechanism and pharmacology
Vasopressin is an An entry with substantial scientific visibility or identity value. Biological rationale and non-human evidence do not establish patient benefit. Definition source: Scope and selection methodology · Glossary agonist at three GPCR subtypes:
V1a (vascular smooth muscle): Gq/PLC/IP₃ → Ca²⁺ release → vasoconstriction (basis of vasopressor indication)
V2 (renal collecting duct principal cells): Gs/AC/cAMP/PKA → aquaporin-2 insertion → water reabsorption (basis of antidiuretic effect)
V1b/V3 (anterior pituitary corticotrophs): potentiates CRH-driven ACTH release
Vasopressin preserves vasopressor effect when adrenergic receptors are desensitised (sepsis, post-cardiotomy). Mechanism is well-characterised — high confidence.
Evidence by claim
| Claim/indication | Stage | Grade | Best human evidence | Main result | Important limitations |
|---|---|---|---|---|---|
| Vasodilatory shock (septic, post-cardiotomy) | Approved (FDA) | A | FDA label literature synthesis of 7 septic-shock and 8 post-cardiotomy-shock studies | Label identifies vasopressin as vasopressor adjunct in vasodilatory shock | Literature-based approval (505(b)(2) pathway); FDA label, NDA 204485 |
| Vasodilatory shock (septic) | Approved (FDA) | A | VASST (Russell 2008): superiority trial, N=779, septic shock | 28-day mortality 35.4% vs 39.3% (P=0.26) — not significant; post-hoc benefit in less severe shock | Primary endpoint not met; does not establish noninferiority; PMID 18305265 |
| Vasodilatory shock (septic) | Approved (FDA) | A | VANISH (Gordon 2016) | No mortality benefit over norepinephrine | Did not reduce kidney failure days; PMID 27483065 |
| Central diabetes insipidus | Approved (DESI) | A | Pre-FDA-era data | Effective for antidiuresis | No modern pivotal trials; grandfathered |
- AGrade A: Established for a specific labeled use
- BGrade B: Moderate human evidence
- CGrade C: Preliminary human evidence
- DGrade D: Preclinical only
- EGrade E: Anecdotal/marketing claim
- XGrade X: Evidence contradicts or does not support the claim
Text alternative for the claim-evidence diagram. Each grade is defined below:
- A — Established for a specific labeled use
- 4 claims: Vasodilatory shock (septic, post-cardiotomy); Vasodilatory shock (septic); Vasodilatory shock (septic); Central diabetes insipidus
- B — Moderate human evidence
- 0 claims
- C — Preliminary human evidence
- 0 claims
- D — Preclinical only
- 0 claims
- E — Anecdotal/marketing claim
- 0 claims
- X — Evidence contradicts or does not support the claim
- 0 claims
Key studies
| Study | Design/population | Exposure studied | Endpoints and result | Limitations |
|---|---|---|---|---|
| Russell et al. 2008 (VASST) | A study in which participants are assigned to the study material or a comparator by chance. Definition source: Neutral gloss; usage context: Evidence grading methodology · Glossary septic shock (n=779); superiority design | Vasopressin 0.01–0.03 U/min vs norepinephrine | 28-day mortality 35.4% vs 39.3% (P=0.26) — primary endpoint not significant; post-hoc benefit in less severe shock | Did not establish noninferiority; post-hoc subgroup; PMID 18305265 |
| Gordon et al. 2016 (VANISH) | RCT septic shock (n≈400) | Early vasopressin vs norepinephrine | No difference in kidney failure-free days | A study in which participants and investigators know what is administered. Definition source: Neutral gloss; usage context: Evidence grading methodology · Glossary; PMID 27483065 |
| Treschan & Peters 2006 | Physiology review | — | Comprehensive AVP physiology and clinical strategies | Review; PMID 16931995 |
Dose and administration evidence
Approved labeled regimen
The label summary below is product-, indication-, and jurisdiction-specific; consult the full current label and a licensed clinician/pharmacist.
FDA-approved regimens (Vasostrict):
Vasodilatory shock: Administered into a vein. Definition source: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossary infusion 0.01–0.03 U/min (label cites literature synthesis of 7 septic-shock and 8 post-cardiotomy-shock studies)
Titrate in 0.005 U/min increments; taper after 8 hours MAP stability without catecholamines
Central diabetes insipidus (Pitressin): Administered into a muscle. Definition source: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossary/Administered into the tissue layer under the skin. Definition source: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossary 5–10 U, 2–3 times daily
Studied regimens (not recommendations)
VASST trial: 0.01–0.03 U/min. VANISH: 0–0.06 U/min titrated per MAP.
What is not established
Optimal dosing for septic shock (ongoing trials)
Role of early vs late vasopressin in sepsis algorithms
Long-term safety in chronic use (diabetes insipidus dosing is well-established)
Safety
Established label risks
No boxed warning but multiple major warnings:
Cardiac: Decreased cardiac output, bradycardia, tachyarrhythmias — monitor haemodynamics
Ischaemia: Coronary, mesenteric, skin/digital ischaemia — extravasation carries risk of tissue necrosis/gangrene
Hyponatraemia: V2-mediated free-water retention — monitor serum sodium
Anaphylaxis: Rare but reported (anaphylactic shock, cardiac arrest)
High-alert medication (ISMP designation): significant patient harm risk with use error
Contraindications: Hypersensitivity to vasopressin or chlorobutanol (preservative in some formulations).
Human-study signals
VASST and VANISH established the safety profile in septic shock. No unexpected toxicity signals at studied doses.
Unknowns and product-quality risks
Paediatric safety data limited for vasodilatory shock indication
Mechanism of nephrogenic diabetes insipidus after AVP withdrawal not well understood
Research chemical vasopressin products completely unacceptable for any therapeutic use
Interactions and special populations
Potentiated by ganglionic blocking drugs and carbamazepine
Attenuated by lithium, demeclocycline, heparin, alcohol
Caution in cardiovascular disease (ischaemic risk)
Pregnancy category: no adequate well-controlled studies; use only if clearly needed
Paediatric: safety and efficacy not established in vasodilatory shock
Regulatory, compounding, and sport notes
The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. Definition source: WADA and sport regulation brief · Glossary: not prohibited
US DEA: not scheduled
The reviewed US vasopressin products are prescription medicines; scheduling and access must be checked for the specific product and jurisdiction
FDA approval of a branded product does not by itself determine whether a particular compounded preparation satisfies sections Sections of the US Food, Drug, and Cosmetic Act covering traditional compounding exemptions (503A) and outsourcing-facility compounding (503B). Under 503A, qualification conditions include a patient-specific prescription requirement; under 503B, conditions cover facility registration and bulk-substance eligibility. Definition source: United States regulation brief · Glossary or 503B
Differentiated from desmopressin (V2-selective synthetic analogue)
Evidence gaps
Vasodilatory shock indication approved via 505(b)(2) pathway (literature-based)
Optimal dosing for septic shock remains debated
Paediatric safety data limited
Nephrogenic diabetes insipidus after AVP withdrawal mechanism unclear
Search notes
Databases and registries: PubMed, DailyMed, Drugs@FDA, WHO EML, ISMP
Search terms: Vasopressin, argipressin, Vasostrict, Pitressin, VASST, VANISH, 644077, DB00067
Last searched: 2026-08-06
Inclusion emphasis: regulatory labels, large A study in which participants are assigned to the study material or a comparator by chance. Definition source: Neutral gloss; usage context: Evidence grading methodology · Glossary, systematic reviews
Sources
FDA label: Vasostrict (vasopressin injection). NDA 204485. https://www.accessdata.fda.gov/drugsatfda_docs/label/2021/204485Orig1s017lbl.pdf
Russell JA et al. (2008) N Engl J Med. VASST. PMID 18305265
Gordon AC et al. (2016) JAMA. VANISH. PMID 27483065
DrugBank DB00067. https://go.drugbank.com/drugs/DB00067
PubChem CID 644077. https://pubchem.ncbi.nlm.nih.gov/compound/644077
ISMP. High-Alert Medications in Acute Care Settings. Institute for Safe Medication Practices. https://www.ismp.org/recommendations/high-alert-medications-acute-list