
Bottom line
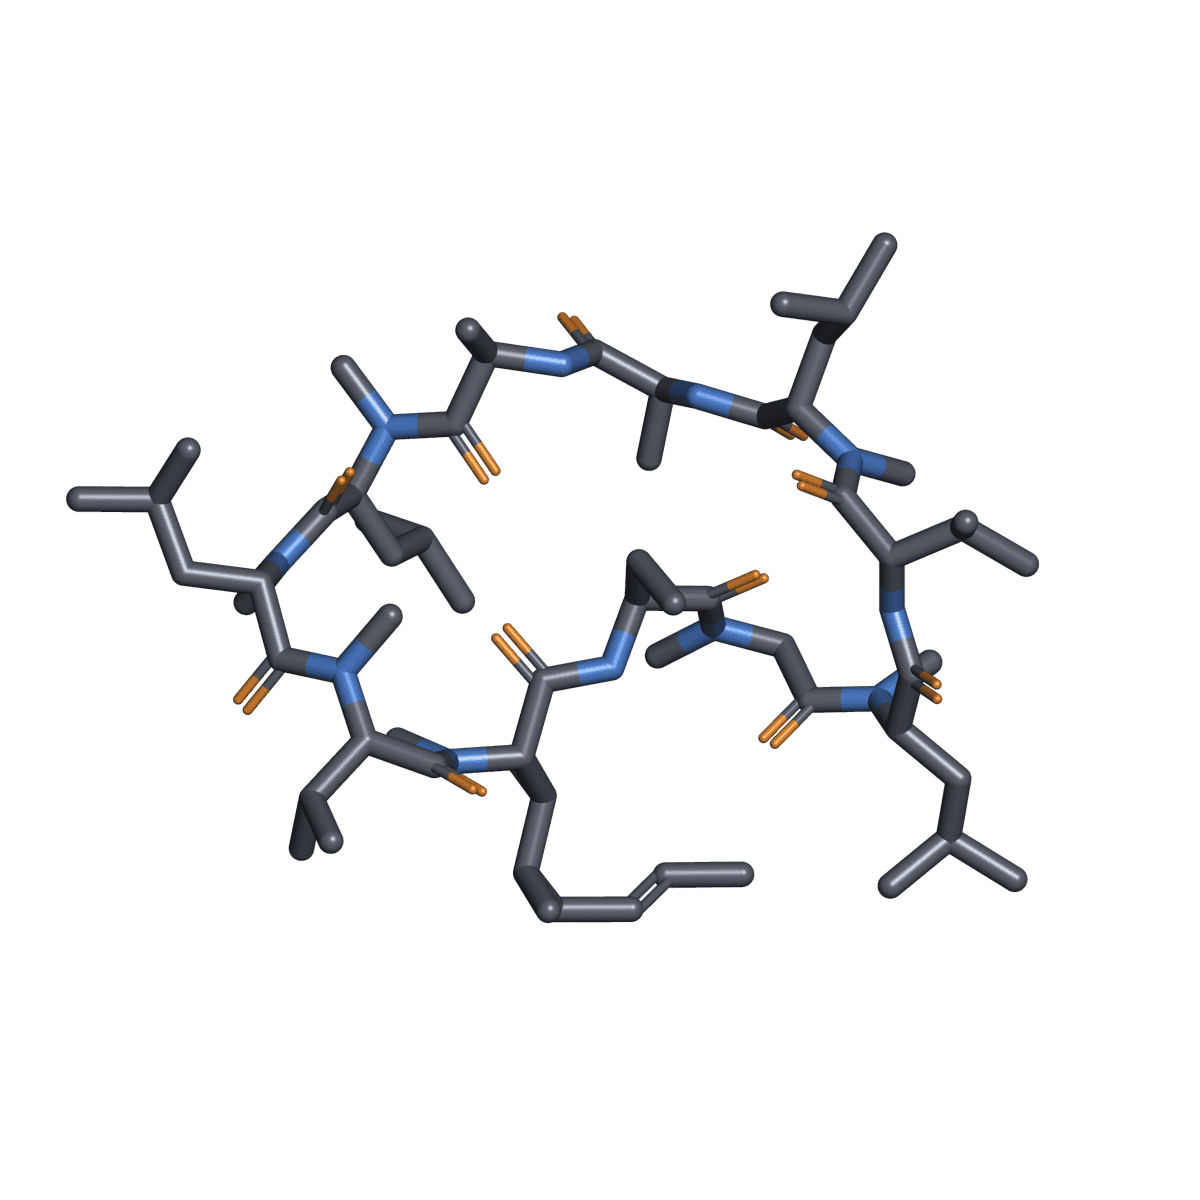
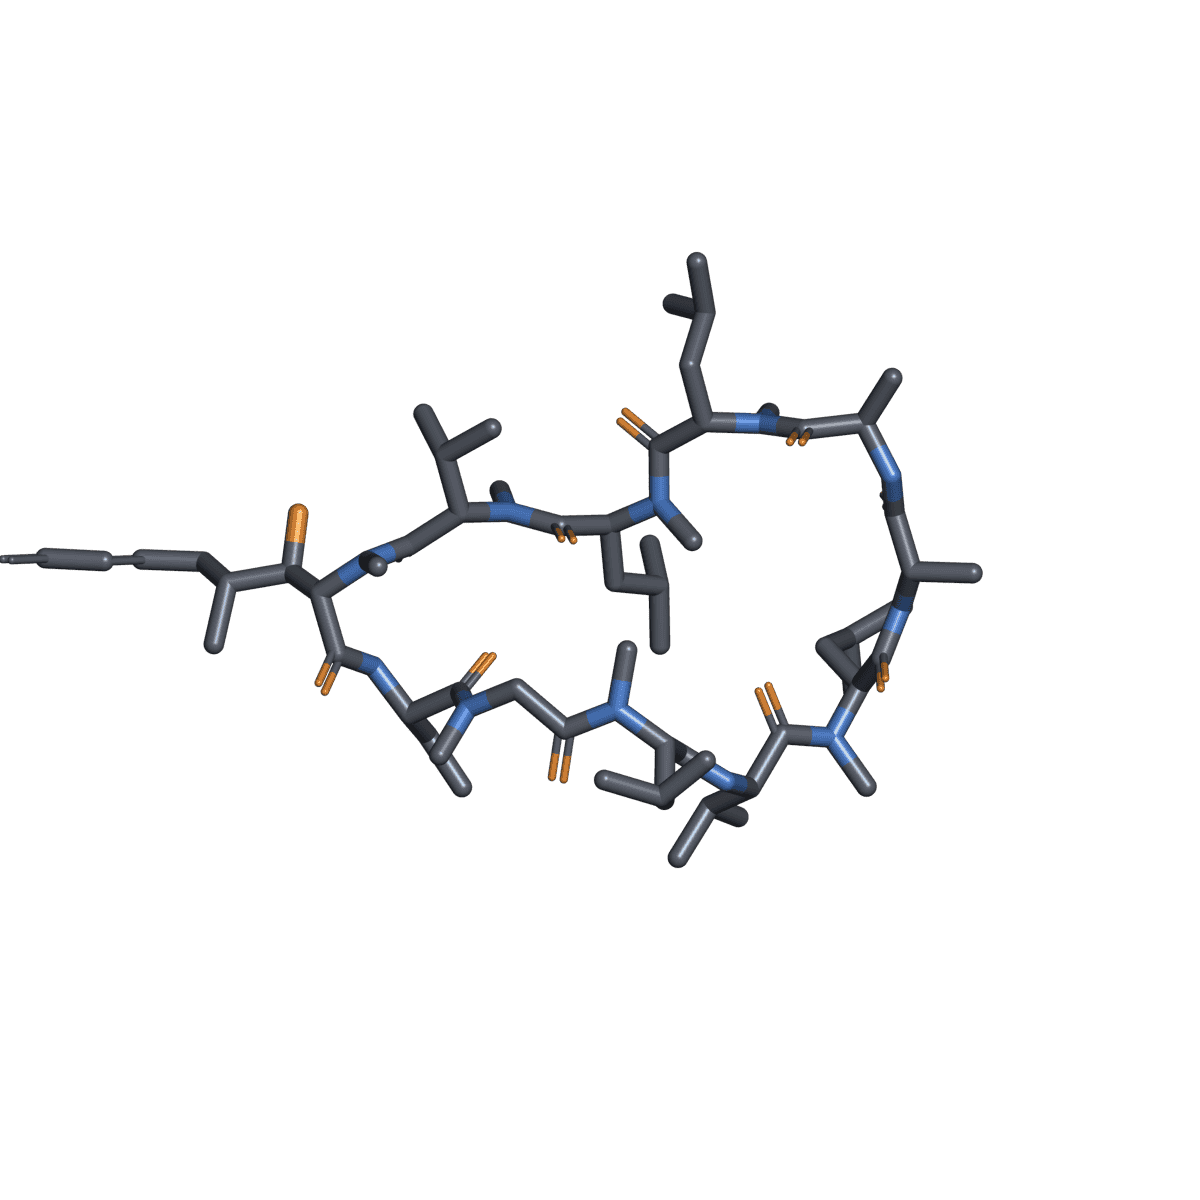
Voclosporin is a synthetic analog of cyclosporine A modified at the amino acid-1 residue (the MeBmt position). It is a homodetic cyclic peptide and a calcineurin inhibitor. FDA-approved in January 2021 (Lupkynis) for the treatment of active lupus nephritis in combination with mycophenolate mofetil and corticosteroids. A pivotal phase 3 trial (AURORA-1) demonstrated superior renal response rates compared to standard of care. Unlike cyclosporine, voclosporin does not require therapeutic drug monitoring.
Identity and composition
| Field | Verified information |
|---|---|
| Preferred name | Voclosporin |
| Key aliases | Lupkynis, ISA-247, ISATX247 |
| Molecular/sequence identity | Cyclic peptide of 11 amino acids; cyclosporine A analog modified at amino acid-1 residue (MeBmt side chain modification); molecular formula C63H111N11O12 |
| Modifications/form | Homodetic cyclic peptide; MW 1214.6 g/mol |
| Stable identifiers | CAS 515814-01-4; The record number of a compound in PubChem, the atlas's primary structure-asset source. A registry record or depiction does not authenticate a commercial sample. 定義の出典: Identity and structure assets methodology · 用語集 6918486; DrugBank DB11919; UNII 2PN063X6B1 |
| Identity caveats | Structurally distinct from cyclosporine A by a single functional-group modification on the MeBmt residue |
Development and approval status
| Jurisdiction | Status and indication | Product/source | As of |
|---|---|---|---|
| US (FDA) | Active lupus nephritis (with MMF and corticosteroids) | Lupkynis (23.7 mg capsules) | Jan 2021 |
| EU (EMA) | Active lupus nephritis (with MMF) | Lupkynis | 15 Sep 2022 |
- UNITED STATES
- US (FDA): Active lupus nephritis (with MMF and corticosteroids)
- EU/EEA
- EU (EMA): Active lupus nephritis (with MMF)
- UNITED KINGDOM
- No UNITED KINGDOM row is present in the source status table
- OTHER DOCUMENTED
- No OTHER DOCUMENTED row is present in the source status table
Sport status: WADA: voclosporin was not identified by exact name in the 2026 Prohibited List, and this review did not identify a matching prohibited class. An unsupported assumption about performance effect is not a basis for classification; athletes should verify the exact product and current status.
Mechanism and pharmacology
Voclosporin binds to cyclophilin A; the complex inhibits calcineurin, blocking IL-2 expression and T-cell-mediated immune responses. It also stabilizes podocytes in the kidney. The single amino-acid modification vs cyclosporine A alters binding affinity to calcineurin, leading to a more predictable How a substance is absorbed, distributed, metabolized, and eliminated by the body; atlas pages report pharmacokinetic data such as half-life, metabolism, and clearance. 定義の出典: Neutral gloss; usage context: Routes, devices, and absorption primer · 用語集 profile and no requirement for therapeutic drug monitoring.
Evidence by claim
| Claim/indication | Stage | Grade | Best human evidence | Main result | Important limitations |
|---|---|---|---|---|---|
| Active lupus nephritis (with MMF) | Approved | A | Phase 3 AURORA-1 (N=357) | Renal response at 52 weeks: 40.8% vs 22.5% (OR 2.65, p less than 0.001) | Excluded severe renal impairment; 52-week follow-up |
- AグレードA: 特定の表示使用に対して確立
- BグレードB: 中等度のヒトエビデンス
- CグレードC: 予備的ヒトエビデンス
- DグレードD: 前臨床のみ
- EグレードE: 逸話的/マーケティング主張
- XグレードX: エビデンスが主張と矛盾するか、支持しない
Text alternative for the claim-evidence diagram. Each grade is defined below:
- A — Established for a specific labeled use
- 1 claim: Active lupus nephritis (with MMF)
- B — Moderate human evidence
- 0 claims
- C — Preliminary human evidence
- 0 claims
- D — Preclinical only
- 0 claims
- E — Anecdotal/marketing claim
- 0 claims
- X — Evidence contradicts or does not support the claim
- 0 claims
Key studies
| Study | Design/population | Exposure studied | Endpoints and result | Limitations |
|---|---|---|---|---|
| AURORA-1 (NCT03021499) | Phase 3, DBPC, N=357, active LN | Voclosporin 23.7 mg BID + MMF 2 g/day + rapidly tapered corticosteroids vs An inactive comparator used in a controlled study. 定義の出典: Neutral gloss; usage context: Evidence grading methodology · 用語集 + MMF + steroids | Renal response (UPCR ≤0.5 mg/mg, eGFR ≥60 mL/min or no decrease >20%, no rescue therapy) at 52 weeks: 40.8% vs 22.5% | 52-week data; long-term renal survival not assessed |
| AURA-LV (NCT02141672) | Phase 2, DBPC, N=265, active LN | Voclosporin low-dose (23.7 mg BID) and high-dose (39.5 mg BID) vs placebo | Complete renal response at 24 weeks: 32.6% low-dose vs 19.3% placebo | Dose-ranging, short duration |
Dose and administration evidence
Approved labeled regimen
The label summary below is product-, indication-, and jurisdiction-specific; consult the full current label and a licensed clinician/pharmacist.
23.7 mg (3 capsules of 7.9 mg) orally twice daily (approximately 12 hours apart).
Avoid use if baseline eGFR ≤45 mL/min/1.73 m² unless benefit outweighs risk.
If eGFR drops to 30–44 mL/min/1.73 m² during treatment: reduce dose to 15.8 mg (2 capsules) BID; if no improvement within 4 weeks, discontinue.
If eGFR drops to <30 mL/min/1.73 m²: discontinue voclosporin.
For severe renal impairment at baseline (eGFR 15–29 mL/min/1.73 m²): starting dose of 15.8 mg BID if used; discontinuation rules apply as above.
On empty stomach (1 hour before or 2 hours after a meal).
In combination with mycophenolate mofetil (MMF) and rapidly tapered corticosteroids.
Studied regimens (not recommendations)
High-dose regimen (39.5 mg BID) studied in phase 2 but associated with increased adverse events.
What is not established
Safety and efficacy in combination with cyclophosphamide.
Safety in severe renal impairment (eGFR less than 30 mL/min) or dialysis.
Pediatric use.
Safety
Established label risks
Boxed warning: VOCLOSPORIN is a calcineurin-inhibitor immunosuppressant associated with an increased risk of malignancies, including lymphoma and skin cancer, and an increased susceptibility to serious infections, including opportunistic infections. Use only in the recommended dose and in combination with mycophenolate mofetil and corticosteroids. Only physicians experienced in immunosuppressive therapy and management of lupus nephritis should prescribe.
Nephrotoxicity: eGFR reduction (typically reversible).
Hypertension.
QT prolongation (dose-dependent; ECGs recommended).
Increased risk of infections.
Diarrhea, headache, anemia, cough.
Fetal harm (based on mechanism; adequate contraception required).
Human-study signals
AURORA-1: Serious infections 10.2% vs 9.3% An inactive comparator used in a controlled study. 定義の出典: Neutral gloss; usage context: Evidence grading methodology · 用語集. Malignancies 0.6% vs 0%. Deaths 1.7% vs 1.9%.
Unknowns and product-quality risks
Limited long-term safety data beyond 3 years.
Interactions and special populations
CYP3A4 substrate.
Moderate-strong CYP3A4 inhibitors (including grapefruit): increase voclosporin exposure; contraindicated with strong inhibitors.
CYP3A4 inducers: reduce exposure; avoid.
Pregnancy: based on animal data, may cause fetal harm.
Breastfeeding: not recommended.
Regulatory, compounding, and sport notes
FDA and EMA approved prescription only.
The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. 定義の出典: WADA and sport regulation brief · 用語集: voclosporin was not identified by exact name in the 2026 Prohibited List, and this review did not identify a matching prohibited class. An unsupported assumption about performance effect is not a basis for classification; athletes should verify the exact product and current status.
Not interchangeable with cyclosporine or tacrolimus.
Evidence gaps
Long-term renal survival data.
Comparative effectiveness vs tacrolimus-based regimens.
Safety in sub-Saharan African and Latin American populations with LN.
Search notes
Databases and registries: PubMed, FDA label, ClinicalTrials.gov, DrugBank
Search terms: "voclosporin", "Lupkynis", "ISA-247", "AURORA-1"
Last searched: 2026-08-06
Inclusion emphasis: FDA label, pivotal phase 3 trial
Sources
FDA. Lupkynis (voclosporin) prescribing information. https://www.accessdata.fda.gov/drugsatfda_docs/label/2025/213716s008lbl.pdf
PubChem. Voclosporin (CID 6918486). https://pubchem.ncbi.nlm.nih.gov/compound/6918486
Rovin BH, et al. AURORA-1: Efficacy and safety of voclosporin versus placebo for lupus nephritis. Kidney Int. 2021;99(4):974-984.
DrugBank. Voclosporin (DB11919). https://go.drugbank.com/
World Anti-Doping Agency. 2026 Prohibited List. https://www.wada-ama.org/sites/default/files/2025-09/2026list_en_final_clean_september_2025.pdf