
Bottom line
Octreotide is a synthetic octapeptide somatostatin analog with predominant SSTR2 and SSTR5 affinity. Approved for acromegaly, carcinoid syndrome, and VIPoma diarrhea; additionally supported by the PROMID study for metastatic midgut neuroendocrine tumor (NET) disease control. Long-acting repeatable (LAR) Administered into a muscle. Quelle der Definition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossar depot is the primary maintenance formulation.
Identity and composition
| Field | Verified information |
|---|---|
| Preferred name | Octreotide |
| Key aliases | Sandostatin (Administered into the tissue layer under the skin. Quelle der Definition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossar/Administered into a vein. Quelle der Definition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossar), Sandostatin LAR (Administered into a muscle. Quelle der Definition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossar depot) |
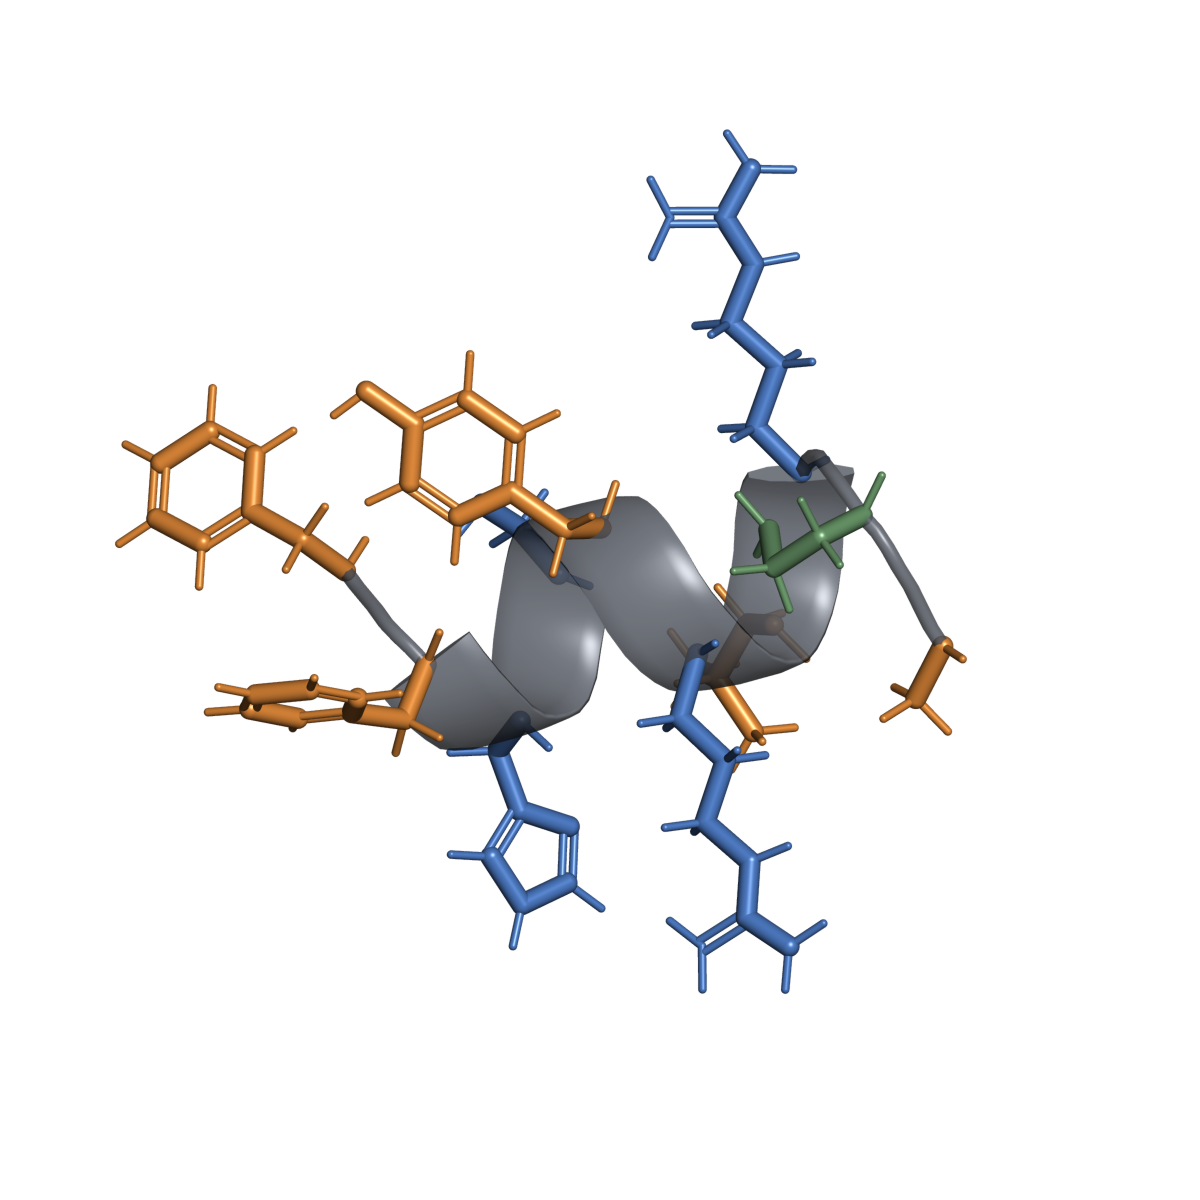
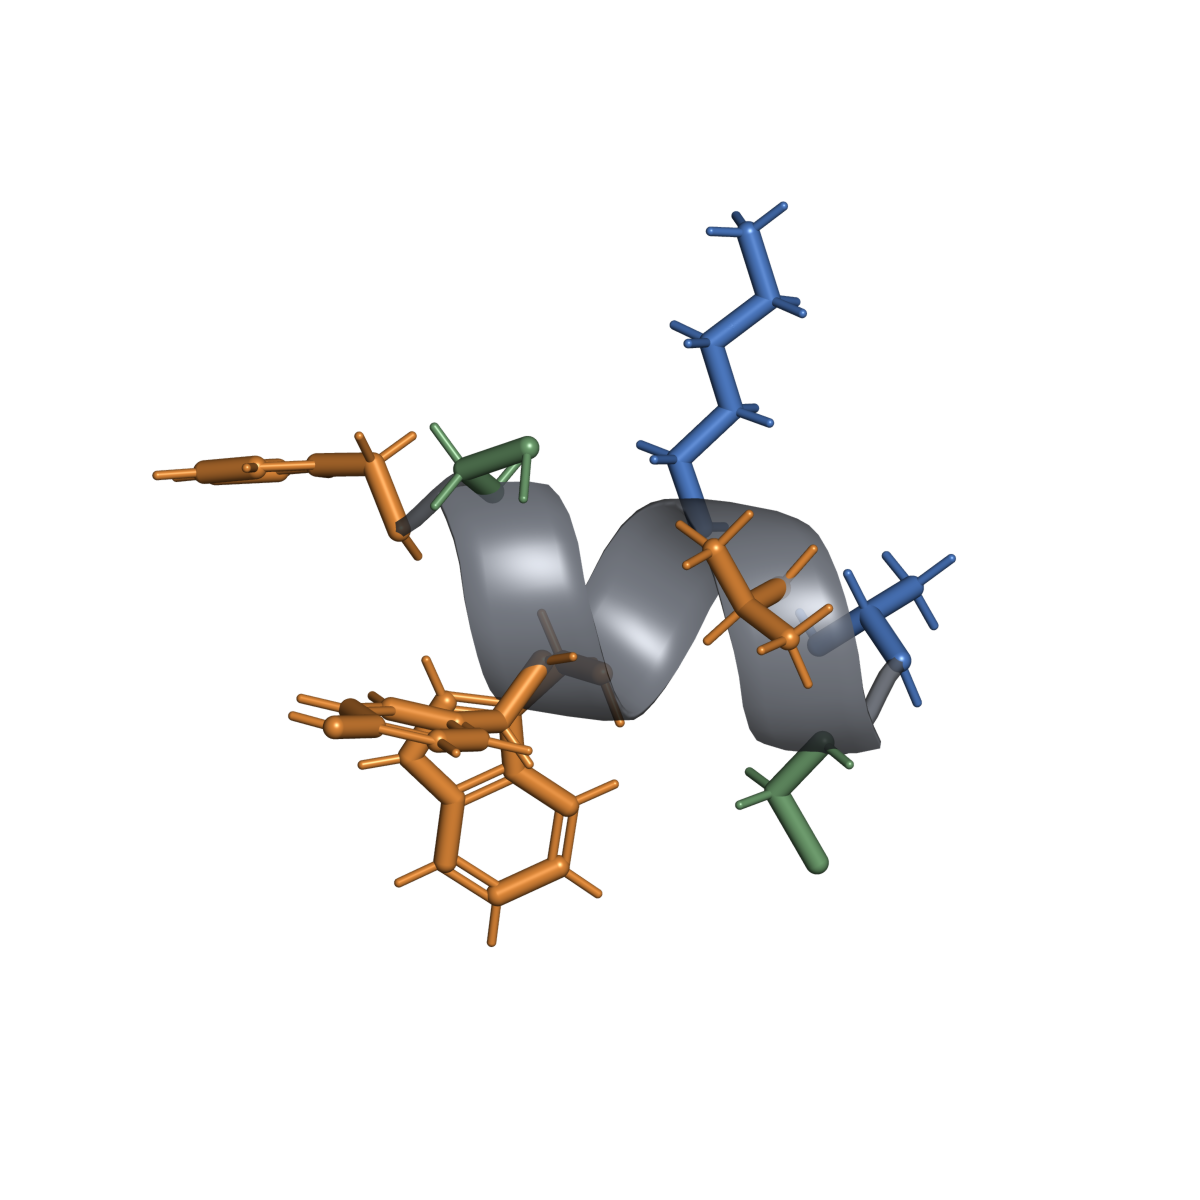
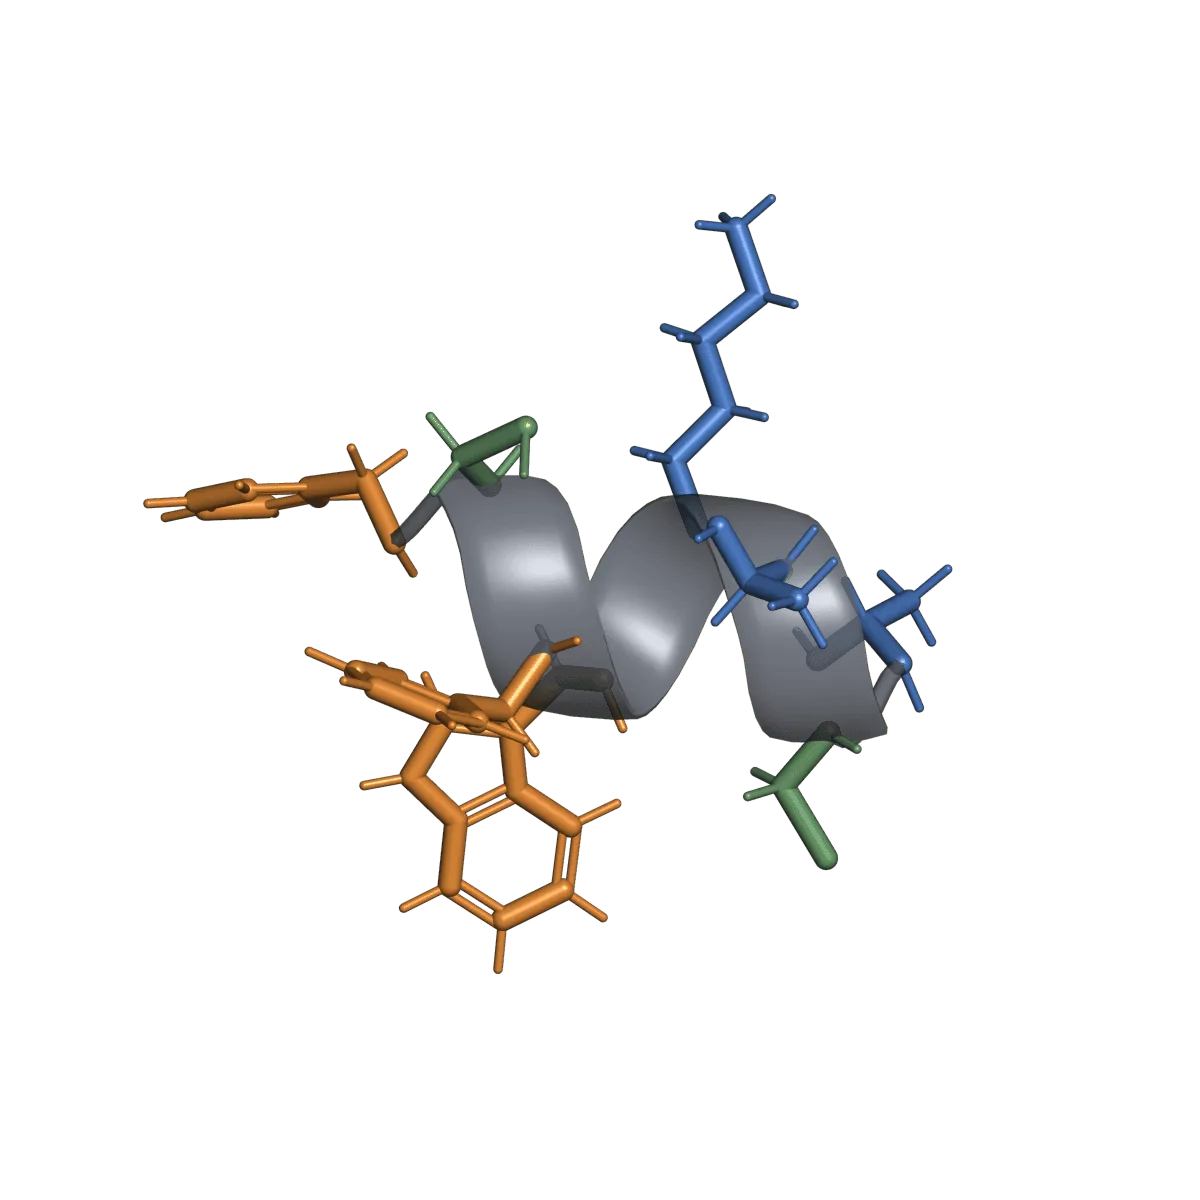
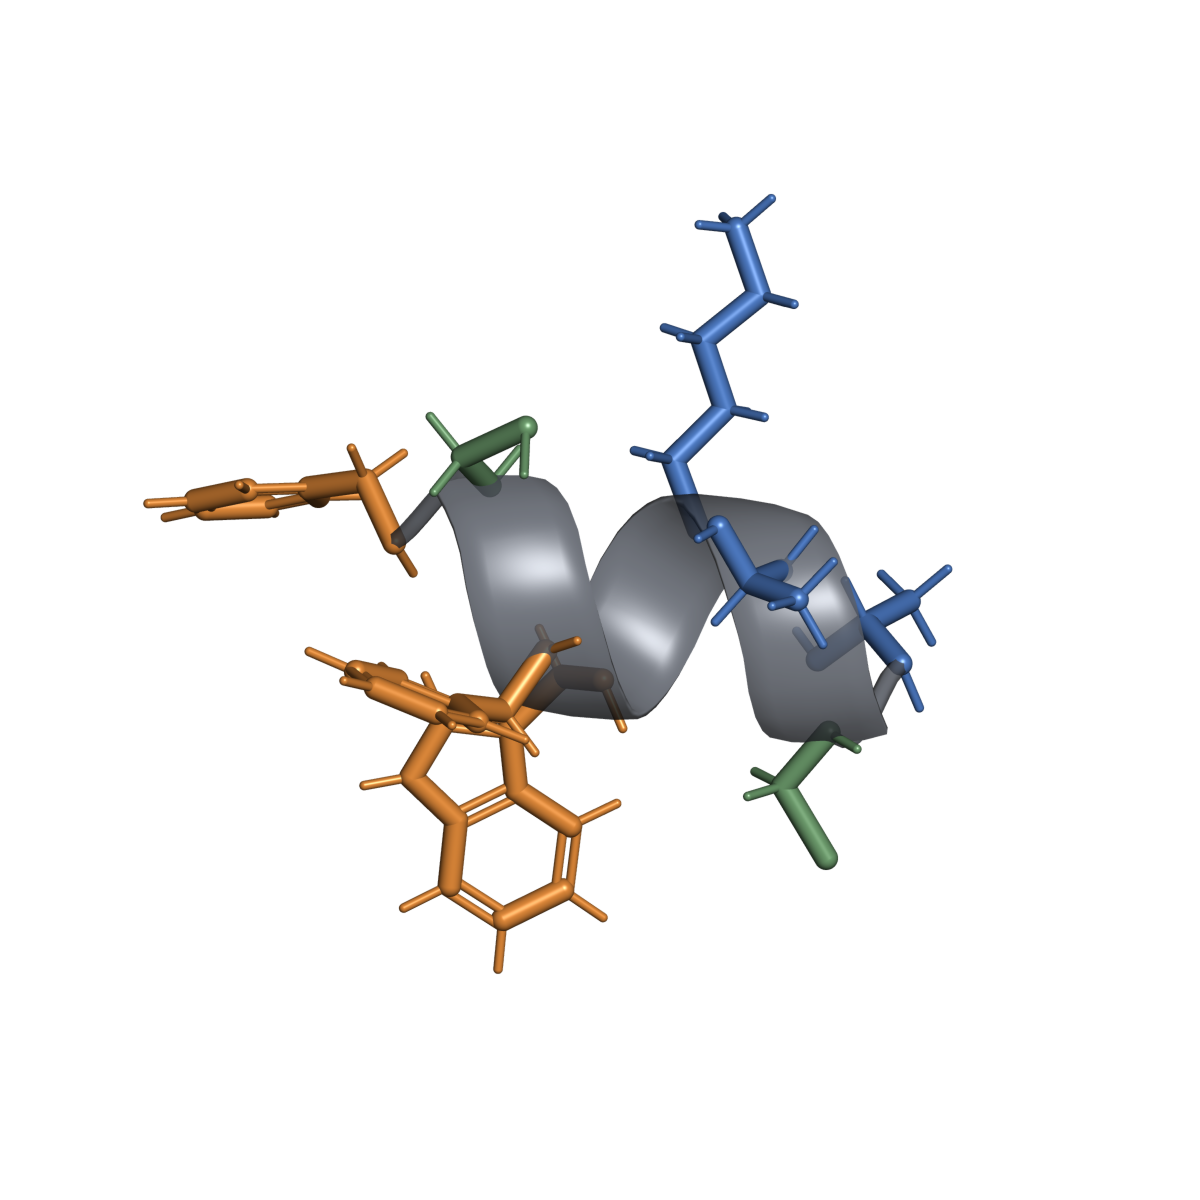
| Molecular/sequence identity | Linear D-Phe-Cys-Phe-D-Trp-Lys-Thr-Cys-Thr-ol (octapeptide amide); disulfide bridge Cys2–Cys7 |
| Modifications/form | Acetate salt; immediate-release SC/IV solution and LAR IM microsphere suspension |
| Stable identifiers | UNII: RWM8CCW8GP; The record number of a compound in PubChem, the atlas's primary structure-asset source. A registry record or depiction does not authenticate a commercial sample. Quelle der Definition: Identity and structure assets methodology · Glossar: 448601; CAS: 83150-76-9 (base); DrugBank: DB00104 |
| Identity caveats | Sequence differs from native somatostatin (14 or 28 aa). Multiple commercial peptide vial listings. |
Development and approval status
| Jurisdiction | Status and indication | Product/source | As of |
|---|---|---|---|
| US (FDA) | Approved: acromegaly, carcinoid syndrome, VIPoma | Sandostatin/Sandostatin LAR (Novartis) | 1988 (IR), 1998 (LAR) |
| EU/EEA (EMA) | Approved: acromegaly, carcinoid syndrome, VIPoma, prevention of complications after pancreatic surgery | Sandostatin/Sandostatin LAR | Oct 1998 |
| UK (MHRA) | Approved: same indications | Sandostatin | Dec 1998 |
- UNITED STATES
- US (FDA): Approved: acromegaly, carcinoid syndrome, VIPoma
- EU/EEA
- EU/EEA (EMA): Approved: acromegaly, carcinoid syndrome, VIPoma, prevention of complications after pancreatic surgery
- UNITED KINGDOM
- UK (MHRA): Approved: same indications
- OTHER DOCUMENTED
- No OTHER DOCUMENTED row is present in the source status table
Sport status: WADA: octreotide was not identified by exact name in the 2026 Prohibited List, and this review did not identify a matching prohibited class; athletes should verify current case-specific status.
Mechanism and pharmacology
Somatostatin receptor agonist with highest affinity for SSTR2 (Kᵢ ~0.4 nM) and SSTR5 (Kᵢ ~0.3 nM); lower affinity for SSTR3 and negligible for SSTR1,4. Inhibits growth hormone (GH), insulin-like growth factor 1 (IGF-1), glucagon, insulin, and gastrointestinal peptide secretion. Reduces splanchnic blood flow and intestinal motility.
Evidence by claim
| Claim/indication | Stage | Grade | Best human evidence | Main result | Important limitations |
|---|---|---|---|---|---|
| Acromegaly (adjunct to surgery/RT) | Approved | A | Phase 3 trials (NCT multiple) | GH <2.5 ng/mL and normalized IGF-1 in ~65% with LAR | Response varies by tumor SSTR profile |
| Carcinoid syndrome diarrhea | Approved | A | Pivotal crossover trials (1980s–90s) | Symptom control in ~70% of patients | No contemporary An inactive comparator used in a controlled study. Quelle der Definition: Neutral gloss; usage context: Evidence grading methodology · Glossar-controlled pivotal data |
| Metastatic midgut NET (disease control) | Supported by evidence; off-label in US | A | PROMID (Rinke A, et al. J Clin Oncol. 2009;27:4656–63. PMID: 19704057) | Median TTP 14.3 mo vs 6.0 mo placebo (HR 0.34) | Midgut NET only; US label only covers symptom control in metastatic carcinoid tumors and VIPoma diarrhea — effects on tumor size/growth/metastases not established per FDA label |
| VIPoma diarrhea | Approved | A | A study in which participants and investigators know what is administered. Quelle der Definition: Neutral gloss; usage context: Evidence grading methodology · Glossar series | Symptom control reported | No controlled trial |
- AKlasse A: Für eine bestimmte gekennzeichnete Anwendung nachgewiesen
- BKlasse B: Mäßige Humanstudien
- CKlasse C: Vorläufige Humanstudien
- DKlasse D: Nur präklinisch
- EKlasse E: Anekdotisch/Vermarktungsbehauptung
- XKlasse X: Die Evidenz widerspricht der Behauptung oder stützt sie nicht
Text alternative for the claim-evidence diagram. Each grade is defined below:
- A — Established for a specific labeled use
- 4 claims: Acromegaly (adjunct to surgery/RT); Carcinoid syndrome diarrhea; Metastatic midgut NET (disease control); VIPoma diarrhea
- B — Moderate human evidence
- 0 claims
- C — Preliminary human evidence
- 0 claims
- D — Preclinical only
- 0 claims
- E — Anecdotal/marketing claim
- 0 claims
- X — Evidence contradicts or does not support the claim
- 0 claims
Key studies
| Study | Design/population | Exposure studied | Endpoints and result | Limitations |
|---|---|---|---|---|
| PROMID | A study in which participants are assigned to the study material or a comparator by chance. Quelle der Definition: Neutral gloss; usage context: Evidence grading methodology · Glossar, N=85, treatment-naïve metastatic midgut NET | Octreotide LAR 30 mg Administered into a muscle. Quelle der Definition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossar q4wk vs An inactive comparator used in a controlled study. Quelle der Definition: Neutral gloss; usage context: Evidence grading methodology · Glossar | Median TTP 14.3 vs 6.0 mo (HR 0.34, p=0.000072) | A study in which participants and investigators know what is administered. Quelle der Definition: Neutral gloss; usage context: Evidence grading methodology · Glossar after progression; low-grade tumors |
| CSOM230C2402 (PAOLA) | RCT, N=198, acromegaly uncontrolled on first-generation SSA | Pasireotide LAR vs octreotide LAR | Biochemical control: 20% pasireotide vs 0% octreotide (p<0.001) | Active comparator, not placebo |
Dose and administration evidence
Approved labeled regimen
The label summary below is product-, indication-, and jurisdiction-specific; consult the full current label and a licensed clinician/pharmacist.
Acromegaly — Administered into the tissue layer under the skin. Quelle der Definition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossar: 50–100 mcg three times daily initially, then LAR: 10–30 mg Administered into a muscle. Quelle der Definition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossar q4wk. Carcinoid syndrome — SC: 100–600 mcg/day in 2–4 divided doses; LAR: 20–30 mg IM q4wk. VIPoma — SC: 200–300 mcg/day in 2–4 divided doses; LAR 20–30 mg IM q4wk. (LAR requires SC overlap for 2 weeks after first IM dose.)
Studied regimens (not recommendations)
PROMID: octreotide LAR 30 mg IM q4wk for NET disease control.
What is not established
Effects on tumor size, growth, or metastases — not established in the US label for octreotide; PROMID disease-control data are supported but off-label in the US.
Efficacy in pancreatic NET not demonstrated (PROMID excluded pancreatic primary).
No established role in obesity, diabetic complications, or other off-label metabolic uses.
Safety
Established label risks
Gallbladder: Cholelithiasis (~50% of patients on chronic therapy). Ultrasound recommended before and during therapy.
Metabolic: Hyperglycemia and hypoglycemia (effects on GH, insulin, glucagon balance).
Cardiovascular: Bradycardia, QT prolongation (ECG monitoring in at-risk patients).
GI: Nausea, diarrhea, steatorrhea.
Injection site: Pain, inflammation; LAR requires proper Administered into a muscle. Quelle der Definition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossar technique.
Human-study signals
PROMID: 8.2% cholelithiasis reported; GI adverse events 31%.
Unknowns and product-quality risks
Long-term safety beyond 2 years in NETs in controlled settings.
Research-grade vials may lack LAR formulation, potency, or sterility assurance.
Interactions and special populations
May reduce absorption of cyclosporine, cimetidine.
May alter insulin/oral antidiabetic requirements.
Bradycardia additive with beta-blockers, calcium channel blockers.
Dose adjustment not required in renal impairment; caution in hepatic impairment.
Regulatory, compounding, and sport notes
The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. Quelle der Definition: WADA and sport regulation brief · Glossar: octreotide was not identified by exact name in the 2026 Prohibited List, and this review did not identify a matching prohibited class; athletes should verify current case-specific status.
Not scheduled under US CSA.
Research-use-only vials are not FDA-evaluated.
LAR formulation complex; not replicable by simple compounding.
Evidence gaps
Direct comparison of LAR depot formulations with lanreotide Autogel efficacy.
Optimal duration and long-term NET disease control beyond 2 years.
Biomarker-based selection of SSTR-directed therapy.
Search notes
Databases and registries: DailyMed, PubMed, ClinicalTrials.gov, EMA EPAR
Search terms: octreotide, Sandostatin, Sandostatin LAR, PROMID, acromegaly, neuroendocrine tumor
Last searched: 2026-08-06
Inclusion emphasis: Regulatory labels, pivotal A study in which participants are assigned to the study material or a comparator by chance. Quelle der Definition: Neutral gloss; usage context: Evidence grading methodology · Glossar, systematic reviews
Sources
Sandostatin LAR (octreotide) prescribing information. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d0b7fe9e-7000-4b79-ba3b-291ce92c14f9
Rinke A, et al. Placebo-controlled, double-blind, prospective, randomized study on the effect of octreotide LAR in the control of tumor growth in patients with metastatic neuroendocrine midgut tumors (PROMID). J Clin Oncol. 2009;27(28):4656–63. PMID: 19704057.
Gadelha MR, et al. Pasireotide versus octreotide in acromegaly: a head-to-head superiority study (PAOLA). Lancet Diabetes Endocrinol. 2014;2(11):875–84. PMID: 25260838.
UK electronic Medicines Compendium. Sandostatin LAR (octreotide acetate) SmPC. https://www.medicines.org.uk/emc/product/1038/smpc
PubChem. Octreotide. https://pubchem.ncbi.nlm.nih.gov/compound/448601
WADA. 2026 Prohibited List. https://www.wada-ama.org/en/resources/world-anti-doping-program/prohibited-list