
Bottom line
Synthetic human angiotensin II (Giapreza) is an Administered into a vein. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 vasoconstrictor approved for increasing blood pressure in adults with vasodilatory (septic or other distributive) shock. The ATHOS-3 trial demonstrated a significant pressor-sparing effect. High-acuity ICU-only use with specific thromboembolic risk warnings.
Identity and composition
| Field | Verified information |
|---|---|
| Preferred name | Angiotensin II |
| Key aliases | Giapreza, synthetic human angiotensin II |
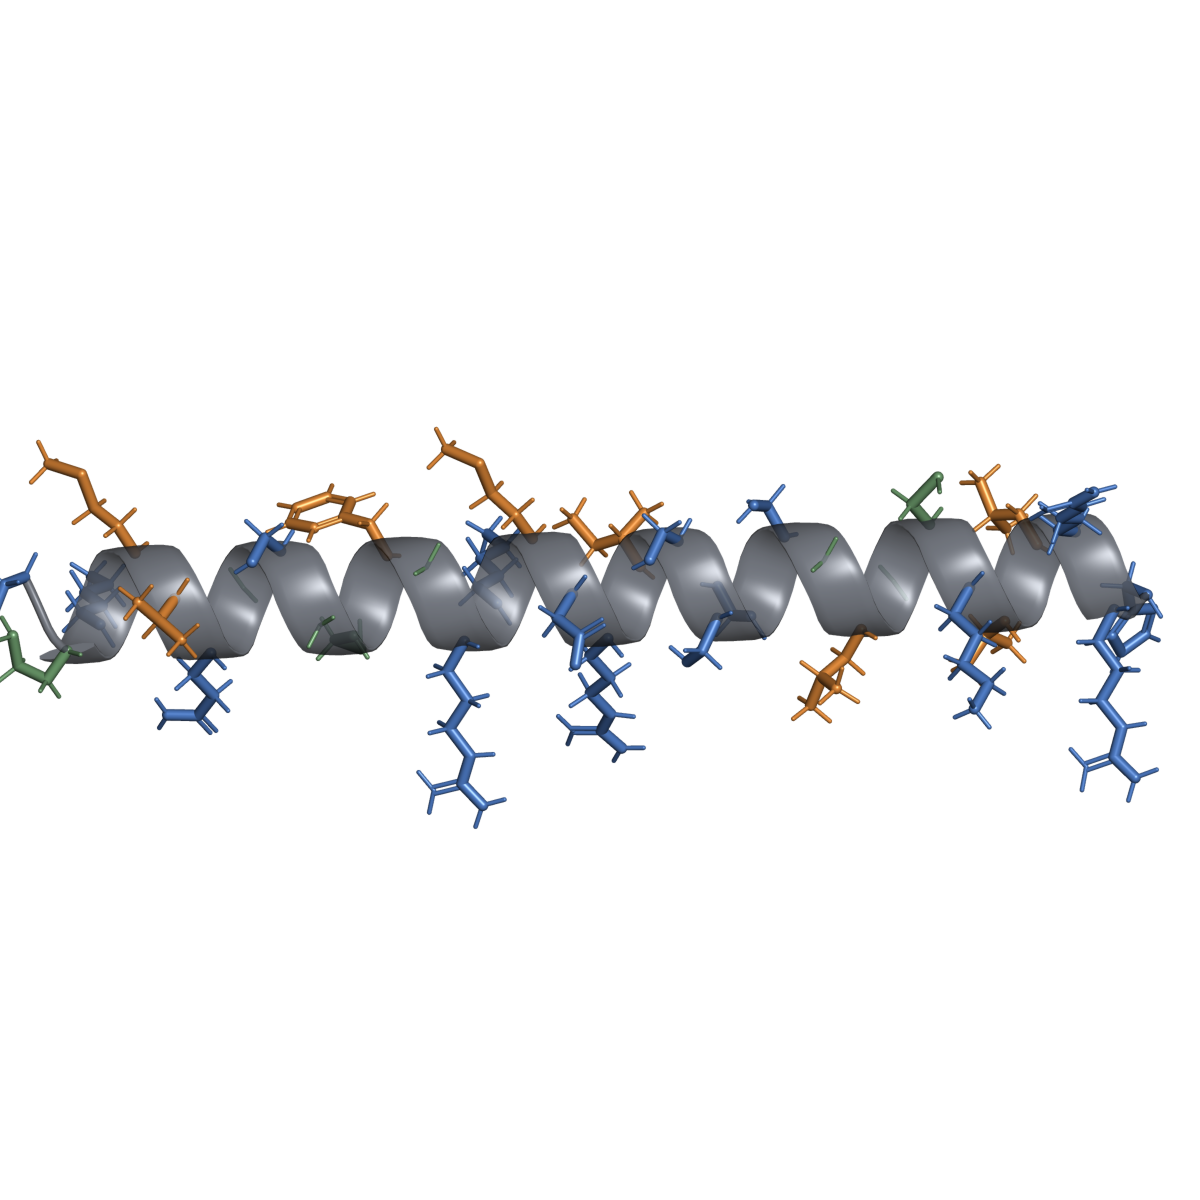
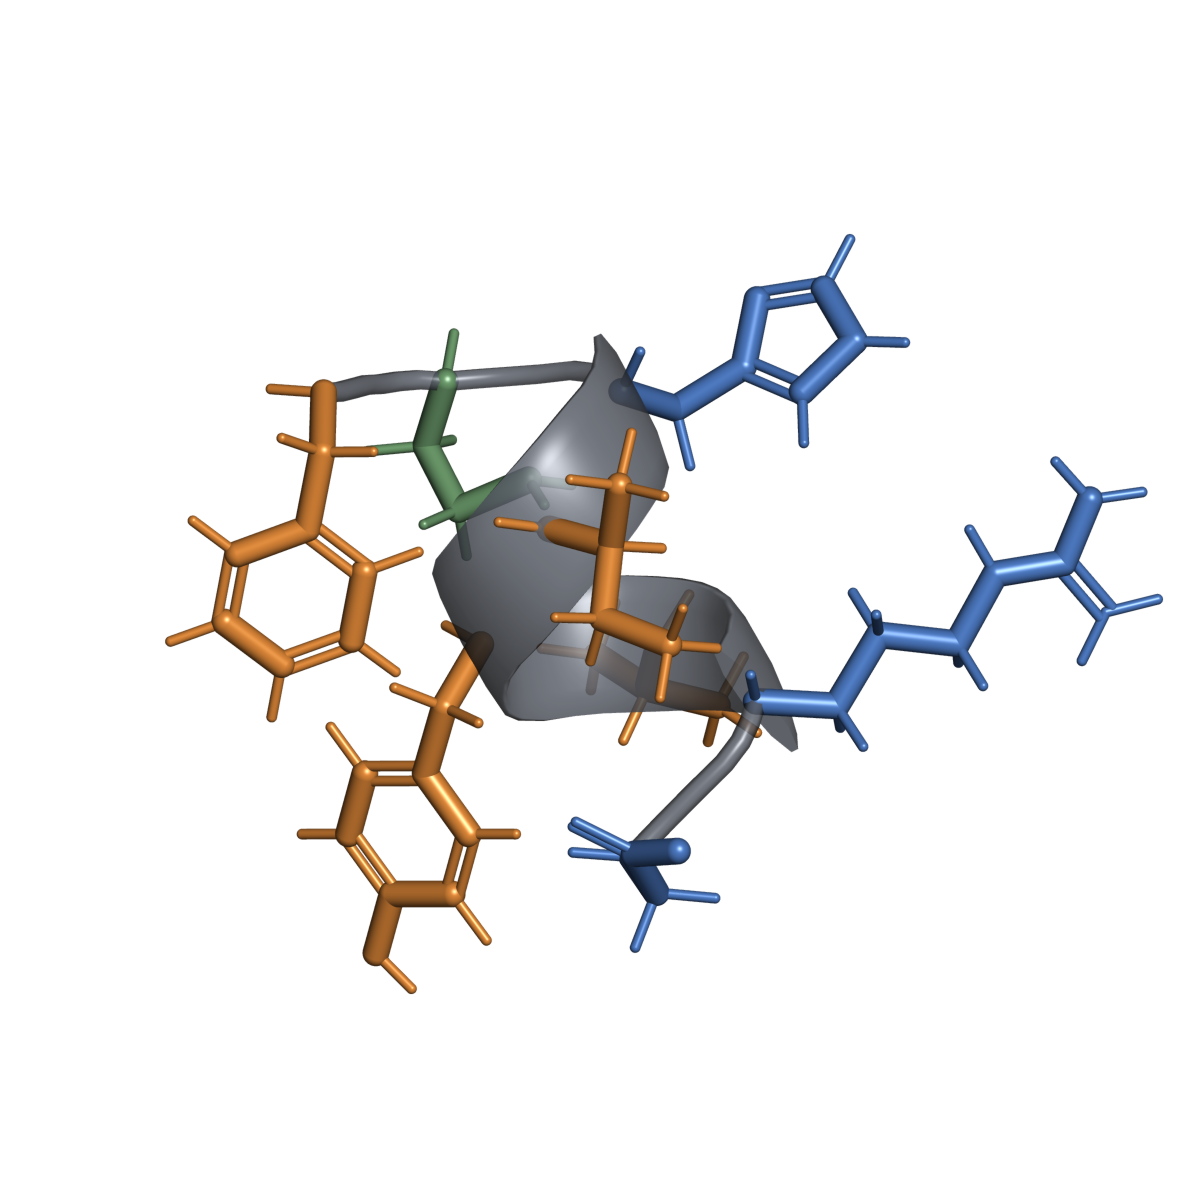
| Molecular/sequence identity | Asp-Arg-Val-Tyr-Ile-His-Pro-Phe (octapeptide, human sequence) |
| Modifications/form | Acetate salt; Administered into a vein. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 infusion concentrate (2.5 mg/mL, diluted for use) |
| Stable identifiers | UNII: M89CC0J5DV; The record number of a compound in PubChem, the atlas's primary structure-asset source. A registry record or depiction does not authenticate a commercial sample. 定义来源: Identity and structure assets methodology · 术语表: 172198; CAS: 4474-91-3 (base); DrugBank: DB11848 |
| Identity caveats | Identical in sequence to An entry with substantial scientific visibility or identity value. Biological rationale and non-human evidence do not establish patient benefit. 定义来源: Scope and selection methodology · 术语表 human angiotensin II. A An entry with frequent visibility in the research-peptide ecosystem. Visibility is not endorsement, and marketed material is not assumed safe, sterile, authentic, or suitable for humans. 定义来源: Scope and selection methodology · 术语表 name alone does not establish the identity, salt form, concentration, sterility, or pharmaceutical equivalence of a listed material. |
Development and approval status
| Jurisdiction | Status and indication | Product/source | As of |
|---|---|---|---|
| US (FDA) | Approved: increasing blood pressure in adults with septic or other distributive shock | Giapreza (La Jolla Pharma), NDA 209360 | Dec 21, 2017 |
| EU/EEA (EMA) | Approved: same | Giapreza | Aug 2019 |
| UK (MHRA) | Approved: same | Giapreza | 2019 |
- UNITED STATES
- US (FDA): Approved: increasing blood pressure in adults with septic or other distributive shock
- EU/EEA
- EU/EEA (EMA): Approved: same
- UNITED KINGDOM
- UK (MHRA): Approved: same
- OTHER DOCUMENTED
- No OTHER DOCUMENTED row is present in the source status table
Sport status: WADA: angiotensin II was not identified by exact name in the 2026 Prohibited List, and this review did not identify a matching prohibited class. Endogenous status does not itself determine classification; athletes should verify the exact product and current status with their anti-doping organisation.
Mechanism and pharmacology
AT1 receptor agonist — potent systemic vasoconstrictor. Binds to angiotensin type 1 receptors on vascular smooth muscle, increasing intracellular calcium and causing arteriolar vasoconstriction. Also increases aldosterone release and renal tubular sodium reabsorption. Pressor effect within minutes.
Evidence by claim
| Claim/indication | Stage | Grade | Best human evidence | Main result | Important limitations |
|---|---|---|---|---|---|
| Vasodilatory shock (pressor effect) | Approved | A | ATHOS-3 (Khanna A, et al. N Engl J Med. 2017;377:419–30. PMID: 28528561) | 70% reached target MAP response at 3h vs 23% An inactive comparator used in a controlled study. 定义来源: Neutral gloss; usage context: Evidence grading methodology · 术语表 (on background vasopressors) at 20 ng/kg/min | Background catecholamines used; 28-day mortality not significantly different |
Text alternative for the claim-evidence diagram. Each grade is defined below:
- A — Established for a specific labeled use
- 1 claim: Vasodilatory shock (pressor effect)
- B — Moderate human evidence
- 0 claims
- C — Preliminary human evidence
- 0 claims
- D — Preclinical only
- 0 claims
- E — Anecdotal/marketing claim
- 0 claims
- X — Evidence contradicts or does not support the claim
- 0 claims
Key studies
| Study | Design/population | Exposure studied | Endpoints and result | Limitations |
|---|---|---|---|---|
| ATHOS-3 | A study in which participants are assigned to the study material or a comparator by chance. 定义来源: Neutral gloss; usage context: Evidence grading methodology · 术语表, N=321, vasodilatory shock with MAP 55–70 mm Hg despite >0.2 mcg/kg/min norepinephrine | Angiotensin II 20 ng/kg/min Administered into a vein. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 (titrated 1.25–200 ng/kg/min; after 3 hours, maintenance dose capped at 40 ng/kg/min per protocol) vs An inactive comparator used in a controlled study. 定义来源: Neutral gloss; usage context: Evidence grading methodology · 术语表 | MAP response at 3h: 70% vs 23% (p<0.001); baseline vasopressor dose reduced | A study in which participants and investigators know what is administered. 定义来源: Neutral gloss; usage context: Evidence grading methodology · 术语表 rescue design; mortality not improved |
Dose and administration evidence
Approved labeled regimen
The label summary below is product-, indication-, and jurisdiction-specific; consult the full current label and a licensed clinician/pharmacist.
Labeled regimen per Giapreza prescribing information:
Starting dose: 20 ng/kg/min via Administered into a vein. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 infusion (central line)
First 3 hours (titration phase): Titrate as frequently as every 5 minutes by increments of up to 15 ng/kg/min as needed to achieve or maintain target blood pressure. The current US label says not to exceed 80 ng/kg/min during the first 3 hours.
Maintenance (after first 3 hours): Reduce to the lowest effective maintenance dose. Typical maintenance range: 1.25–40 ng/kg/min. Maximum maintenance dose: 40 ng/kg/min (ceiling).
Titration increments: During the first 3 hours, increase or decrease by ≤15 ng/kg/min every 5 minutes. During maintenance, adjust by 5–15 ng/kg/min every 5–15 minutes as needed.
Down-titration: Once the underlying shock has sufficiently improved, the current US label directs down-titration every 5–15 minutes by increments of up to 15 ng/kg/min based on blood pressure.
Studied regimens (not recommendations)
ATHOS-3: starting dose 20 ng/kg/min; the study protocol allowed titration up to 200 ng/kg/min during the first 3 hours, then capped maintenance at 40 ng/kg/min. The 200 ng/kg/min trial ceiling is a historical protocol exposure, not the current US label maximum.
What is not established
Use outside vasodilatory shock (e.g., cardiogenic or hemorrhagic shock).
Pediatric use.
No established or recommended human dose for any other indication.
Safety
Established label risks
Thromboembolic events: Arterial and venous thrombosis reported (Warnings and Precautions, not boxed). Concomitant VTE prophylaxis recommended.
Ischemia: Mesenteric, coronary, cerebral ischemia risk.
Arrhythmia: Tachycardia, bradycardia, atrial fibrillation.
Hypertension: Overshoot hypertension.
Hypotension: On abrupt discontinuation.
Human-study signals
ATHOS-3: thromboembolic events 13% vs 5% An inactive comparator used in a controlled study. 定义来源: Neutral gloss; usage context: Evidence grading methodology · 术语表; serious adverse events 60% vs 67% (no significant difference).
Unknowns and product-quality risks
Mortality benefit not demonstrated.
Long-term outcomes not studied (short-term ICU therapy only).
Research-grade vials are not pharmaceutical Giapreza.
Interactions and special populations
ACE inhibitors may potentiate effect (increased angiotensin II sensitivity).
ARBs may reduce effect.
No data in pregnancy or nursing.
Regulatory, compounding, and sport notes
The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. 定义来源: WADA and sport regulation brief · 术语表: angiotensin II was not identified by exact name in the 2026 Prohibited List, and this review did not identify a matching prohibited class. An entry with substantial scientific visibility or identity value. Biological rationale and non-human evidence do not establish patient benefit. 定义来源: Scope and selection methodology · 术语表 status does not itself determine classification; athletes should verify the exact product and current status with their anti-doping organisation.
No US federal CSA scheduling was identified as of 2026-08-06; state law and other jurisdictions were not assessed.
The reviewed GIAPREZA product is institutionally administered; this page makes no general claim about An entry with frequent visibility in the research-peptide ecosystem. Visibility is not endorsement, and marketed material is not assumed safe, sterile, authentic, or suitable for humans. 定义来源: Scope and selection methodology · 术语表 availability.
Evidence gaps
Mortality benefit not established in any subgroup.
Comparative effectiveness vs other third-line vasopressors (vasopressin, methylene blue).
Search notes
Databases and registries: DailyMed, PubMed, ClinicalTrials.gov, EMA
Search terms: angiotensin II, Giapreza, ATHOS-3, vasodilatory shock
Last searched: 2026-08-06
Inclusion emphasis: FDA label, pivotal A study in which participants are assigned to the study material or a comparator by chance. 定义来源: Neutral gloss; usage context: Evidence grading methodology · 术语表
Sources
Giapreza (angiotensin II) prescribing information. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=c265d69a-3efe-4107-9a9e-e6fd3d531c48
FDA. NDA 209360 approval letter for Giapreza (angiotensin II), signed December 21, 2017. https://www.accessdata.fda.gov/drugsatfda_docs/nda/2017/209360Orig1s000Approv.pdf
Khanna A, et al. Angiotensin II for vasodilatory shock (ATHOS-3). N Engl J Med. 2017;377(5):419–30. PMID: 28528561.
EMA. Giapreza EPAR. https://www.ema.europa.eu/en/medicines/human/EPAR/giapreza
PubChem. Angiotensin II. https://pubchem.ncbi.nlm.nih.gov/compound/172198
World Anti-Doping Agency. 2026 Prohibited List. https://www.wada-ama.org/sites/default/files/2025-09/2026list_en_final_clean_september_2025.pdf