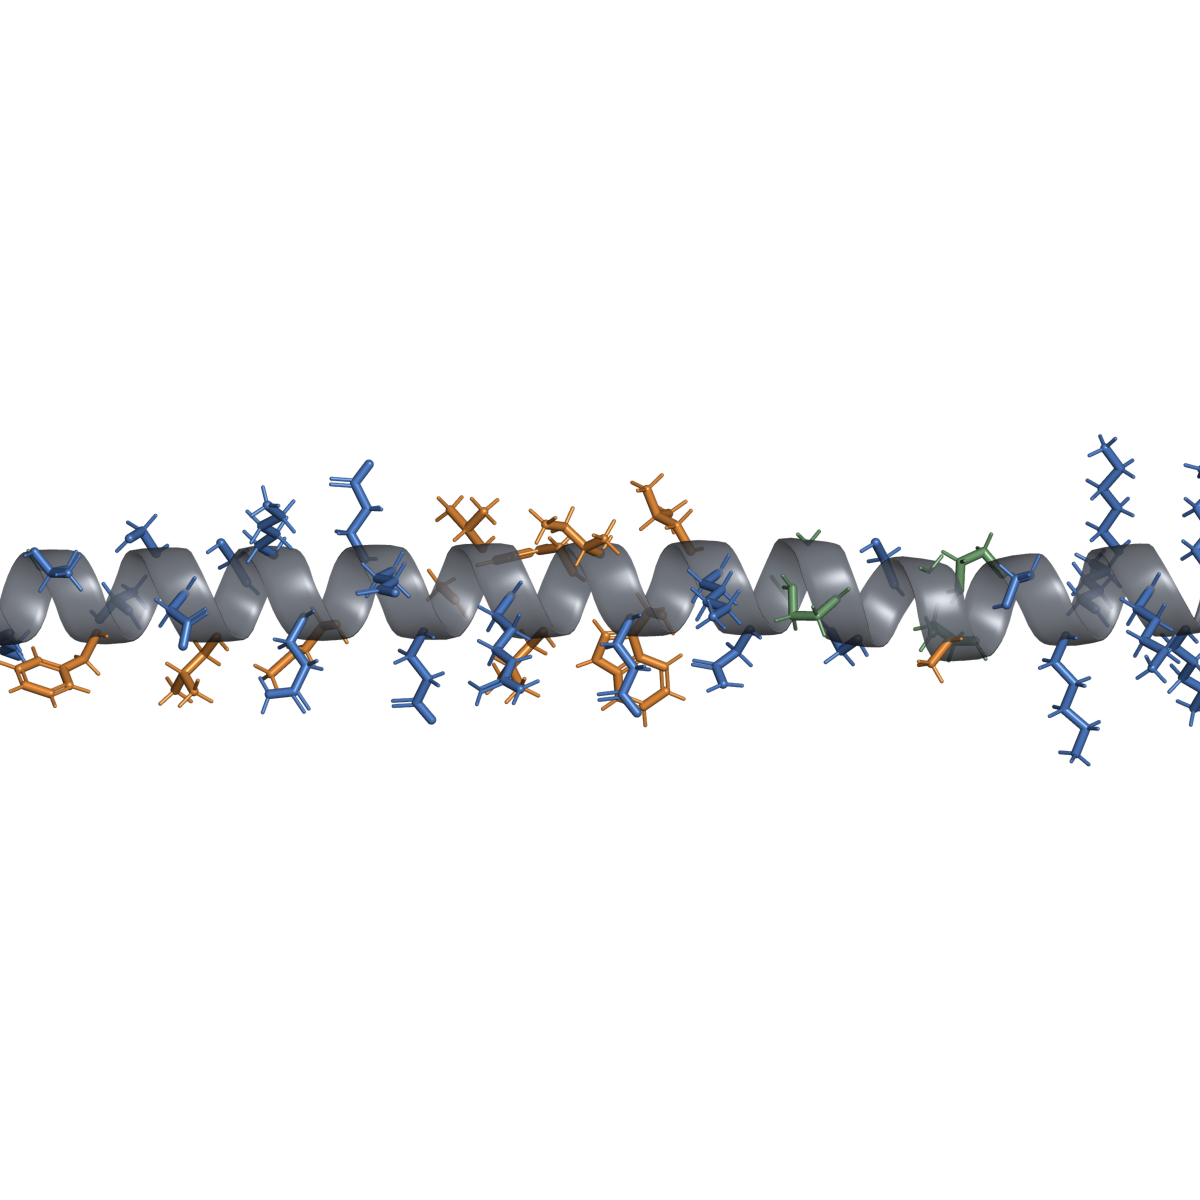

Bottom line
Lixisenatide is a once-daily, prandial Expansion of the abbreviation used in the monographs: glucagon-like peptide-1 receptor agonist. The atlas does not define the pharmacology of this class; see the monograph for what is documented about a specific compound. Definition source: Neutral gloss; the abbreviation is printed on the tirzepatide monograph but the atlas does not define the class pharmacology · Glossary derived from exendin-4, with a 44-amino-acid sequence that includes a C-terminal hexalysine tail. Approved in the US as Adlyxin (2016) and in the EU as Lyxumia (2013), it is notable for completing the first-ever GLP-1 RA cardiovascular outcomes trial (ELIXA, N=6,068), which demonstrated noninferiority for MACE but no superiority. Its prandial (pre-meal) dosing profile emphasizes postprandial glucose control. Immunogenicity is the highest in the GLP-1 RA class, with approximately 70% of patients developing anti-drug antibodies. Lixisenatide is not approved for weight management or CV risk reduction claims.
Identity and composition
| Field | Verified information |
|---|---|
| Preferred name | Lixisenatide |
| Key aliases | Adlyxin, Lyxumia, AVE 0010, ZP 10 |
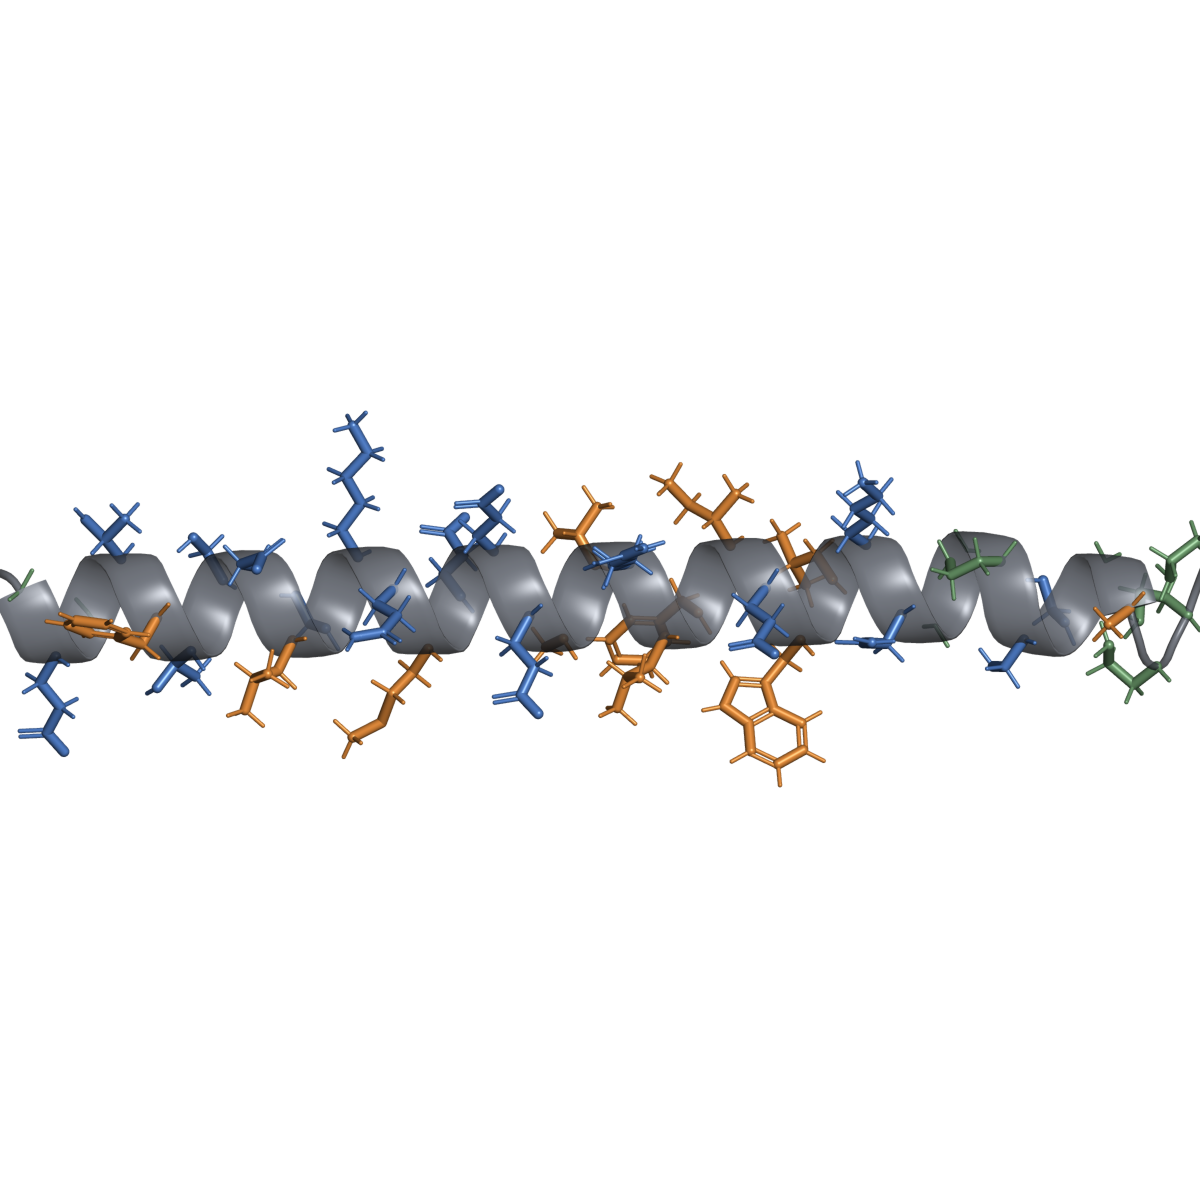
| Molecular/sequence identity | 44-amino-acid synthetic exendin-4 analog: H-His-Gly-Glu-Gly-Thr-Phe-Thr-Ser-Asp-Leu-Ser-Lys-Gln-Met-Glu-Glu-Glu-Ala-Val-Arg-Leu-Phe-Ile-Glu-Trp-Leu-Lys-Asn-Gly-Gly-Pro-Ser-Ser-Gly-Ala-Pro-Pro-Ser-Lys-Lys-Lys-Lys-Lys-Lys-NH₂ |
| Modifications/form | Exendin-4 backbone (53% homology to human GLP-1) with a C-terminal extension of six lysine residues (Lys-Lys-Lys-Lys-Lys-Lys-NH₂); not conjugated to protein carriers or fatty acids |
| Stable identifiers | The record number of a compound in PubChem, the atlas's primary structure-asset source. A registry record or depiction does not authenticate a commercial sample. Definition source: Identity and structure assets methodology · Glossary: 90472060; CAS: 320367-13-3; DrugBank: DB09265; UNII: 74O62BB01U |
| Identity caveats | Distinguish from exenatide (30 of 39 aa identity over the shared N-terminal region; lixisenatide is 5 aa longer). The hexalysine tail was designed to alter distribution and reduce variability (Zealand Pharma design). Not approved for once-weekly dosing unlike exenatide QW or semaglutide |
Development and approval status
| Jurisdiction | Status and indication | Product/source | As of |
|---|---|---|---|
| EU (EMA) | Approved Feb 2013 for T2D glycemic control | Lyxumia | 2026-08-06 |
| US (FDA) | Approved Jul 2016 for T2D glycemic control | Adlyxin (NDA 208471) | 2026-08-06 |
| US (FDA) | CV safety established (ELIXA); no CV risk reduction claim | — | 2026-08-06 |
| Manufacturer | Sanofi (in-licensed from Zealand Pharma) | Adlyxin/Lyxumia | 2026-08-06 |
- UNITED STATES
- US (FDA): Approved Jul 2016 for T2D glycemic control; US (FDA): CV safety established (ELIXA); no CV risk reduction claim
- EU/EEA
- EU (EMA): Approved Feb 2013 for T2D glycemic control
- UNITED KINGDOM
- No UNITED KINGDOM row is present in the source status table
- OTHER DOCUMENTED
- Manufacturer: Sanofi (in-licensed from Zealand Pharma)
Sport status: WADA: GLP-1 receptor agonists are not prohibited. Not listed on the WADA Prohibited List.
Mechanism and pharmacology
Lixisenatide is a Expansion of the abbreviation used in the monographs: glucagon-like peptide-1 receptor agonist. The atlas does not define the pharmacology of this class; see the monograph for what is documented about a specific compound. Definition source: Neutral gloss; the abbreviation is printed on the tirzepatide monograph but the atlas does not define the class pharmacology · Glossary based on the exendin-4 backbone. Like exenatide, it is naturally resistant to DPP-IV degradation due to the N-terminal His-Gly sequence. The C-terminal hexalysine tail was introduced to modulate How a substance is absorbed, distributed, metabolized, and eliminated by the body; atlas pages report pharmacokinetic data such as half-life, metabolism, and clearance. Definition source: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossary, reducing interindividual variability. The The time for the amount of a substance in the body to fall by half. Definition source: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossary is approximately 3 hours, but receptor binding characteristics allow once-daily dosing when administered before the main meal of the day (typically breakfast). Lixisenatide has a pronounced effect on postprandial glucose via delayed gastric emptying and reduced glucagon secretion, with more modest effects on fasting glucose compared to basal insulin or longer-acting GLP-1 RAs. It is predominantly cleared by glomerular filtration and tubular catabolism (Rosenstock et al., Diabetes Care 2013).
Evidence by claim
| Claim/indication | Stage | Grade | Best human evidence | Main result | Important limitations |
|---|---|---|---|---|---|
| Glycemic control (T2D) | Approved | A | GetGoal program (13 trials; >5,000 pts) | HbA1c reduction 0.5–0.9%; pronounced PPG reduction | Modest HbA1c reduction vs longer-acting Expansion of the abbreviation used in the monographs: glucagon-like peptide-1 receptor agonist. The atlas does not define the pharmacology of this class; see the monograph for what is documented about a specific compound. Definition source: Neutral gloss; the abbreviation is printed on the tirzepatide monograph but the atlas does not define the class pharmacology · Glossary; high immunogenicity |
| CV safety | Established (no superiority) [1] | A | ELIXA (N=6,068; median 2.1 yr) | MACE HR 1.02 (0.89–1.17); noninferior (P less than 0.001) | Neutral — no superiority; shortest CVOT follow-up among GLP-1 RAs; limited by 25% with baseline CVD |
| Weight management | Not approved | C | GetGoal weight outcomes (secondary endpoints) | Mean weight loss 2–3 kg vs An inactive comparator used in a controlled study. Definition source: Neutral gloss; usage context: Evidence grading methodology · Glossary | Modest; no dedicated obesity trial |
- AGrade A: Established for a specific labeled use
- BGrade B: Moderate human evidence
- CGrade C: Preliminary human evidence
- DGrade D: Preclinical only
- EGrade E: Anecdotal/marketing claim
- XGrade X: Evidence contradicts or does not support the claim
Text alternative for the claim-evidence diagram. Each grade is defined below:
- A — Established for a specific labeled use
- 2 claims: Glycemic control (T2D); CV safety
- B — Moderate human evidence
- 0 claims
- C — Preliminary human evidence
- 1 claim: Weight management
- D — Preclinical only
- 0 claims
- E — Anecdotal/marketing claim
- 0 claims
- X — Evidence contradicts or does not support the claim
- 0 claims
Key studies
| Study | Design/population | Exposure studied | Endpoints and result | Limitations |
|---|---|---|---|---|
| ELIXA; Pfeffer et al., NEJM 2015; PMID: 26378985 | CVOT; N=6,068 T2D with recent ACS (within 180 days); median 2.1 yr [1] | Lixisenatide 20 mcg daily vs An inactive comparator used in a controlled study. Definition source: Neutral gloss; usage context: Evidence grading methodology · Glossary | 4-point MACE HR 1.02 (0.89–1.17); noninferiority P less than 0.001; superiority P=0.81 | First Expansion of the abbreviation used in the monographs: glucagon-like peptide-1 receptor agonist. The atlas does not define the pharmacology of this class; see the monograph for what is documented about a specific compound. Definition source: Neutral gloss; the abbreviation is printed on the tirzepatide monograph but the atlas does not define the class pharmacology · Glossary CVOT; selected highest-risk population (recent ACS); short follow-up; underpowered for superiority |
| GetGoal-F1; Bolli et al., Diabet Med 2014; PMID: 24117597 | A study in which participants are assigned to the study material or a comparator by chance. Definition source: Neutral gloss; usage context: Evidence grading methodology · Glossary; N=676 T2D inadequate on metformin; 24 wk [1] | Lixisenatide 20 mcg daily vs placebo | HbA1c Δ −0.9% vs −0.4%; PPG Δ −4.0 mmol/L vs −1.3 mmol/L; weight −2.7 kg vs −1.8 kg | Short duration; placebo had meaningful HbA1c reduction (background med optimization) |
| GetGoal-L; Riddle et al., Diabetes Care 2013; PMID: 23628617 | RCT; N=495 T2D on basal insulin ± metformin; 24 wk [1] | Lixisenatide 20 mcg daily vs placebo | HbA1c Δ −0.7% vs −0.35%; no weight gain vs +0.1 kg; reduced insulin dose | Higher hypoglycemia (driven by basal insulin); small sample |
| GetGoal-X; Rosenstock et al., Diabetes Care 2013; PMID: 23698396 | RCT A study in which participants and investigators know what is administered. Definition source: Neutral gloss; usage context: Evidence grading methodology · Glossary; N=634 T2D on metformin; 24 wk [1] | Lixisenatide 20 mcg daily vs exenatide BID 10 mcg | HbA1c Δ −0.79% vs −0.96% (exenatide superior); less nausea with lixisenatide (24% vs 35%) | Exenatide more effective for HbA1c; open-label; higher overall GI AEs in exenatide |
Dose and administration evidence
Approved labeled regimen
The label summary below is product-, indication-, and jurisdiction-specific; consult the full current label and a licensed clinician/pharmacist.
The entry summarizes the cited US FDA Adlyxin label for type 2 diabetes.
Initiate 10 mcg Administered into the tissue layer under the skin. Definition source: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossary once daily within 1 hour before the same meal (preferably the main meal) for 14 days.
Increase to maintenance dose of 20 mcg SC once daily from day 15.
Administer SC in abdomen, thigh, or upper arm. If a dose is missed, skip it and resume with the next scheduled dose.
Studied regimens (not recommendations)
ELIXA and GetGoal trials used the 20 mcg daily maintenance regimen.
The 10 mcg initiation dose was added to reduce GI side effects during titration.
What is not established
Once-weekly formulation (not developed; only daily dosing studied).
Effectiveness in patients with HbA1c >10% or severe hyperglycemia.
Use without concomitant metformin or basal insulin (most trials were add-on therapy).
Weight management indication — no dedicated trial.
CV risk reduction claim — ELIXA showed neutrality, not superiority.
Safety
Established label risks
Gastrointestinal: Nausea (24–33%), vomiting (7–12%), diarrhea. Lower GI dropout rates than exenatide in head-to-head GetGoal-X.
Acute pancreatitis: Postmarketing reports; discontinue if suspected.
Acute kidney injury: Reports in setting of severe GI symptoms; use caution in renal impairment.
Hypoglycemia: Low risk with monotherapy; higher with sulfonylurea or basal insulin coadministration (as in GetGoal-L).
Immunogenicity: Highest in class — 70% anti-drug antibody positive in clinical trials; 2.7% high-titer antibodies with reduced efficacy (vs ~6% for Bydureon).
Human-study signals
ELIXA: No signal for pancreatitis (1.2% vs 1.2%), pancreatic cancer, or thyroid malignancy.
ELIXA: Higher serious GI events (6.0% vs 4.9%).
ELIXA: No excess heart failure hospitalization (HR 0.96, 0.75–1.23).
Injection-site reactions reported in ~1% of patients.
Unknowns and product-quality risks
Clinical significance of high immunogenicity for long-term efficacy and safety is not fully characterized. Lower-titer antibodies do not affect efficacy; high-titer (~2.7%) attenuate HbA1c response.
No data on cross-reactivity of anti-lixisenatide antibodies with native GLP-1 or exenatide.
No long-term safety data beyond 2.1 years (ELIXA median follow-up).
No approved generic or biosimilar as of 2026. Product is a synthetic peptide (NDA, not BLA), so generic pathway (ANDA) is possible in principle.
Interactions and special populations
Delays gastric emptying; oral medications requiring rapid absorption should be taken separately (label suggests at least 1 hour before or 4 hours after lixisenatide). Clinical significance for drugs with narrow therapeutic index.
Sulfonylurea or basal insulin: Increased hypoglycemia risk; consider dose reduction.
Renal impairment: Limited data in severe impairment (CrCl below 30 mL/min). Use caution; no dose adjustment for mild/moderate (CrCl 30–89).
Hepatic impairment: No dose adjustment; limited data in severe impairment.
Pregnancy: Class C per FDA labeling; animal studies show toxicity; avoid unless benefit outweighs risk.
Regulatory, compounding, and sport notes
Adlyxin has no FDA boxed warning; its contraindication is serious hypersensitivity.
Sanofi discontinued promotional activities for Adlyxin in the US post-launch; brand remains available but not actively marketed.
The product was in-licensed from Zealand Pharma; AVE 0010 references the Sanofi development code; ZP 10 references the Zealand Pharma code.
The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. Definition source: WADA and sport regulation brief · Glossary: Expansion of the abbreviation used in the monographs: glucagon-like peptide-1 receptor agonist. The atlas does not define the pharmacology of this class; see the monograph for what is documented about a specific compound. Definition source: Neutral gloss; the abbreviation is printed on the tirzepatide monograph but the atlas does not define the class pharmacology · Glossary are not prohibited. Not listed on the WADA Prohibited List.
Evidence gaps
CVOT superiority (ELIXA was neutral — the only Expansion of the abbreviation used in the monographs: glucagon-like peptide-1 receptor agonist. The atlas does not define the pharmacology of this class; see the monograph for what is documented about a specific compound. Definition source: Neutral gloss; the abbreviation is printed on the tirzepatide monograph but the atlas does not define the class pharmacology · Glossary CVOT to miss superiority)
Dedicated weight management trial
Head-to-head vs once-weekly GLP-1 RAs (only compared to exenatide BID)
Long-term efficacy and safety beyond ~2 years
Clinical significance of high immunogenicity — need for antibody monitoring unclear
Pediatric T2D data — no studies conducted
Data in patients with eGFR below 15 mL/min
Search notes
Databases and registries: PubMed, FDA Drugs@FDA, ClinicalTrials.gov, DailyMed, EMA EPAR
Search terms: "lixisenatide", "Adlyxin", "Lyxumia", "ELIXA", "GetGoal", "AVE 0010", "ZP 10"
Last searched: 2026-08-06
Inclusion emphasis: CVOT publication, phase 3 registration trials, FDA label, immunogenicity analyses
Sources
Pfeffer MA et al. Lixisenatide in patients with type 2 diabetes and acute coronary syndrome (ELIXA). N Engl J Med. 2015;373(23):2247-2257. PMID: 26378985. https://doi.org/10.1056/NEJMoa1509225
Rosenstock J et al. Efficacy and safety of lixisenatide once daily versus exenatide twice daily in type 2 diabetes inadequately controlled on metformin (GetGoal-X). Diabetes Care. 2013;36(9):2945-2951. PMID: 23698396. https://doi.org/10.2337/dc12-2709
Bolli GB et al. Efficacy and safety of lixisenatide once daily vs. placebo in people with type 2 diabetes insufficiently controlled on metformin (GetGoal-F1). Diabet Med. 2014;31(2):176-184. PMID: 24117597. https://doi.org/10.1111/dme.12328
Riddle MC et al. Adding once-daily lixisenatide for type 2 diabetes inadequately controlled by established basal insulin (GetGoal-L). Diabetes Care. 2013;36(9):2489-2496. PMID: 23628617. https://doi.org/10.2337/dc12-2454
FDA. Adlyxin (lixisenatide) injection label. NDA 208471. Drugs@FDA. Revised 2026. https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/208471s012lbl.pdf
Drucker DJ. Mechanisms of action and therapeutic application of GLP-1 and GIP receptor agonists. Cell Metab. 2018;27(4):740-756. PMID: 29617641. https://doi.org/10.1016/j.cmet.2018.03.001
Christensen M et al. Lixisenatide, a novel GLP-1 receptor agonist for the treatment of type 2 diabetes mellitus. IDrugs. 2009;12(8):503-517. PMID: 19629885.