Bottom line
Dalbavancin is a semisynthetic lipoglycopeptide antibiotic with a long The time for the amount of a substance in the body to fall by half. 定義の出典: Neutral gloss; usage context: Routes, devices, and absorption primer · 用語集 (~14 days) enabling a convenient 2-dose weekly Administered into a vein. 定義の出典: Neutral gloss; usage context: Routes, devices, and absorption primer · 用語集 regimen (1,000 mg day 1, 500 mg day 8) for ABSSSI. Its lipophilic side chain enhances activity against MRSA and other Gram-positive bacteria. Not active against Gram-negative organisms. A single 1,500 mg dose is also approved.
Identity and composition
| Field | Verified information |
|---|---|
| Preferred name | Dalbavancin |
| Key aliases | Dalvance, BI-397, VER001 |
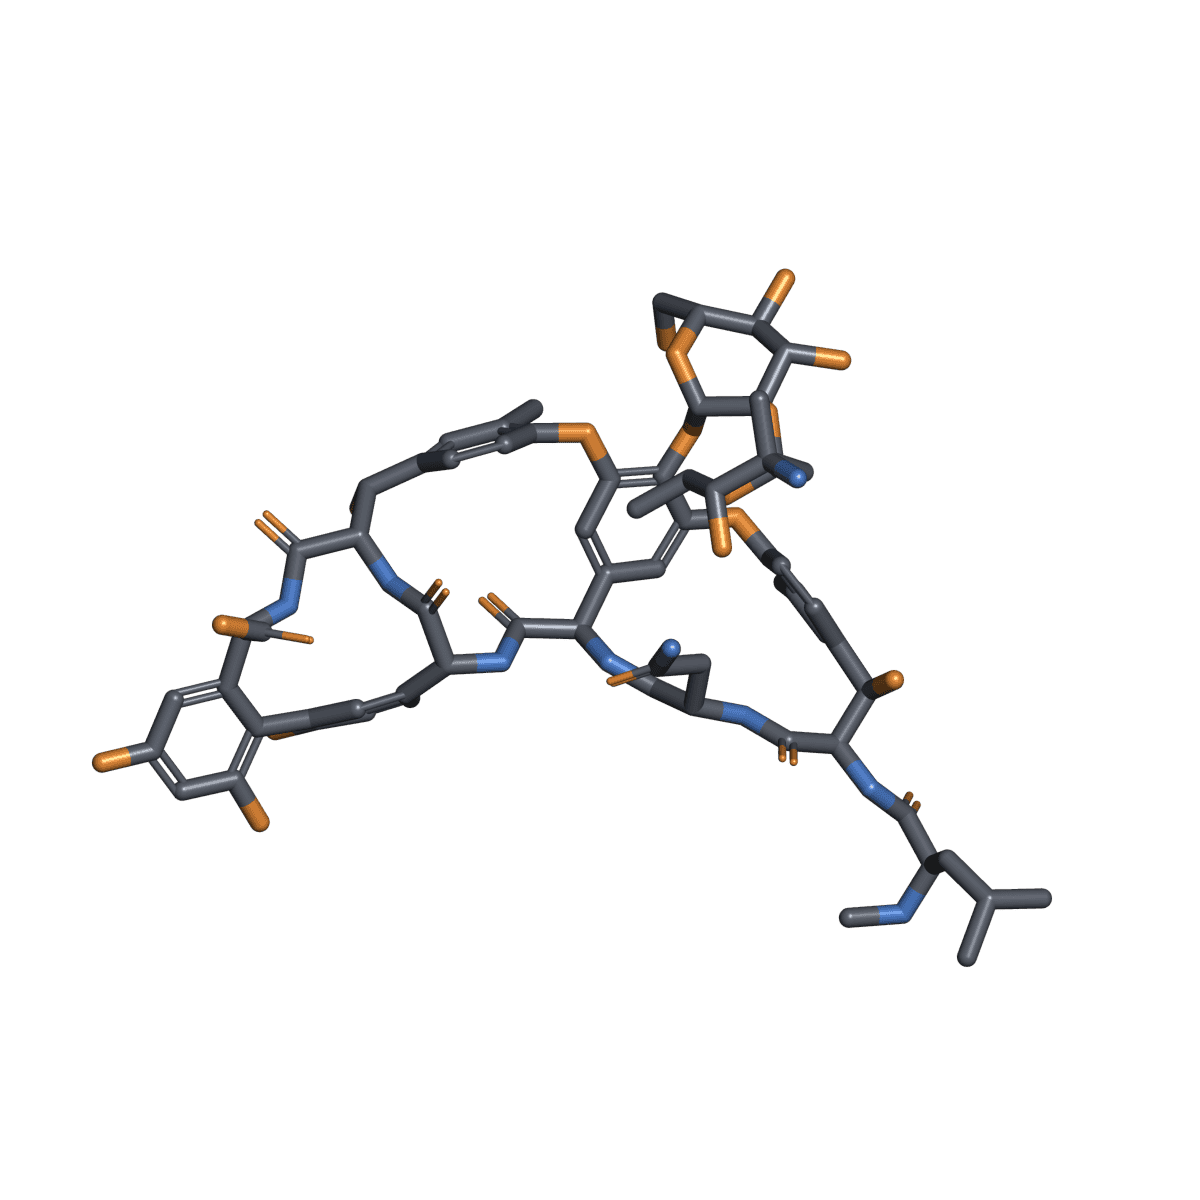
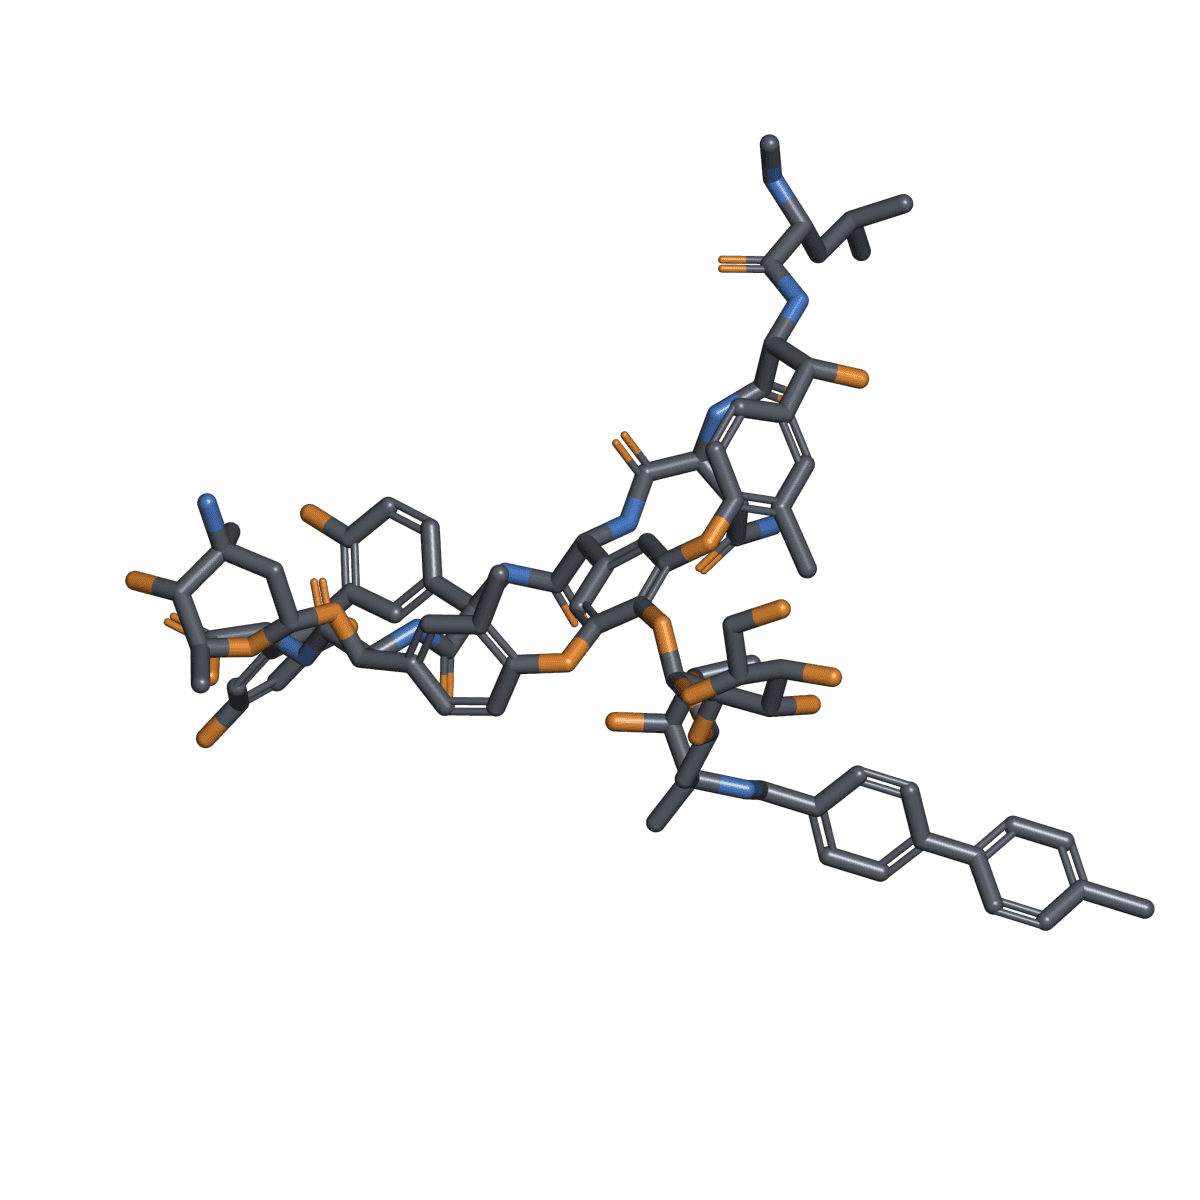
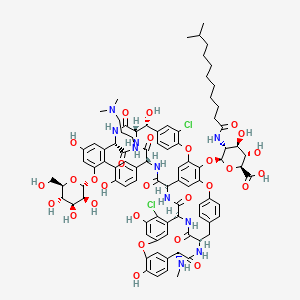
| Molecular/sequence identity | Semisynthetic lipoglycopeptide derived from the A40926 fermentation product of Nonomuraea species. A mixture of five active homologs (A0, A1, B0, B1, B2); B0 is the major component. The core structure is a glycopeptide with an N-acylaminoglucuronic acid moiety carrying a fatty acid side chain. |
| Modifications/form | Hydrochloride salt; Freeze-drying: water is removed by sublimation under reduced pressure, which can improve the stability of peptides and yield a porous dry matrix. Water removal does not sterilize a product, prove its quality, or define how it should later be handled. 定義の出典: Lyophilization, formulation, and stability primer · 用語集 powder for Administered into a vein. 定義の出典: Neutral gloss; usage context: Routes, devices, and absorption primer · 用語集 infusion after The product-specific pharmaceutical process by which a lyophilized (freeze-dried) solid returns to a liquid dispersion. It is not evidence that the resulting material is suitable for administration. 定義の出典: What reconstitution means primer · 用語集 and dilution |
| Stable identifiers | The record number of a compound in PubChem, the atlas's primary structure-asset source. A registry record or depiction does not authenticate a commercial sample. 定義の出典: Identity and structure assets methodology · 用語集: 16134627 (B0); DrugBank: DB09032; ChEBI: CHEBI:136534; CAS: 171500-79-1 |
| Identity caveats | A lipoglycopeptide — classified as a peptide-derived antibiotic, not a natural peptide. Distinguish from vancomycin (glycopeptide, no lipophilic side chain) and oritavancin. |
Development and approval status
| Jurisdiction | Status and indication | Product/source | As of |
|---|---|---|---|
| USA (FDA) | Approved — ABSSSI (adults and pediatric patients) | Dalvance (Durata Therapeutics/AbbVie) | 2014 |
| EU (EMA) | Approved — ABSSSI (adults) | Dalvance | 2015 |
- UNITED STATES
- USA (FDA): Approved — ABSSSI (adults and pediatric patients)
- EU/EEA
- EU (EMA): Approved — ABSSSI (adults)
- UNITED KINGDOM
- No UNITED KINGDOM row is present in the source status table
- OTHER DOCUMENTED
- No OTHER DOCUMENTED row is present in the source status table
Sport status: WADA status: not prohibited. No US federal CSA scheduling was identified as of 2026-08-06; state law and other jurisdictions were not assessed. FDA-approved ABSSSI populations and current generic availability are product-specific.
Mechanism and pharmacology
Dalbavancin interferes with bacterial cell wall synthesis by binding to the D-alanyl-D-alanine terminus of the stem pentapeptide in nascent peptidoglycan, preventing cross-linking. It is bactericidal in vitro against S. aureus and S. pyogenes. The lipophilic side chain increases potency and prolongs The time for the amount of a substance in the body to fall by half. 定義の出典: Neutral gloss; usage context: Routes, devices, and absorption primer · 用語集 by enhancing albumin binding and reducing renal clearance.
How a substance is absorbed, distributed, metabolized, and eliminated by the body; atlas pages report pharmacokinetic data such as half-life, metabolism, and clearance. 定義の出典: Neutral gloss; usage context: Routes, devices, and absorption primer · 用語集: Administered into a vein. 定義の出典: Neutral gloss; usage context: Routes, devices, and absorption primer · 用語集 administration; half-life ~14.4 days; high protein binding (>93%); primarily renal excretion; not CYP450 metabolized; no dose adjustment for hepatic impairment.
Evidence by claim
| Claim/indication | Stage | Grade | Best human evidence | Main result | Important limitations |
|---|---|---|---|---|---|
| ABSSSI (adults, two-dose) | Approved | A | Two identically designed phase 3 A study in which participants are assigned to the study material or a comparator by chance. 定義の出典: Neutral gloss; usage context: Evidence grading methodology · 用語集 (Trial 1/2; N=1,312); dalbavancin 1,000 mg d1 + 500 mg d8 vs vancomycin 1 g q12h (optional switch to linezolid) | Early clinical response (48-72 h): dalbavancin 79.7-82.3% vs vancomycin 75.8-80.7% — met non-inferiority (margin -10%) | ~5% received concomitant aztreonam; Eastern European majority population |
| ABSSSI (single dose) | Approved | A | Phase 3 RCT (Trial 3; N=698); dalbavancin 1,500 mg single dose vs 1,000/500 mg two-dose | Single dose non-inferior to two-dose regimen | Not An inactive comparator used in a controlled study. 定義の出典: Neutral gloss; usage context: Evidence grading methodology · 用語集-controlled; insufficient historical data to compare vs placebo at follow-up |
- AグレードA: 特定の表示使用に対して確立
- BグレードB: 中等度のヒトエビデンス
- CグレードC: 予備的ヒトエビデンス
- DグレードD: 前臨床のみ
- EグレードE: 逸話的/マーケティング主張
- XグレードX: エビデンスが主張と矛盾するか、支持しない
Text alternative for the claim-evidence diagram. Each grade is defined below:
- A — Established for a specific labeled use
- 2 claims: ABSSSI (adults, two-dose); ABSSSI (single dose)
- B — Moderate human evidence
- 0 claims
- C — Preliminary human evidence
- 0 claims
- D — Preclinical only
- 0 claims
- E — Anecdotal/marketing claim
- 0 claims
- X — Evidence contradicts or does not support the claim
- 0 claims
Key studies
| Study | Design/population | Exposure studied | Endpoints and result | Limitations |
|---|---|---|---|---|
| DUR001-301 and DUR001-302 (two-dose) | Phase 3, DB, double-dummy, A study in which participants are assigned to the study material or a comparator by chance. 定義の出典: Neutral gloss; usage context: Evidence grading methodology · 用語集; N=1,312; ABSSSI | Dalbavancin 1,000 mg Administered into a vein. 定義の出典: Neutral gloss; usage context: Routes, devices, and absorption primer · 用語集 d1 + 500 mg d8 vs vancomycin IV q12h | ECR (48-72 h): 79.7% vs 75.8% (Trial 1); 82.3% vs 80.7% (Trial 2); both met NI | Short course comparator (10-14 d); different geographies |
| DUR001-303 (single dose) | Phase 3, DB, RCT; N=698; ABSSSI | Dalbavancin 1,500 mg single dose vs two-dose regimen | Single dose met NI vs two-dose for ≥20% lesion reduction at 48-72 h | No active non-dalbavancin comparator for single dose |
Dose and administration evidence
Approved labeled regimen
The label summary below is product-, indication-, and jurisdiction-specific; consult the full current label and a licensed clinician/pharmacist.
Adults (two-dose): 1,000 mg Administered into a vein. 定義の出典: Neutral gloss; usage context: Routes, devices, and absorption primer · 用語集 followed 1 wk later by 500 mg IV. Single-dose: 1,500 mg IV ×1. Pediatric (3 mo to <18 y): weight-based. Infuse over 30 min. Renal impairment (CrCl <30 mL/min): two-dose regimen — 750 mg/375 mg; single dose — 1,125 mg.
What is not established
Use beyond ABSSSI (e.g., osteomyelitis, endocarditis — off-label studied but not approved).
Use in pregnancy: limited human data.
Pediatric patients <3 months: very limited data.
Safety
Established label risks
Nausea, diarrhea, headache, vomiting, pruritus — most frequent adverse events.
Infusion reactions (phlebitis, thrombophlebitis).
Elevated ALT/AST (typically mild).
Not studied in pregnancy; animal studies show no teratogenicity at clinically relevant exposures.
Human-study signals
No evidence of QTc prolongation (thorough QT study).
Lower overall adverse event rate than vancomycin in the phase 3 trials (driven largely by the ability to stop Administered into a vein. 定義の出典: Neutral gloss; usage context: Routes, devices, and absorption primer · 用語集 therapy earlier).
Unknowns and product-quality risks
One vial may not deliver full label dose; overdosing possible if multiple vials used without accounting for The product-specific pharmaceutical process by which a lyophilized (freeze-dried) solid returns to a liquid dispersion. It is not evidence that the resulting material is suitable for administration. 定義の出典: What reconstitution means primer · 用語集 overfill.
No oral formulation.
Interactions and special populations
Not a CYP inhibitor/inducer/substrate. Avoid concurrent nephrotoxic agents (limited data). Renal impairment requires dose adjustment (CrCl <30 mL/min). No dose change for mild-moderate hepatic impairment.
Regulatory, compounding, and sport notes
The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. 定義の出典: WADA and sport regulation brief · 用語集 status: not prohibited. No US federal CSA scheduling was identified as of 2026-08-06; state law and other jurisdictions were not assessed. FDA-approved ABSSSI populations and current generic availability are product-specific.
Evidence gaps
Comparative effectiveness vs ceftaroline or tedizolid for ABSSSI.
Utilization for off-label indications (osteomyelitis, IE, prosthetic joint infections).
Long-term safety of single-dose regimen (60-day follow-up used in trials).
Dalbavancin-nonsusceptible isolates: not observed in clinical trials but in vitro serial passage can select resistant variants.
Search notes
Databases and registries: FDA label (accessdata.fda.gov), DailyMed, ClinicalTrials.gov, PubMed
Search terms: dalbavancin, Dalvance, lipoglycopeptide, ABSSSI, MRSA, two-dose regimen
Last searched: 2026-08-06
Inclusion emphasis: FDA/EMA labels, phase 3 A study in which participants are assigned to the study material or a comparator by chance. 定義の出典: Neutral gloss; usage context: Evidence grading methodology · 用語集
Sources
FDA prescribing information: DALVANCE (dalbavancin) for injection. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2025/021883Orig1s012lbl.pdf (accessed 2026-08-06).
DailyMed: DALVANCE. Available at: https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=4b4674d8-4d1e-4728-8465-d42ada33fa5c (accessed 2026-08-06).
Boucher HW, et al. Once-weekly dalbavancin versus daily conventional therapy for skin infection. N Engl J Med. 2014;370(23):2169-79. DOI: 10.1056/NEJMoa1310480.
Dunne MW, et al. Single-dose oritavancin and dalbavancin for ABSSSI — two pivotal trials and a single-dose study. Clin Infect Dis. 2015;61(Suppl 2):S58-67. DOI: 10.1093/cid/civ675.