
Bottom line
Semaglutide is a long-acting GLP-1 receptor agonist modified with a C18 fatty diacid for albumin binding, enabling once-weekly subcutaneous (Ozempic, Wegovy) and once-daily oral (Rybelsus) administration.
It is approved across three indications — glycemic control in type 2 diabetes, chronic weight management, and cardiovascular risk reduction — and in August 2025 received accelerated FDA approval for metabolic dysfunction-associated steatohepatitis (MASH). The cardiovascular outcomes program (SUSTAIN-6, SELECT, SOUL) demonstrates MACE reduction in patients with and without diabetes. See the evidence grading methodology for an explanation of Grade A: Established for a specific labeled use — current approval plus adequate controlled trials and post-market context. Sumber definisi: Evidence grading methodology · Glosarium evidence.
Identity and composition
| Field | Verified information |
|---|---|
| Preferred name | Semaglutide |
| Key aliases | Ozempic, Rybelsus, Wegovy, NN 9936 |
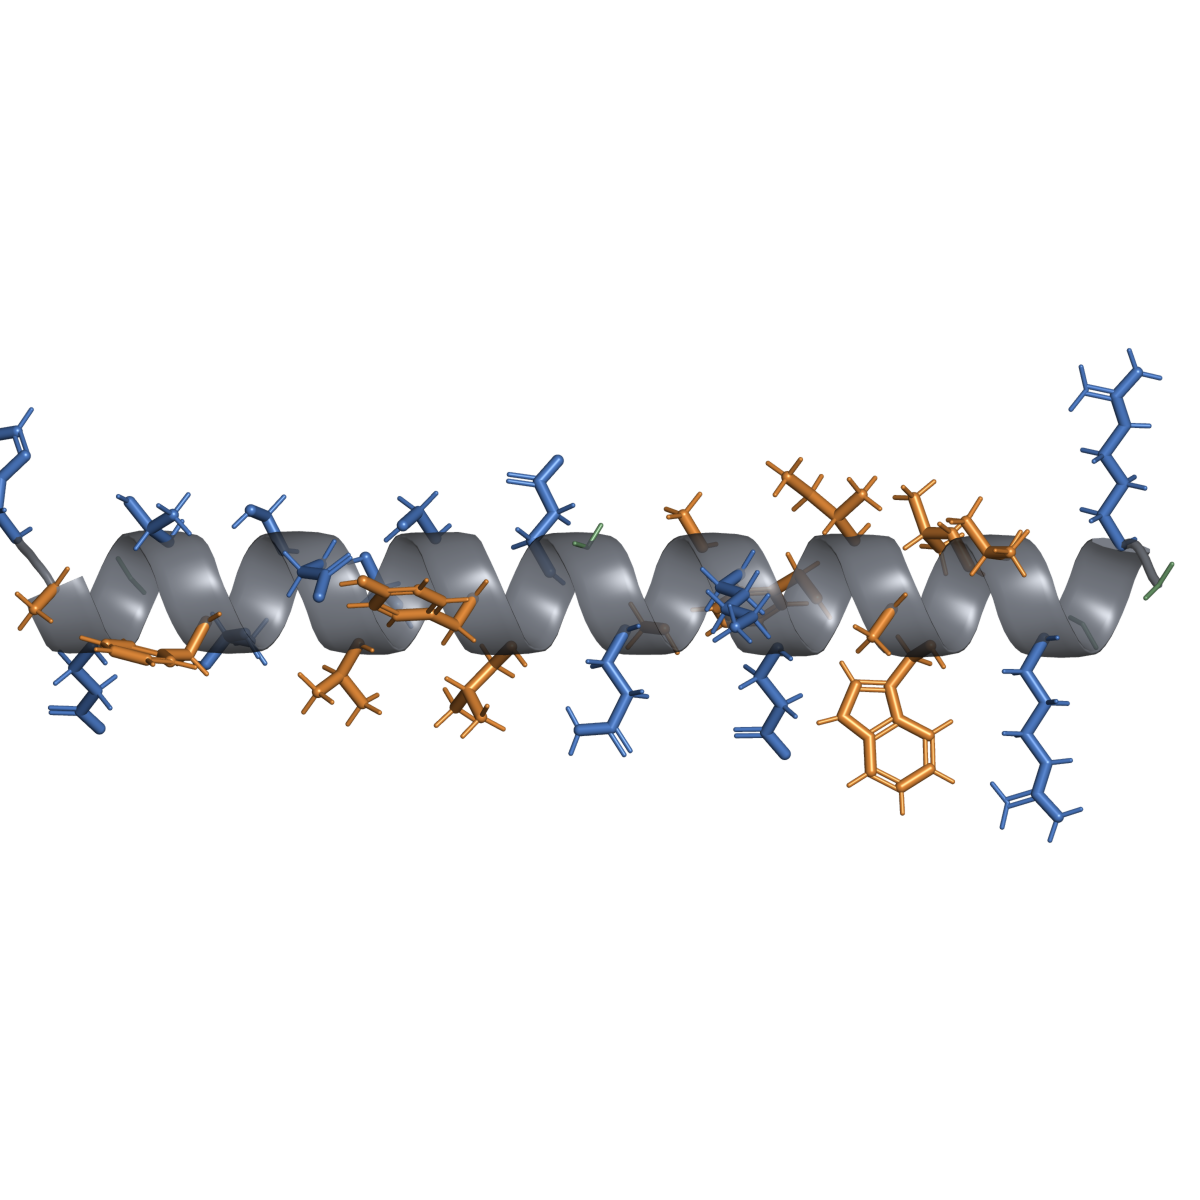
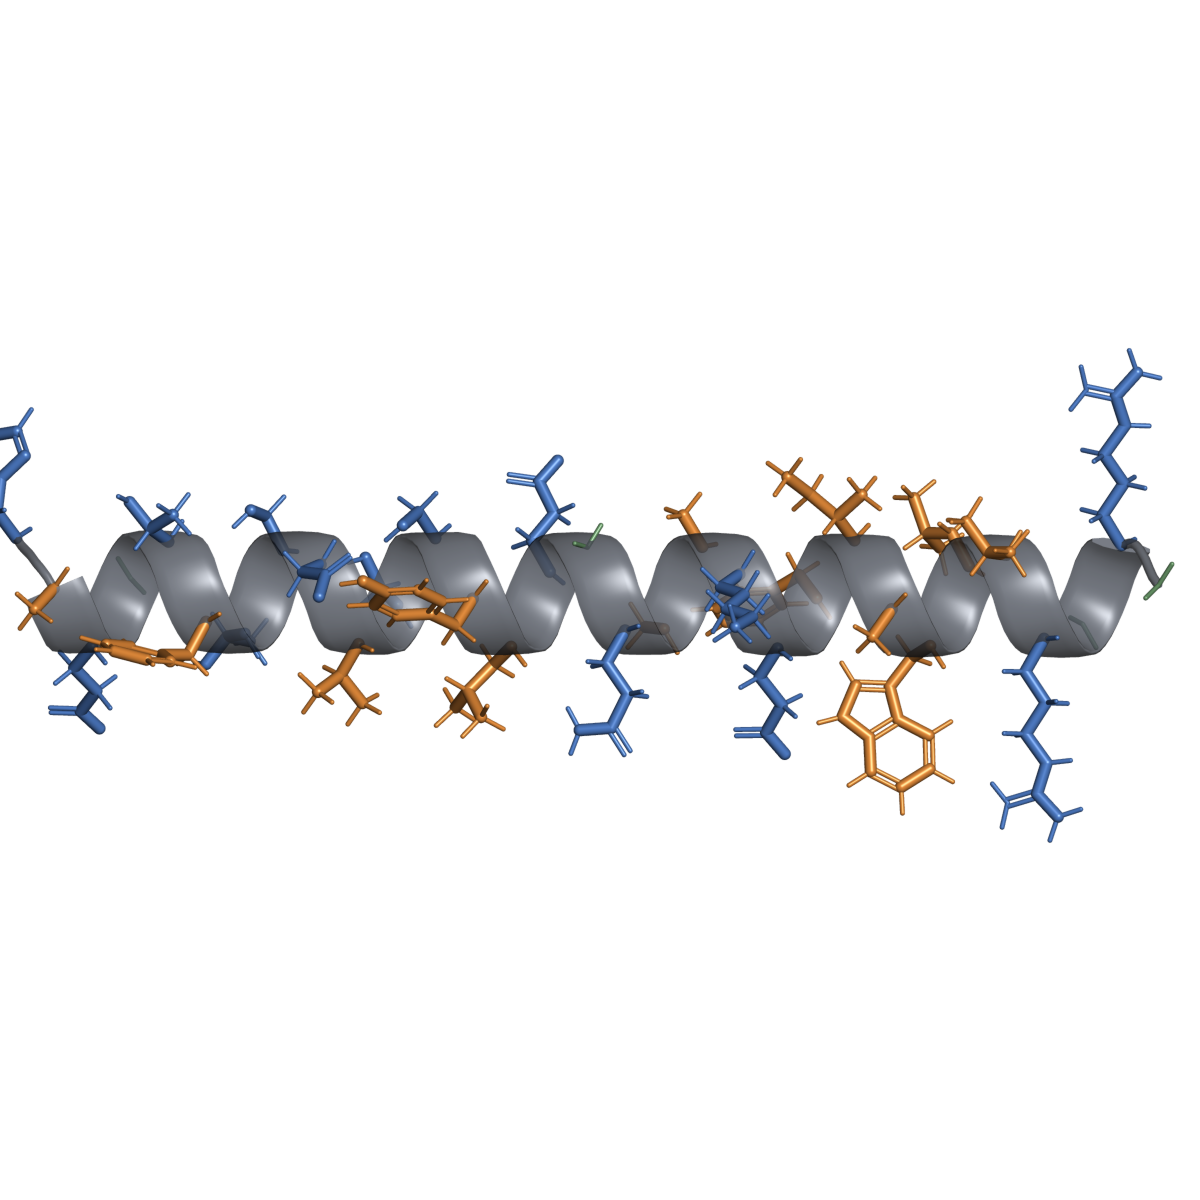
| Molecular/sequence identity | 31-amino-acid modified human GLP-1 analog: H-His-Aib-Glu-Gly-Thr-Phe-Thr-Ser-Asp-Val-Ser-Ser-Tyr-Leu-Glu-Gly-Gln-Ala-Ala-Lys(AEEAc-AEEAc-γ-Glu-17-carboxyheptadecanoyl)-Glu-Phe-Ile-Ala-Trp-Leu-Val-Arg-Gly-Arg-Gly-OH |
| Modifications/form | Aib substitution at position 2 (DPP-IV resistance); C18 fatty diacid linked via a hydrophilic spacer (AEEAc-AEEAc-γ-Glu) to Lys²⁶ for albumin binding; acetate or sodium salt |
| Stable identifiers | The record number of a compound in PubChem, the atlas's primary structure-asset source. A registry record or depiction does not authenticate a commercial sample. Sumber definisi: Identity and structure assets methodology · Glosarium: 56843331; CAS: 910463-68-2; DrugBank: DB15171; UNII: 53AXN4NNHX |
| Identity caveats | Distinguish from other Expansion of the abbreviation used in the monographs: glucagon-like peptide-1 receptor agonist. The atlas does not define the pharmacology of this class; see the monograph for what is documented about a specific compound. Sumber definisi: Neutral gloss; the abbreviation is printed on the tirzepatide monograph but the atlas does not define the class pharmacology · Glosarium; the 25 mg oral tablet (OASIS 4 program) uses the same active moiety with a different formulation |
Development and approval status
| Jurisdiction | Status and indication | Product/source | As of |
|---|---|---|---|
| US (FDA) | Approved Dec 2017 for T2D glycemic control | Ozempic injection (NDA 209637) | 2026-08-06 |
| US (FDA) | Approved Sep 2019 for T2D glycemic control | Rybelsus tablets (NDA 213051) | 2026-08-06 |
| US (FDA) | Approved Jun 2021 for chronic weight management (BMI ≥30 or ≥27 with ≥1 weight-related comorbidity) | Wegovy injection (NDA 215256) | 2026-08-06 |
| US (FDA) | Approved Mar 2024 for CV risk reduction in adults with obesity/overweight + CVD | Wegovy label expansion (SELECT trial) | 2026-08-06 |
| US (FDA) | Accelerated approval Aug 2025 for MASH (NASH) | Wegovy label expansion | 2026-08-06 |
| EU (EMA) | Approved Feb 2018 (Ozempic), Dec 2021 (Wegovy), Jun 2022 (oral) | Ozempic, Wegovy, Rybelsus | 2026-08-06 |
- UNITED STATES
- US (FDA): Approved Dec 2017 for T2D glycemic control; US (FDA): Approved Sep 2019 for T2D glycemic control; US (FDA): Approved Jun 2021 for chronic weight management (BMI ≥30 or ≥27 with ≥1 weight-related comorbidity); US (FDA): Approved Mar 2024 for CV risk reduction in adults with obesity/overweight + CVD; US (FDA): Accelerated approval Aug 2025 for MASH (NASH)
- EU/EEA
- EU (EMA): Approved Feb 2018 (Ozempic), Dec 2021 (Wegovy), Jun 2022 (oral)
- UNITED KINGDOM
- No UNITED KINGDOM row is present in the source status table
- OTHER DOCUMENTED
- No OTHER DOCUMENTED row is present in the source status table
Sport status: WADA: semaglutide is not prohibited, but its markers are included in the 2026 Monitoring Program in- and out-of-competition. Monitoring is not prohibition.
Mechanism and pharmacology
Receptor pharmacology
Semaglutide is a long-acting GLP-1 receptor agonist (Expansion of the abbreviation used in the monographs: glucagon-like peptide-1 receptor agonist. The atlas does not define the pharmacology of this class; see the monograph for what is documented about a specific compound. Sumber definisi: Neutral gloss; the abbreviation is printed on the tirzepatide monograph but the atlas does not define the class pharmacology · Glosarium). The Aib substitution at position 2 confers resistance to dipeptidyl peptidase-4 (DPP-IV) cleavage.
How a substance is absorbed, distributed, metabolized, and eliminated by the body; atlas pages report pharmacokinetic data such as half-life, metabolism, and clearance. Sumber definisi: Neutral gloss; usage context: Routes, devices, and absorption primer · Glosarium
The C18 fatty diacid chain binds non-covalently to serum albumin, extending the plasma half-life to approximately 1 week (168 h), enabling once-weekly SC dosing. Oral semaglutide (Rybelsus) uses the absorption enhancer sodium N-(8-[2-hydroxybenzoyl] amino) caprylate (SNAC) to facilitate gastric absorption.
Physiologic effects
Semaglutide increases glucose-dependent insulin secretion, suppresses glucagon secretion, delays gastric emptying, and promotes satiety through central GLP-1 receptor activation in the hypothalamus (Drucker, 2018; Marso et al., NEJM 2016).
Evidence by claim
See the evidence grading methodology for an explanation of Grade letters.
| Claim/indication | Stage | Grade | Best human evidence | Main result | Important limitations |
|---|---|---|---|---|---|
| Glycemic control (T2D) | Approved | A | SUSTAIN program (1–10, >10,000 pts) | HbA1c reduction 1.0–1.8% across doses | Predominantly vs An inactive comparator used in a controlled study. Sumber definisi: Neutral gloss; usage context: Evidence grading methodology · Glosarium or active comparator; A study in which participants and investigators know what is administered. Sumber definisi: Neutral gloss; usage context: Evidence grading methodology · Glosarium extensions |
| CV risk reduction (T2D+CVD) | Approved [1] | A | SUSTAIN-6 (N=3,297; 2.1 yr) | HR 0.74 for MACE (95% CI 0.58–0.95) | CV outcome was secondary endpoint; open-label |
| CV risk reduction (obesity, no T2D) | Approved [1] | A | SELECT (N=17,604; mean 3.75 yr) | HR 0.80 MACE (95% CI 0.72–0.90) | CV trial in overweight/obesity without diabetes; secondary prevention only; generalizability to primary prevention is unknown |
| Chronic weight management | Approved [1] | A | STEP program (1–8, >5,000 pts) | Mean weight loss ~15% at 68 wk (STEP 1) | High GI tolerability dropouts; no active comparator vs other anti-obesity drugs |
| MASH / NASH | Approved (accel. Aug 2025) | B | Phase 3 week-72 interim analysis | 63% vs 34% achieved MASH resolution without fibrosis worsening; 37% vs 22% achieved ≥1-stage fibrosis improvement without NASH worsening | Accelerated approval based on surrogate endpoints; confirmatory phase 3 required |
- AKelas A: Mapan untuk penggunaan berlabel tertentu
- BKelas B: Bukti manusia moderat
- CKelas C: Bukti manusia awal
- DKelas D: Hanya praklinis
- EKelas E: Klaim anekdot/pemasaran
- XKelas X: Bukti bertentangan atau tidak mendukung klaim
Text alternative for the claim-evidence diagram. Each grade is defined below:
- A — Established for a specific labeled use
- 4 claims: Glycemic control (T2D); CV risk reduction (T2D+CVD); CV risk reduction (obesity, no T2D); Chronic weight management
- B — Moderate human evidence
- 1 claim: MASH / NASH
- C — Preliminary human evidence
- 0 claims
- D — Preclinical only
- 0 claims
- E — Anecdotal/marketing claim
- 0 claims
- X — Evidence contradicts or does not support the claim
- 0 claims
Key studies
| Study | Design/population | Exposure studied | Endpoints and result | Limitations |
|---|---|---|---|---|
| SUSTAIN-6; Marso et al., NEJM 2016; PMID: 27633186 | CVOT; N=3,297 T2D with high CV risk; median 2.1 yr [1] | Semaglutide 0.5/1.0 mg Administered into the tissue layer under the skin. Sumber definisi: Neutral gloss; usage context: Routes, devices, and absorption primer · Glosarium qwk vs An inactive comparator used in a controlled study. Sumber definisi: Neutral gloss; usage context: Evidence grading methodology · Glosarium | 3-point MACE HR 0.74 (0.58–0.95); nonfatal stroke HR 0.61; driven by vascular outcomes | A study in which participants and investigators know what is administered. Sumber definisi: Neutral gloss; usage context: Evidence grading methodology · Glosarium; CV endpoint not primary; fewer events than typical CVOT |
| SELECT; Lincoff et al., NEJM 2023; PMID: 37952131 | CVOT; N=17,604 adults with overweight/obesity + established CVD, no T2D; mean 3.75 yr [1] | Semaglutide 2.4 mg SC qwk (Wegovy) vs placebo | MACE HR 0.80 (0.72–0.90); 20% RRR; consistent across subgroups | No diabetes population; generalizability to primary CV prevention unclear |
| STEP 1; Wilding et al., NEJM 2021; PMID: 34154581 | A study in which participants are assigned to the study material or a comparator by chance. Sumber definisi: Neutral gloss; usage context: Evidence grading methodology · Glosarium; N=1,961 adults with overweight/obesity; 68 wk [1] | Semaglutide 2.4 mg SC qwk vs placebo | Mean weight change −14.9% vs −2.4%; 86% achieved ≥5% loss | High GI AE rate; 5% discontinued for GI intolerance; open-label extension |
| OASIS 4; ClinicalTrials.gov NCT05586997 | RCT; N=1,200 T2D; oral semaglutide 25 mg | Oral semaglutide 25 mg daily vs placebo | HbA1c reduction superior to lower doses | Not yet fully published; results from press release |
| SOUL; ClinicalTrials.gov NCT03574597 | CVOT; N=9,650 T2D with CVD/CKD; oral semaglutide | Oral semaglutide 14 mg daily vs placebo | MACE HR reported at ADA 2024; met primary endpoint | Full peer-reviewed publication pending |
| MASH week-72 interim; ClinicalTrials.gov NCT04822181 | Phase 3 RCT; N=approx 960 adults with MASH and F2/F3 fibrosis [1] | Semaglutide 2.4 mg SC qwk vs placebo | 63% vs 34% achieved MASH resolution without fibrosis worsening; 37% vs 22% achieved ≥1-stage fibrosis improvement without NASH worsening | Accelerated approval based on surrogate; confirmatory phase 3 ongoing |
Dose and administration evidence
Approved labeled regimen
The label summary below is product-, indication-, and jurisdiction-specific; consult the full current label and a licensed clinician/pharmacist.
The entries summarize the cited US FDA labels for the named products and their approved indications.
Ozempic: Initiate 0.25 mg Administered into the tissue layer under the skin. Sumber definisi: Neutral gloss; usage context: Routes, devices, and absorption primer · Glosarium qwk × 4 wk, then 0.5 mg qwk; may increase to 1.0 mg qwk after ≥4 wk at 0.5 mg; 2.0 mg qwk approved (label update Jan 2022).
Wegovy: Initiate 0.25 mg SC qwk, titrate every 4 wk (0.5, 1.0, 1.7) to 2.4 mg qwk maintenance.
Rybelsus: 3 mg daily × 30 days, then 7 mg daily; may increase to 14 mg daily. Must be taken on an empty stomach with ≤120 mL water, after ≥30 min wait.
Studied regimens (not recommendations)
OASIS 4 evaluated oral semaglutide 25 mg daily for T2D; showed additional HbA1c reduction vs 14 mg.
Doses up to 4.5 mg SC qwk have been evaluated in early-phase obesity studies.
What is not established
Efficacy and safety in combination with tirzepatide or other incretin dual/triple agonists have not been studied.
Long-term weight maintenance beyond 4 years has not been reported.
No data exist for use in MASH without NASH diagnosis.
Safety
Established label risks
Boxed warning: Thyroid C-cell tumors. Rodent studies showed dose-dependent C-cell hyperplasia and tumors; human relevance is uncertain but monitoring required per label. Contraindicated in patients with personal/family history of medullary thyroid carcinoma or MEN 2.
Gastrointestinal: Nausea (44% Wegovy), vomiting, diarrhea, constipation. Dose-dependent; most pronounced during titration.
Pancreatitis: Rare (reported in clinical trials and postmarket); discontinue if suspected.
Acute kidney injury: Reported in setting of severe GI volume depletion.
Gallbladder disease: Increased incidence of cholelithiasis, especially with rapid weight loss.
Diabetic retinopathy: SUSTAIN-6 showed increased retinopathy complications (HR 1.76, 0.99–3.14), attributed to rapid glycemic improvement.
Hypoglycemia: Low risk unless combined with insulin or sulfonylureas.
Human-study signals
SELECT reported serious adverse events in 33.4% of semaglutide vs 36.4% An inactive comparator used in a controlled study. Sumber definisi: Neutral gloss; usage context: Evidence grading methodology · Glosarium; higher GI event rates.
Injection-site reactions (mild, self-limited) in 1–2% of clinical trial participants.
Unknowns and product-quality risks
Human thyroid C-cell tumor risk remains theoretically possible; long-term postmarket surveillance is ongoing.
Human pregnancy data remain insufficient and animal studies suggest fetal risk. This is not a blanket labeled contraindication: the 2026 Wegovy label says to discontinue treatment used for weight or cardiovascular-risk reduction when pregnancy is recognized, while MASH use during pregnancy is reserved for circumstances in which potential benefit justifies fetal risk.
Branded products only (Ozempic, Wegovy, Rybelsus); no FDA-approved generic. Compounded semaglutide (including semaglutide sodium) is not FDA-approved and carries risks of impurity, potency variation, and contamination. See the product quality and authenticity primer. FDA has issued warnings about compounded semaglutide.
Interactions and special populations
Delays gastric emptying, potentially reducing rate of absorption of oral medications (especially narrow-therapeutic-index drugs).
Insulin and sulfonylureas increase hypoglycemia risk; dose adjustment of these agents may be needed.
Renal impairment: No dose adjustment for mild/moderate; limited data with eGFR below 30 mL/min; caution with severe GI symptoms leading to volume depletion.
Hepatic impairment: No dose adjustment; limited data in severe hepatic impairment.
Pregnancy: product and indication matter. Wegovy used for weight or cardiovascular-risk reduction should be discontinued when pregnancy is recognized; for MASH, the label permits use only when potential benefit justifies fetal risk. Other semaglutide labels likewise warn of fetal risk; none should be summarized as a universal formal contraindication.
Regulatory, compounding, and sport notes
FDA boxed warning for thyroid C-cell tumors applies to all semaglutide brands.
Compounded semaglutide: FDA has repeatedly warned about compounding of "semaglutide sodium" and semaglutide produced without Novo Nordisk authorization. Counterfeit products have been identified.
The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. Sumber definisi: WADA and sport regulation brief · Glosarium: semaglutide is not prohibited, but its markers are included in the 2026 Monitoring Program in- and out-of-competition. Monitoring is not prohibition.
EU: EMA investigated Expansion of the abbreviation used in the monographs: glucagon-like peptide-1 receptor agonist. The atlas does not define the pharmacology of this class; see the monograph for what is documented about a specific compound. Sumber definisi: Neutral gloss; the abbreviation is printed on the tirzepatide monograph but the atlas does not define the class pharmacology · Glosarium suicide/self-harm signal (2023); found no causal link but recommends continued monitoring.
Evidence gaps
Long-term safety >5 years of semaglutide for weight management
Comparative effectiveness vs tirzepatide in head-to-head obesity trials beyond SURPASS
Role in primary CV prevention (SELECT was secondary prevention)
Confirmatory phase 3 data for MASH approval
Use in adolescents under 12 for obesity (STEP TEENS was 12–18)
Effects on non-alcoholic steatohepatitis (NASH) with fibrosis stage 3/4
Search notes
Databases and registries: PubMed, FDA Drugs@FDA, ClinicalTrials.gov, EMA EPAR, DailyMed, The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. Sumber definisi: WADA and sport regulation brief · Glosarium Prohibited List
Search terms: "semaglutide", "Ozempic", "Rybelsus", "Wegovy", "SUSTAIN", "SELECT", "STEP trial", "OASIS", "SOUL"
Last searched: 2026-08-06
Inclusion emphasis: Primary A study in which participants are assigned to the study material or a comparator by chance. Sumber definisi: Neutral gloss; usage context: Evidence grading methodology · Glosarium publications, FDA labels, FDA approval announcements, CVOTs
Sources
Marso SP et al. Semaglutide and cardiovascular outcomes in patients with type 2 diabetes (SUSTAIN-6). N Engl J Med. 2016;375(19):1834-1844. PMID: 27633186. https://doi.org/10.1056/NEJMoa1607141
Wilding JPH et al. Once-weekly semaglutide in adults with overweight or obesity (STEP 1). N Engl J Med. 2021;384(11):989-1002. PMID: 34154581. https://doi.org/10.1056/NEJMoa2032183
Lincoff AM et al. Semaglutide and cardiovascular outcomes in obesity without diabetes (SELECT). N Engl J Med. 2023;389(24):2221-2232. PMID: 37952131. https://doi.org/10.1056/NEJMoa2307563
FDA. Ozempic (semaglutide) injection label. NDA 209637. DailyMed. Accessed 2026-08-06. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=adec4fd2-6858-4c99-91d4-531f5f2a2d79
FDA. Wegovy (semaglutide) current label. NDA 215256. Revised 2026. https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/215256s025lbl.pdf
FDA. Rybelsus (semaglutide) tablets label. NDA 213051. DailyMed. Accessed 2026-08-06. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=27f15fac-7d98-4114-a2ec-92494a91da98
Drucker DJ. Mechanisms of action and therapeutic application of GLP-1 and GIP receptor agonists. Cell Metab. 2018;27(4):740-756. PMID: 29617641. https://doi.org/10.1016/j.cmet.2018.03.001
FDA. FDA approves Wegovy (semaglutide) for MASH. August 2025. https://www.fda.gov/drugs/news-events-human-drugs/fda-approves-treatment-serious-liver-disease-known-mash
ClinicalTrials.gov. Efficacy and Safety of Semaglutide in Subjects With MASH. NCT04822181. https://clinicaltrials.gov/study/NCT04822181
WADA. 2026 Monitoring Program. https://www.wada-ama.org/en/resources/monitoring-program