
Bottom line
Ipamorelin is a synthetic pentapeptide growth hormone secretagogue developed by Novo Nordisk in the 1990s. It acts as a selective ghrelin receptor (GHS-R1a) agonist, stimulating GH release without significant cortisol or prolactin elevation in the cited Evidence from in vitro or animal studies with no adequate human efficacy evidence — the atlas Grade D lane. Source de la définition: Evidence grading methodology · Glossaire characterization — a selectivity advantage over GHRP-2 and GHRP-6 in those animal models. The only published Phase II trial (postoperative ileus; 117 enrolled and 114 in the safety/modified intention-to-treat population) failed to meet its primary endpoint (time to first tolerated meal, p=0.15). No therapeutic product was ever approved. Ipamorelin is now marketed as a research chemical, predominantly for speculated GH-releasing and body-composition applications unsupported by adequate clinical trials.
Identity and composition
| Field | Verified information |
|---|---|
| Preferred name | Ipamorelin |
| Key aliases | NNC 26-0161, ipamorelin acetate |
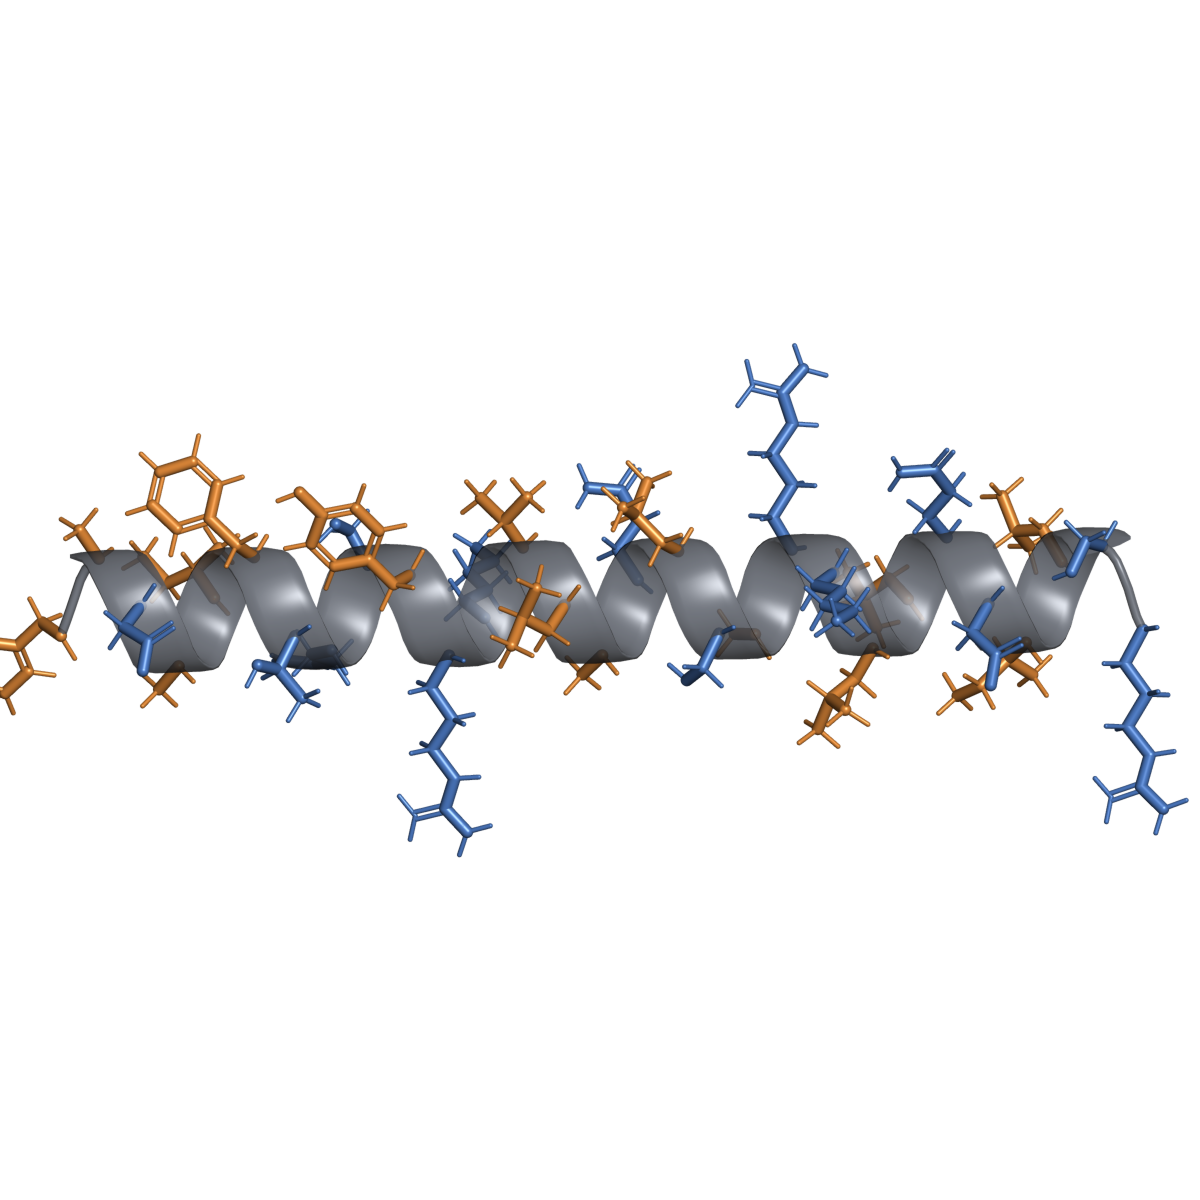
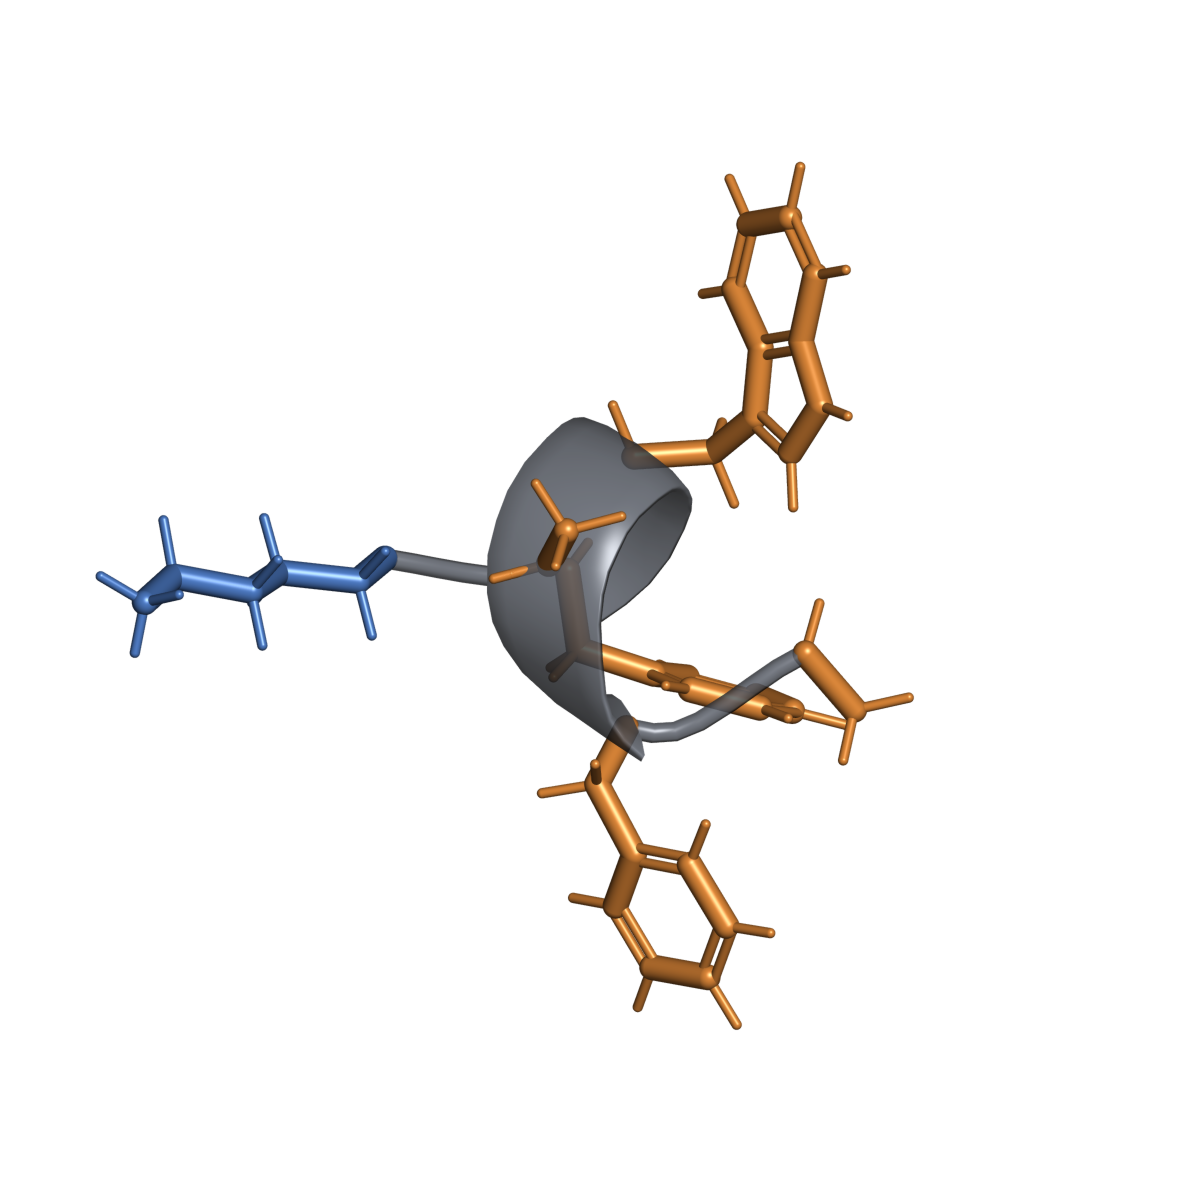
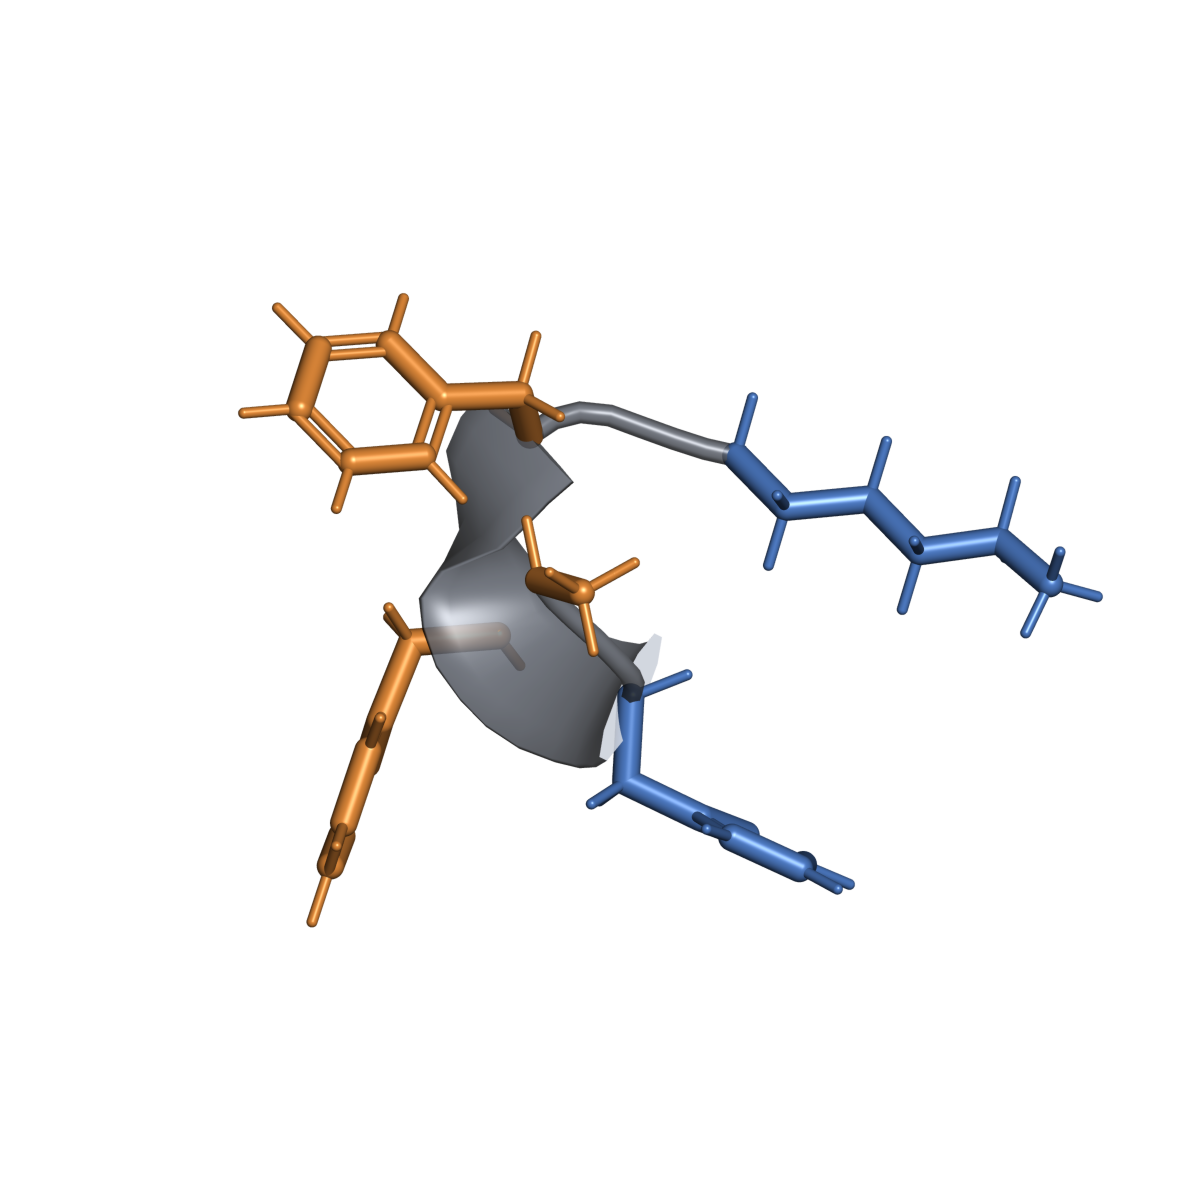
| Molecular/sequence identity | Synthetic pentapeptide: Aib-His-D-2-Nal-D-Phe-Lys-NH2 (where Aib = α-aminoisobutyric acid, D-2-Nal = D-2-naphthylalanine) |
| Modifications/form | Aib at position 1 confers DPP-IV resistance; C-terminal amidation |
| Stable identifiers | The record number of a compound in PubChem, the atlas's primary structure-asset source. A registry record or depiction does not authenticate a commercial sample. Source de la définition: Identity and structure assets methodology · Glossaire: 9831659; CAS: 170851-70-4 (free base); MW ~711 Da |
| Identity caveats | Ipamorelin is frequently confused with GHRP-2 or hexarelin in vendor listings. Verified by mass spec and sequence analysis. |
Development and approval status
| Jurisdiction | Status and indication | Product/source | As of |
|---|---|---|---|
| US (FDA) | No approved indication; Phase II discontinued | — | 2026-08-06 |
| EU (EMA) | No marketing authorization | — | 2026-08-06 |
- UNITED STATES
- US (FDA): No approved indication; Phase II discontinued
- EU/EEA
- EU (EMA): No marketing authorization
- UNITED KINGDOM
- No UNITED KINGDOM row is present in the source status table
- OTHER DOCUMENTED
- No OTHER DOCUMENTED row is present in the source status table
Sport status: Ipamorelin is explicitly listed under WADA section S2.2.4 as a growth-hormone secretagogue and is prohibited at all times. Analytical detectability depends on the validated method, specimen and target analyte.
Mechanism and pharmacology
Ipamorelin is a selective agonist at the growth hormone secretagogue receptor (GHS-R1a / ghrelin receptor). It stimulates GH release from the pituitary with minimal effect on ACTH, cortisol, or prolactin secretion — distinguishing it from GHRP-2, GHRP-6, and hexarelin. The The time for the amount of a substance in the body to fall by half. Source de la définition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossaire in humans is approximately 2 hours. GH peak occurs 15–30 minutes after Administered into the tissue layer under the skin. Source de la définition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossaire administration.
Evidence by claim
| Claim/indication | Stage | Grade | Best human evidence | Main result | Important limitations |
|---|---|---|---|---|---|
| Postoperative ileus | Phase II (failed) | X | Beck et al. 2014, PMID 25331030; 117 enrolled, 114 in the safety/modified intention-to-treat population | No significant difference in time to first tolerated meal (25.3 vs 32.6 h, p=0.15) | Failed primary endpoint; small sample; single study |
| GH release (pharmacology) | Phase I | C | Novo Nordisk early-phase studies | Dose-dependent GH elevation; selectivity confirmed | Pharmacology only; no efficacy endpoints |
| GH deficiency | Phase II (discontinued) | D | Limited published data | Development discontinued | No completed Phase II publication |
| Body composition | Marketing | E | No controlled trials | No adequate evidence | Marketing extrapolation only |
- AGrade A: Établi pour une utilisation indiquée spécifique
- BGrade B: Preuve humaine modérée
- CGrade C: Preuve humaine préliminaire
- DGrade D: Préclinique uniquement
- EGrade E: Affirmation anecdotique/commerciale
- XGrade X: Les preuves contredisent ou ne soutiennent pas l'affirmation
Text alternative for the claim-evidence diagram. Each grade is defined below:
- A — Established for a specific labeled use
- 0 claims
- B — Moderate human evidence
- 0 claims
- C — Preliminary human evidence
- 1 claim: GH release (pharmacology)
- D — Preclinical only
- 1 claim: GH deficiency
- E — Anecdotal/marketing claim
- 1 claim: Body composition
- X — Evidence contradicts or does not support the claim
- 1 claim: Postoperative ileus
Key studies
| Study | Design/population | Exposure studied | Endpoints and result | Limitations |
|---|---|---|---|---|
| Beck et al., 2014; PMID 25331030 (NCT00672074) | Multicenter, Neither participants nor investigators know who receives the study material or the comparator. Source de la définition: Neutral gloss; usage context: Evidence grading methodology · Glossaire, An inactive comparator used in a controlled study. Source de la définition: Neutral gloss; usage context: Evidence grading methodology · Glossaire-controlled Phase II trial; 117 adults enrolled after small- or large-bowel resection, with 114 in the safety/modified intention-to-treat population | 0.03 mg/kg Administered into a vein. Source de la définition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossaire twice daily from postoperative day 1 through day 7 or hospital discharge | Median time to first tolerated meal 25.3 vs 32.6 hours (p=0.15) | Failed primary endpoint; IV route; short perioperative window only |
| Raun et al., 1998 (Evidence from in vitro or animal studies with no adequate human efficacy evidence — the atlas Grade D lane. Source de la définition: Evidence grading methodology · Glossaire characterization) | Rat pharmacology | Various Administered into the tissue layer under the skin. Source de la définition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossaire doses | Potent GH release; minimal cortisol | Animal data; cannot extrapolate human efficacy |
Dose and administration evidence
Approved labeled regimen
Not applicable.
Studied regimens (not recommendations)
No established or recommended human dose. The failed Phase II postoperative study used 0.03 mg/kg Administered into a vein. Source de la définition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossaire twice daily from postoperative day 1 through day 7 or hospital discharge. That protocol-specific exposure was not a dose recommendation and did not establish efficacy.
What is not established
Effective therapeutic dose for any indication
Long-term dosing protocol
Dose for body composition or anti-aging claims
Safety beyond the short published perioperative study
Safety
Established label risks
No approved label exists.
Human-study signals
In the Phase II postoperative-ileus trial, treatment-emergent adverse events occurred in 87.5% of the ipamorelin group versus 94.8% of the An inactive comparator used in a controlled study. Source de la définition: Neutral gloss; usage context: Evidence grading methodology · Glossaire group. The trial context involved major bowel surgery, so the event rates do not isolate effects attributable to ipamorelin.
The FDA has identified serious safety concerns for ipamorelin based on a different context of use: serious adverse events, including death, were reported in an Administered into a vein. Source de la définition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossaire gastric-motility study. The FDA noted these events where uncertainty exists regarding causality and whether the risk extends to other routes of administration (e.g., Administered into the tissue layer under the skin. Source de la définition: Neutral gloss; usage context: Routes, devices, and absorption primer · Glossaire). This safety signal is specific to the IV route and the gastric-motility indication and may not generalize.
Unknowns and product-quality risks
Long-term safety beyond 7 days has not been studied. Theoretical risks include: GH/IGF-1 elevation promoting neoplasia; insulin resistance; fluid retention; carpal tunnel syndrome. Research-grade material purity and identity are not regulated.
Interactions and special populations
No human drug-interaction data exist. Contraindications would theoretically include active malignancy, pregnancy, and known hypersensitivity.
Regulatory, compounding, and sport notes
Ipamorelin is explicitly listed under The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. Source de la définition: WADA and sport regulation brief · Glossaire section S2.2.4 as a growth-hormone secretagogue and is prohibited at all times. Analytical detectability depends on the validated method, specimen and target analyte.
Evidence gaps
Only one published human efficacy trial, which failed
No long-term safety or efficacy data
No studies in elderly, female, or pediatric populations for therapeutic indications
No comparative studies against approved GH or GHRH therapies
No dose-finding for non-IV routes in therapeutic context
Search notes
Databases and registries: PubMed, ClinicalTrials.gov, FDA Drugs@FDA
Search terms: "ipamorelin", "NNC 26-0161", "NCT00672074"
Last searched: 2026-08-06
Inclusion emphasis: Human clinical trials; primary peer-reviewed Evidence from in vitro or animal studies with no adequate human efficacy evidence — the atlas Grade D lane. Source de la définition: Evidence grading methodology · Glossaire pharmacology
Sources
NCT00672074. Safety and efficacy of ipamorelin for management of postoperative ileus. ClinicalTrials.gov. https://clinicaltrials.gov/study/NCT00672074
Beck DE, Sweeney WB, McCarter MD; Ipamorelin 201 Study Group. Prospective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients. Int J Colorectal Dis. 2014;29(12):1527-1534. PMID 25331030. https://pubmed.ncbi.nlm.nih.gov/25331030/
Raun K et al. Ipamorelin, the first selective growth hormone secretagogue. Eur J Endocrinol. 1998;139(5):552-561. PMID 9849822. https://pubmed.ncbi.nlm.nih.gov/9849822/
FDA. Drugs@FDA. No listing for ipamorelin. https://www.accessdata.fda.gov/scripts/cder/daf/
WADA Prohibited List 2026. https://www.wada-ama.org/en/prohibited-list
PubChem CID 9831659. Ipamorelin. https://pubchem.ncbi.nlm.nih.gov/compound/9831659
FDA. Certain bulk drug substances for use in compounding may present significant safety risks. Ipamorelin entry. Accessed 2026-08-06. https://www.fda.gov/drugs/human-drug-compounding/certain-bulk-drug-substances-use-compounding-may-present-significant-safety-risks