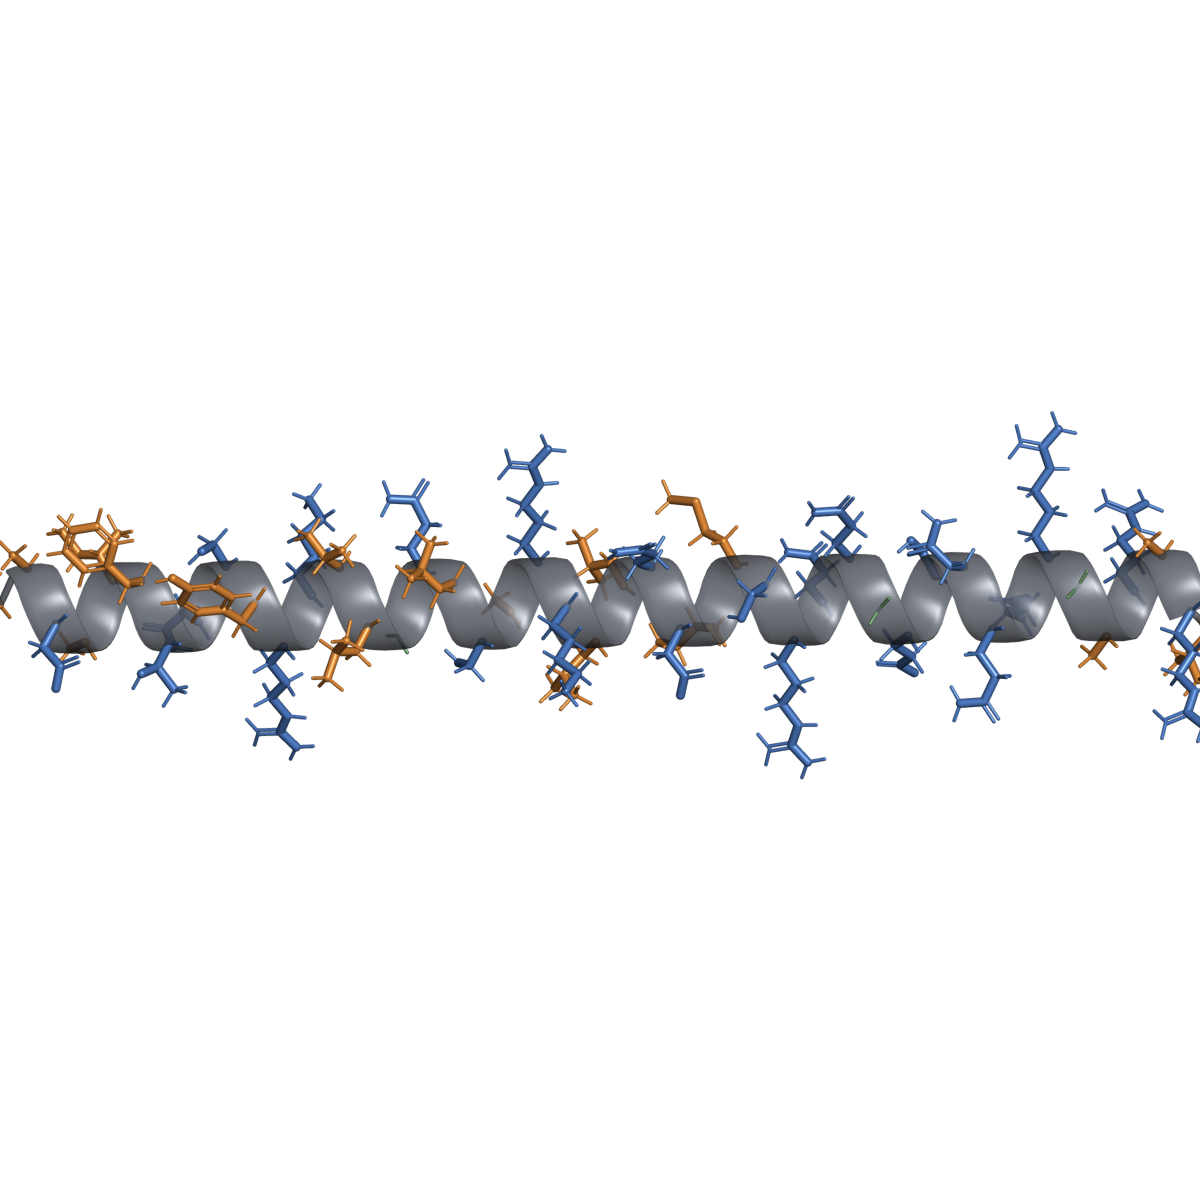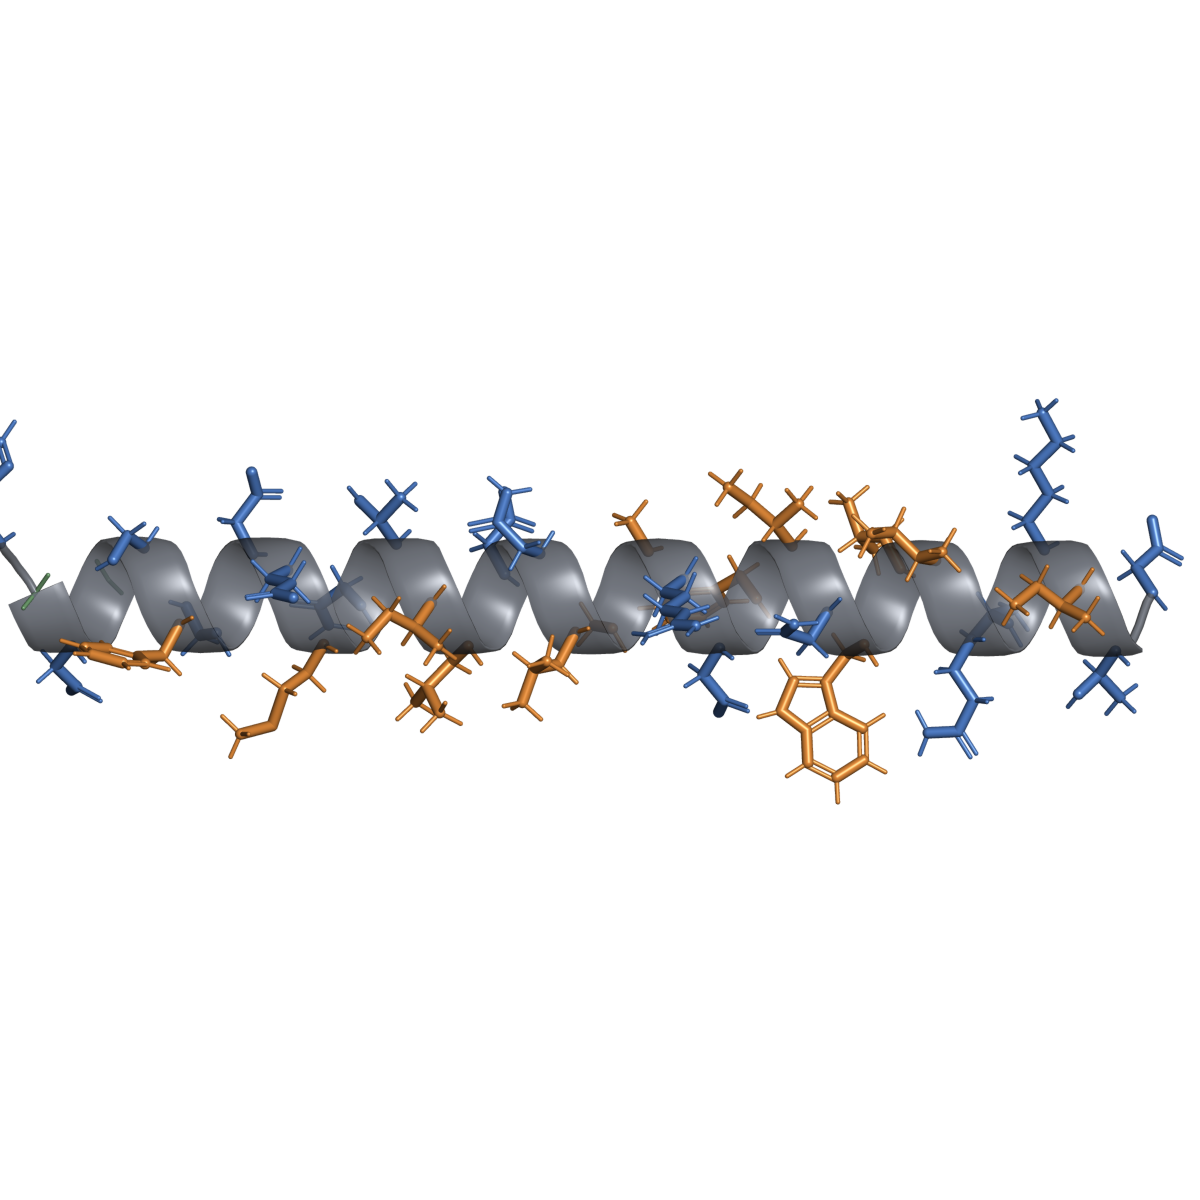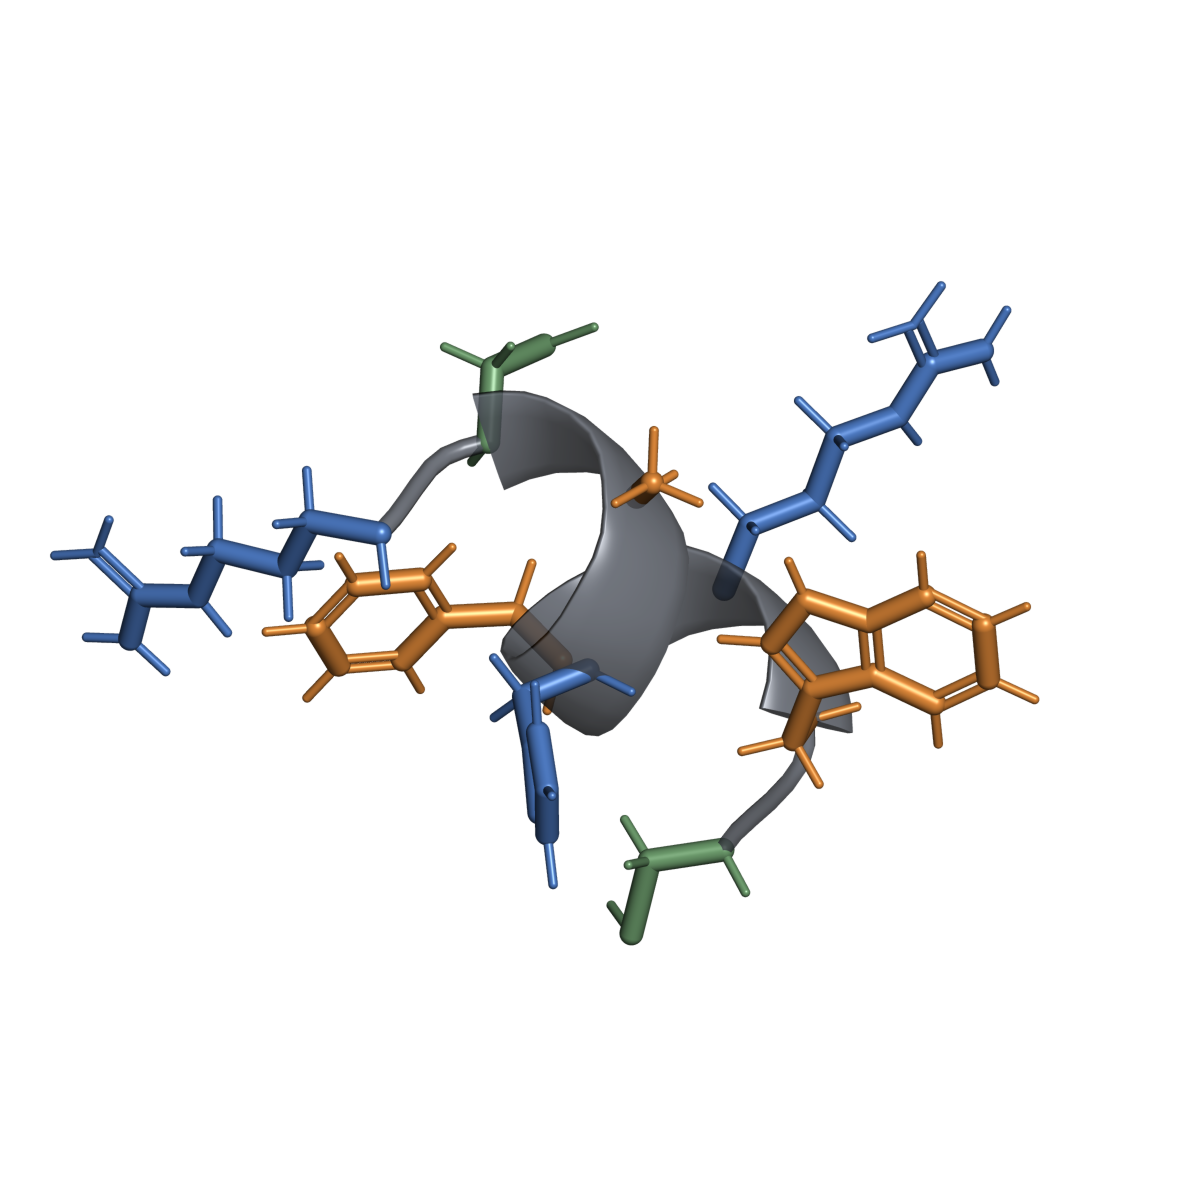

Bottom line
MC4R agonist approved for three rare genetic obesity disorders. Not indicated for general obesity. Reduces hunger and body weight in patients with impaired melanocortin signaling. Skin hyperpigmentation is a near-universal pharmacodynamic effect.
Identity and composition
| Field | Verified information |
|---|---|
| Preferred name | Setmelanotide |
| Key aliases | Imcivree, RM-493 |
| Molecular/sequence identity | Ac-Arg-Cys-D-Ala-His-D-Phe-Arg-Trp-Cys-NH2; 8-amino-acid cyclic peptide |
| Modifications/form | Cyclic (2→8) disulfide bridge between Cys2 and Cys8; N-terminal acetylation; C-terminal cysteinamide; D-Ala3 and D-Phe5; acetate salt in the labeled product |
| Stable identifiers | The record number of a compound in PubChem, the atlas's primary structure-asset source. A registry record or depiction does not authenticate a commercial sample. Fuente de la definición: Identity and structure assets methodology · Glosario: 11993702; CAS 920014-72-8 (free base); UNII N7T15V1FUY; DrugBank DB11700; FDA NDA 213793 |
| Identity caveats | Residue numbering here follows the complete eight-residue peptide: D-Ala is residue 3 and D-Phe is residue 5. Residual MC1R agonism accounts for the melanocytic effect (skin darkening). |
Development and approval status
| Jurisdiction | Status and indication | Product/source | As of |
|---|---|---|---|
| US (FDA) | Approved Nov 2020 — POMC/PCSK1/LEPR deficiency obesity (age 6+); Jun 2022 — Bardet-Biedl syndrome (age 2+); Mar 2026 — acquired hypothalamic obesity (age 4+) | Imcivree (Rhythm Pharmaceuticals) | Aug 2026 |
| EU (EMA) | Approved — same core indications | Imcivree (Rhythm Pharmaceuticals) | Aug 2026 |
| UK (MHRA) | Approved — POMC/LEPR deficiency obesity | Imcivree | Aug 2026 |
- UNITED STATES
- US (FDA): Approved Nov 2020 — POMC/PCSK1/LEPR deficiency obesity (age 6+); Jun 2022 — Bardet-Biedl syndrome (age 2+); Mar 2026 — acquired hypothalamic obesity (age 4+)
- EU/EEA
- EU (EMA): Approved — same core indications
- UNITED KINGDOM
- UK (MHRA): Approved — POMC/LEPR deficiency obesity
- OTHER DOCUMENTED
- No OTHER DOCUMENTED row is present in the source status table
Sport status: WADA status: not prohibited.
Mechanism and pharmacology
Setmelanotide is a potent MC4 receptor agonist that restores signaling in the hypothalamic melanocortin pathway downstream of POMC/PCSK1/LEPR dysfunction. MC4R activation reduces appetite and increases energy expenditure. The cyclic structure and D-Phe substitution confer high MC4R potency with reduced MC1R selectivity (though residual MC1R agonism causes hyperpigmentation).
Evidence by claim
| Claim/indication | Stage | Grade | Best human evidence | Main result | Important limitations |
|---|---|---|---|---|---|
| Weight loss in POMC/PCSK1/LEPR deficiency obesity | Approved | A | A study without a separate comparison group. Fuente de la definición: Neutral gloss; usage context: Evidence grading methodology · Glosario A study in which participants and investigators know what is administered. Fuente de la definición: Neutral gloss; usage context: Evidence grading methodology · Glosario Phase 3 (n=10–12 per cohort) | 80–100% lost ≥10% body weight at 52 wk; hunger scores reduced | Very small genetic cohorts; open-label design; authors corrected to Clément et al. (2020) |
| Weight reduction in Bardet-Biedl syndrome | Approved | A | Randomised, Neither participants nor investigators know who receives the study material or the comparator. Fuente de la definición: Neutral gloss; usage context: Evidence grading methodology · Glosario, An inactive comparator used in a controlled study. Fuente de la definición: Neutral gloss; usage context: Evidence grading methodology · Glosario-controlled Phase 3 (n=38, BBS cohort) | 32% lost ≥10% body weight at 52 wk | Small; heterogeneous genetic BBS subtypes |
| Weight reduction in acquired hypothalamic obesity | Approved [1] | A | Randomized, double-blind, placebo-controlled Phase 3 NCT05774756 | Placebo-adjusted mean BMI change −18.40% after 52 weeks at the therapeutic regimen | Recent indication; long-term comparative outcome data remain limited |
| General obesity (non-genetic) | Phase 2 (terminated) | X | A study in which participants are assigned to the study material or a comparator by chance. Fuente de la definición: Neutral gloss; usage context: Evidence grading methodology · Glosario in common obesity (n=223) | Did not meet efficacy threshold; FDA explicitly excludes this use | Failed for common obesity; indication strictly limited |
- AGrado A: Establecido para un uso etiquetado específico
- BGrado B: Evidencia humana moderada
- CGrado C: Evidencia humana preliminar
- DGrado D: Solo preclínico
- EGrado E: Afirmación anecdótica/de marketing
- XGrado X: La evidencia contradice o no respalda la afirmación
Text alternative for the claim-evidence diagram. Each grade is defined below:
- A — Established for a specific labeled use
- 3 claims: Weight loss in POMC/PCSK1/LEPR deficiency obesity; Weight reduction in Bardet-Biedl syndrome; Weight reduction in acquired hypothalamic obesity
- B — Moderate human evidence
- 0 claims
- C — Preliminary human evidence
- 0 claims
- D — Preclinical only
- 0 claims
- E — Anecdotal/marketing claim
- 0 claims
- X — Evidence contradicts or does not support the claim
- 1 claim: General obesity (non-genetic)
Key studies
| Study | Design/population | Exposure studied | Endpoints and result | Limitations |
|---|---|---|---|---|
| Clément K, et al. (Lancet Diabetes Endocrinol 2020) — POMC/LEPR deficiency | A study in which participants and investigators know what is administered. Fuente de la definición: Neutral gloss; usage context: Evidence grading methodology · Glosario Phase 3; 12 POMC, 11 LEPR deficiency | Setmelanotide Administered into the tissue layer under the skin. Fuente de la definición: Neutral gloss; usage context: Routes, devices, and absorption primer · Glosario, titrated to 3 mg qd | 80% POMC and 45% LEPR lost ≥10% body weight | Very small; open-label |
| Haws RM, et al. (Lancet Diabetes Endocrinol 2022) — BBS | Randomised, Neither participants nor investigators know who receives the study material or the comparator. Fuente de la definición: Neutral gloss; usage context: Evidence grading methodology · Glosario, An inactive comparator used in a controlled study. Fuente de la definición: Neutral gloss; usage context: Evidence grading methodology · Glosario-controlled Phase 3; 38 BBS participants | Setmelanotide SC, titrated to 3 mg qd | 32% with ≥10% weight loss at 52 wk; hunger score reduced ~30% | Small sample; BBS is heterogeneous |
| NCT05774756 — acquired hypothalamic obesity | Randomized, double-blind, placebo-controlled, 56–60 wk; 142 patients included in the efficacy analysis, age 4+ [1] | Product-label therapeutic regimen versus placebo | Placebo-adjusted mean BMI change −18.40% at 52 wk; more treated patients reached 5%, 10%, and 15% BMI-reduction thresholds | Product-label analysis for a newly approved rare-disease population |
Dose and administration evidence
Approved labeled regimen
The label summary below is product-, indication-, and jurisdiction-specific; consult the full current label and a licensed clinician/pharmacist.
The entries summarize the cited US FDA Imcivree label for the named rare-disease indications and age groups.
Acquired hypothalamic obesity (age 4+): 0.5 mg Administered into the tissue layer under the skin. Fuente de la definición: Neutral gloss; usage context: Routes, devices, and absorption primer · Glosario once daily is the labeled starting dose for 2 weeks. The subsequent titration and, for ages 4 to under 6, maintenance regimen follow the label's age/weight tables.
BBS or POMC/PCSK1/LEPR deficiency, age 12+: 2 mg SC once daily for 2 weeks is the labeled starting dose.
BBS or POMC/PCSK1/LEPR deficiency, age 6 to under 12: 1 mg SC once daily for 2 weeks is the labeled starting dose.
BBS or POMC/PCSK1/LEPR deficiency, age 2 to under 6: 0.5 mg SC once daily for 2 weeks, followed by the label's weight-based table.
Maintenance: 3 mg SC once daily for patients age 6+ across approved indications; younger-patient maintenance is weight-based. Severe renal impairment has separate lower tables and is not a “no adjustment” population; the product is not recommended in end-stage renal disease or in acquired hypothalamic obesity with severe renal impairment.
This is a label summary, not a substitute for the current indication-, age-, weight-, tolerability-, and renal-function tables.
Studied regimens (not recommendations)
Earlier studies used multiple titration exposures; these do not override the current indication- and age-specific label.
What is not established
Not for general obesity or obesity without a confirmed genetic defect in the melanocortin pathway.
Long-term (beyond 1–2 years) safety/efficacy not established.
Human pregnancy data are inadequate; the current US label does not classify pregnancy as a formal contraindication.
Safety
Established label risks
Skin hyperpigmentation (up to 100% of treated patients) due to MC1R activation — reversible upon discontinuation.
Nausea (54%), vomiting, diarrhea, abdominal pain.
Injection site reactions (including erythema, pruritus).
Spontaneous penile erections (males, ~10%).
Depression, suicidal ideation (monitor).
Human-study signals
No evidence of valve disease or structural heart effects.
No hypoglycemia signal.
Elevations in heart rate and BP observed in early studies but not in Phase 3.
Unknowns and product-quality risks
Long-term malignancy risk (MC1R activation linked to melanocyte activity; theoretical).
Reproductive safety: no adequate human data.
In vitro data on MC2R (ACTH receptor) cross-reactivity minimal, but HPA axis effects not fully characterized.
Interactions and special populations
No formal drug interaction studies.
Concomitant insulin secretagogues: monitor glucose (possible insulin resistance improvement).
Mild and moderate renal impairment use the usual indication-specific regimen. Severe impairment uses separate lower label tables for some genetic/BBS populations; end-stage renal disease and acquired hypothalamic obesity with severe impairment are not recommended populations.
Not recommended in pregnancy or breastfeeding.
Regulatory, compounding, and sport notes
FDA-approved under standard prescribing; no REMS program. Restricted to specialty pharmacies under the manufacturer's distribution program.
Orphan drug designation for POMC deficiency, LEPR deficiency, BBS, and hypothalamic obesity.
The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. Fuente de la definición: WADA and sport regulation brief · Glosario status: not prohibited.
Evidence gaps
Long-term outcomes (>2 years) not published.
The small genetic-deficiency and BBS cohorts have limited or no controlled evidence, while the 2026 acquired-hypothalamic-obesity indication has a randomized An inactive comparator used in a controlled study. Fuente de la definición: Neutral gloss; usage context: Evidence grading methodology · Glosario-controlled trial.
No studies directly comparing different genetic subtypes within BBS.
Effect on CV morbidity and mortality unknown.
Search notes
Databases and registries: DailyMed (Imcivree label), ClinicalTrials.gov, PubMed, EMA EPAR, FDA.
Search terms: "setmelanotide" OR "Imcivree" OR "RM-493" OR "MC4R agonist".
Last searched: 2026-08-06.
Inclusion emphasis: FDA/EMA prescribing information, pivotal Phase 3 studies, approved-indication literature.
Sources
Imcivree (setmelanotide) prescribing information. FDA/DailyMed. Revised April 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?lang=en&setid=70c3ccf7-4df0-4c75-ba07-fede9970c8d9
Clément K, van den Akker E, Argente J, et al. Efficacy and safety of setmelanotide, an MC4R agonist, in individuals with severe obesity due to LEPR or POMC deficiency: single-arm, open-label, multicentre, phase 3 trials. Lancet Diabetes Endocrinol. 2020;8(12):960–970. DOI: 10.1016/S2213-8587(20)30364-8. PMID: 33137293. https://doi.org/10.1016/S2213-8587(20)30364-8
Haws RM, et al. Efficacy and safety of setmelanotide, a melanocortin-4 receptor agonist, in patients with Bardet-Biedl syndrome and Alström syndrome: a multicentre, randomised, double-blind, placebo-controlled, phase 3 trial with an open-label period. Lancet Diabetes Endocrinol. 2022;10(12):859–868. DOI: 10.1016/S2213-8587(22)00277-7. PMID: 36356613. https://doi.org/10.1016/S2213-8587(22)00277-7
ClinicalTrials.gov. NCT05774756, acquired hypothalamic obesity. https://clinicaltrials.gov/study/NCT05774756
DrugBank DB11700 — Setmelanotide. https://go.drugbank.com/drugs/DB11700. Accessed 2026-08-06.
EMA. Imcivree (setmelanotide) EPAR. EMA/CHMP/508636/2024. https://www.ema.europa.eu/en/medicines/human/EPAR/imcivree
PubChem CID 11993702 — Setmelanotide. https://pubchem.ncbi.nlm.nih.gov/compound/11993702. Accessed 2026-08-06.