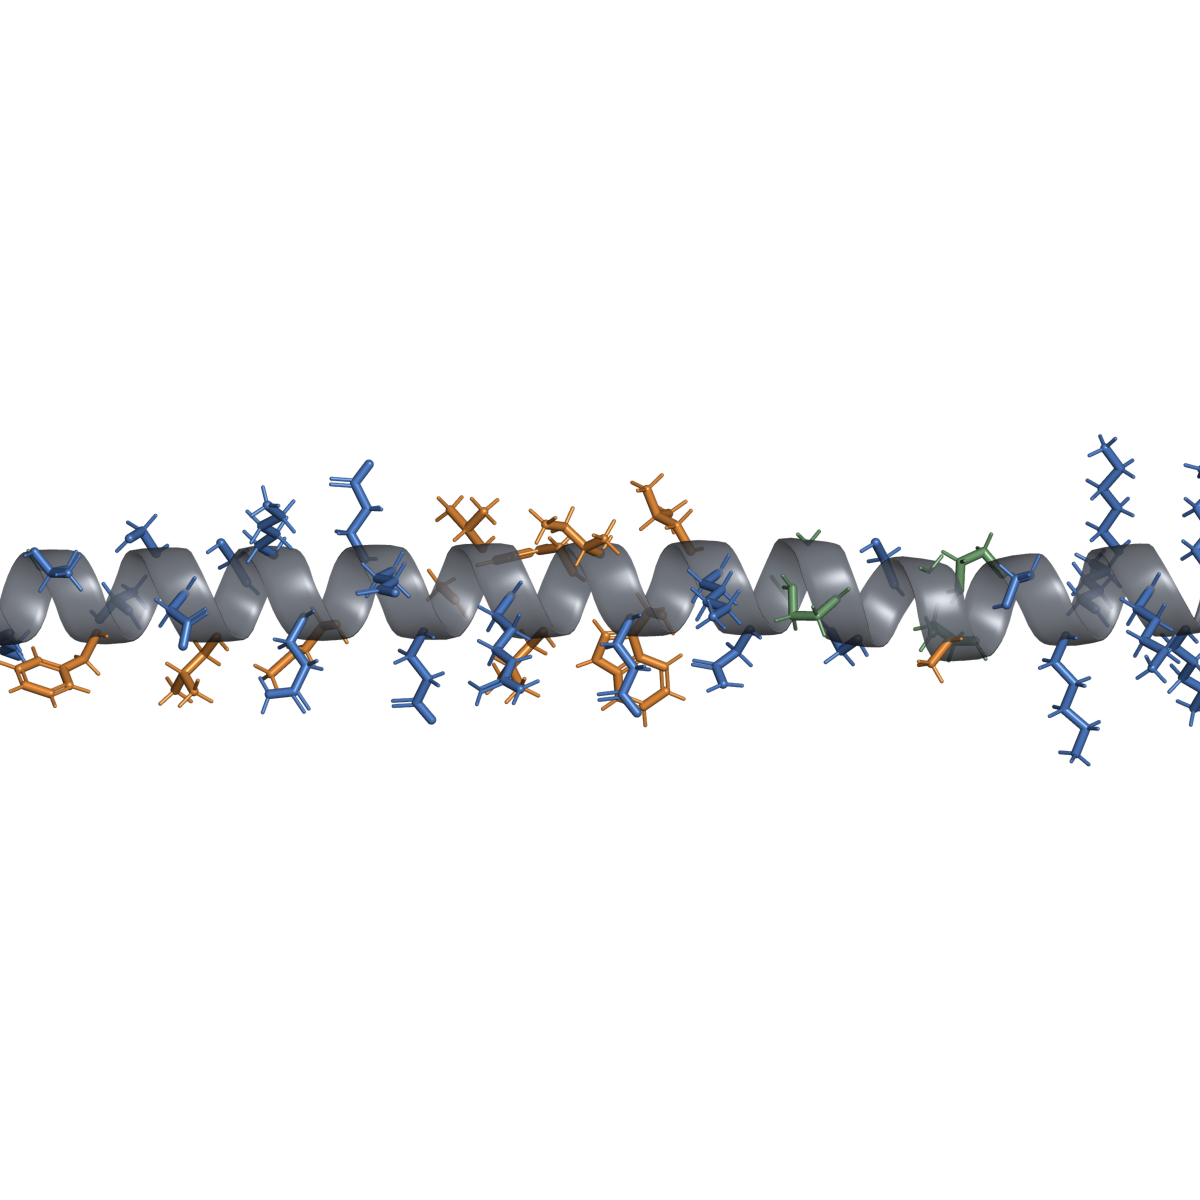Bottom line
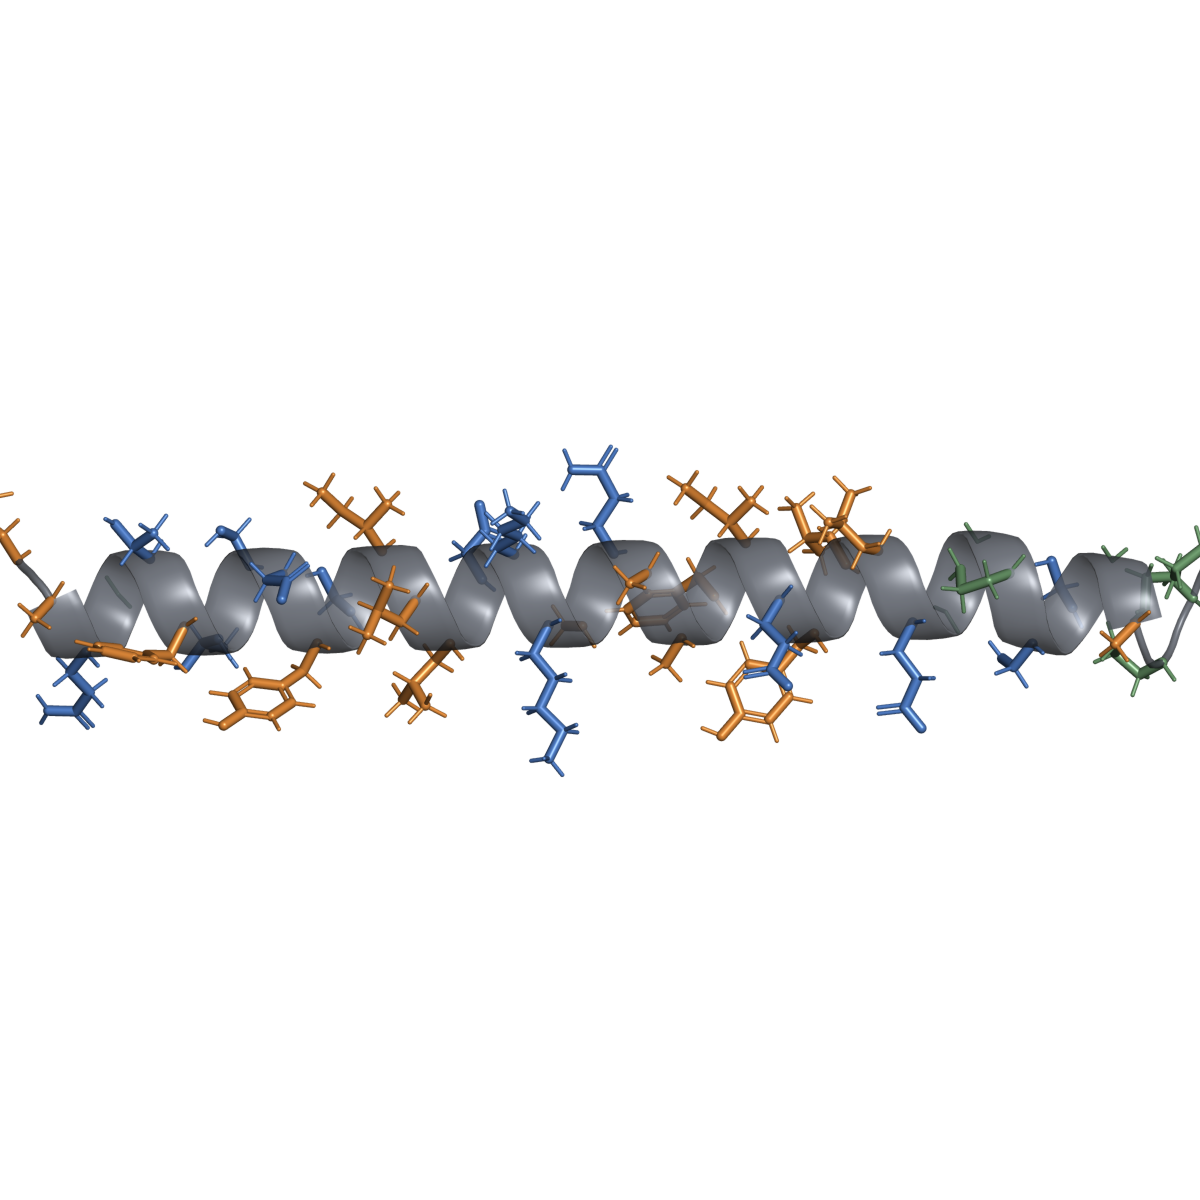
Tirzepatide (Mounjaro, Zepbound) is a 39-amino-acid synthetic linear peptide and the first approved dual glucose-dependent insulinotropic polypeptide (GIP) and glucagon-like peptide-1 (GLP-1) receptor agonist.
Approved by FDA for T2D (May 2022), chronic weight management (Nov 2023), and moderate-to-severe OSA with obesity (December 2024). In SURPASS trials it demonstrated superior glycemic control versus semaglutide 1 mg and dulaglutide; in SURMOUNT-1 it produced mean weight loss of 22.5% at 72 weeks. Approved for pediatric T2D (age 10+) in 2025. See the evidence grading methodology for an explanation of Grade A: Established for a specific labeled use — current approval plus adequate controlled trials and post-market context. 定义来源: Evidence grading methodology · 术语表 evidence.
Identity and composition
| Field | Verified information |
|---|---|
| Preferred name | Tirzepatide |
| Key aliases | LY3298176; Mounjaro; Zepbound |
| Molecular/sequence identity | 39-amino-acid linear peptide with a C20 fatty di-acid (eicosanedioic acid) moiety conjugated to the Lys residue at position 20 via a gamma-glutamic acid linker |
| Modifications/form | Solution for Administered into the tissue layer under the skin. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 injection in single-dose pens; preserved with metacresol |
| Stable identifiers | CAS: 2023788-19-2; The record number of a compound in PubChem, the atlas's primary structure-asset source. A registry record or depiction does not authenticate a commercial sample. 定义来源: Identity and structure assets methodology · 术语表: 156588324; DrugBank: DB15171; UNII: 7C4R8AT8BN |
| Identity caveats | None identified. Sequence and modification consistently reported across FDA labels and patent filings. |
Development and approval status
| Jurisdiction | Status and indication | Product/source | As of |
|---|---|---|---|
| US (FDA) | Approved for glycemic control in T2D (adjunct to diet and exercise) | Mounjaro | May 2022 |
| US (FDA) | Approved for chronic weight management (BMI ≥30, or ≥27 with ≥1 weight-related comorbidity) | Zepbound | Nov 2023 |
| US (FDA) | Approved for moderate-to-severe OSA with obesity | Zepbound | Dec 2024 |
| EU (EMA) | Approved for T2D (Mounjaro, Sep 2022) and weight management (Mounjaro, 2023 expanded) | Mounjaro | 2023 |
| US (FDA) | Approved for pediatric T2D (age 10–17) | Mounjaro | 2025 |
- UNITED STATES
- US (FDA): Approved for glycemic control in T2D (adjunct to diet and exercise); US (FDA): Approved for chronic weight management (BMI ≥30, or ≥27 with ≥1 weight-related comorbidity); US (FDA): Approved for moderate-to-severe OSA with obesity; US (FDA): Approved for pediatric T2D (age 10–17)
- EU/EEA
- EU (EMA): Approved for T2D (Mounjaro, Sep 2022) and weight management (Mounjaro, 2023 expanded)
- UNITED KINGDOM
- No UNITED KINGDOM row is present in the source status table
- OTHER DOCUMENTED
- No OTHER DOCUMENTED row is present in the source status table
Sport status: WADA: Tirzepatide is not prohibited, but its markers are included in the 2026 Monitoring Program in- and out-of-competition. Monitoring is not prohibition. See the WADA and sport regulation brief.
Mechanism and pharmacology
Dual receptor agonism
Tirzepatide is a balanced dual agonist at the GIP and GLP-1 receptors. In vitro binding affinity is approximately equal at both receptors; in vivo the GIP component is hypothesized to complement GLP-1-mediated effects on insulin secretion, glucagon suppression, and gastric emptying.
How a substance is absorbed, distributed, metabolized, and eliminated by the body; atlas pages report pharmacokinetic data such as half-life, metabolism, and clearance. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表
The C20 fatty-diacid moiety enables albumin binding, supporting a once-weekly subcutaneous half-life of approximately 5 days.
Physiologic effects
Central GLP-1 receptor activation in the hypothalamus contributes to appetite suppression and weight loss, while GIP agonism may mitigate the nausea typically associated with GLP-1 monotherapy.
Evidence by claim
See the evidence grading methodology for an explanation of Grade letters.
| Claim/indication | Stage | Grade | Best human evidence | Main result | Important limitations |
|---|---|---|---|---|---|
| Glycemic control in T2D | Approved | A | SURPASS program (Phase 3): seven trials, n>12,000 | HbA1c reduction superior to An inactive comparator used in a controlled study. 定义来源: Neutral gloss; usage context: Evidence grading methodology · 术语表, semaglutide 1 mg, dulaglutide, and insulin glargine | Active comparators did not include semaglutide 2.0 mg; limited long-term durability data beyond 2 years |
| Chronic weight management | Approved [1] | A | SURMOUNT-1 (n=2,539, 72 wk) | Mean weight loss 22.5% (15 mg); 57% achieved ≥20% loss | Limited to adults without T2D in the primary analysis; 2-year extension data from SURMOUNT-3/4 |
| OSA with obesity | Approved [1] | B | SURMOUNT-OSA (n=469, 52 wk) | AHI reduction 27–30 events/h (60–63% relative reduction) | Device-naive and CPAP-experienced subgroups studied separately; long-term CV outcomes not yet reported |
| Pediatric T2D (10–17 yr) | Approved | A | SURPASS-PEDS | Significant HbA1c reduction vs placebo in adolescents | Single trial; sample size limited (n~150) |
Text alternative for the claim-evidence diagram. Each grade is defined below:
- A — Established for a specific labeled use
- 3 claims: Glycemic control in T2D; Chronic weight management; Pediatric T2D (10–17 yr)
- B — Moderate human evidence
- 1 claim: OSA with obesity
- C — Preliminary human evidence
- 0 claims
- D — Preclinical only
- 0 claims
- E — Anecdotal/marketing claim
- 0 claims
- X — Evidence contradicts or does not support the claim
- 0 claims
Key studies
| Study | Design/population | Exposure studied | Endpoints and result | Limitations |
|---|---|---|---|---|
| SURPASS-2 (NCT03987919) | Phase 3, A study in which participants are assigned to the study material or a comparator by chance. 定义来源: Neutral gloss; usage context: Evidence grading methodology · 术语表, 40 wk; T2D (n=1,879) [1] | Tirzepatide 5, 10, 15 mg vs semaglutide 1 mg Administered into the tissue layer under the skin. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 qwk | HbA1c change: −2.01%, −2.24%, −2.30% vs −1.86%; weight: −7.6, −11.2, −12.9 vs −6.3 kg | Semaglutide comparator only at 1.0 mg (max dose 2.0 mg) |
| SURMOUNT-1 (NCT04184622) | Phase 3, RCT, 72 wk; adults with BMI ≥30 or ≥27 + comorbidity (n=2,539) [1] | Tirzepatide 5, 10, 15 mg vs An inactive comparator used in a controlled study. 定义来源: Neutral gloss; usage context: Evidence grading methodology · 术语表 SC qwk | Mean weight loss −16.0%, −21.4%, −22.5% vs −2.4%; 15 mg: 57% achieved ≥20% loss | A study in which participants and investigators know what is administered. 定义来源: Neutral gloss; usage context: Evidence grading methodology · 术语表 extension phase not blinded; participants with T2D excluded |
| SURMOUNT-OSA (NCT05412004) | Phase 3, RCT, 52 wk; moderate-severe OSA + obesity (n=469) [1] | Tirzepatide 10/15 mg vs placebo SC qwk | AHI reduction −27.0 to −30.4 events/h (60–63% relative reduction) | Two subpopulations analyzed separately; no cardiovascular outcome data yet |
| SURPASS-CVOT (NCT04255433) | Phase 3, CV outcomes RCT; T2D with established CVD (n=13,000) [1] | Tirzepatide vs dulaglutide SC qwk | MACE-4 non-inferior; all-cause mortality numerical reduction | Detailed results pending publication; interim data from press releases |
Dose and administration evidence
Approved labeled regimen
The label summary below is product-, indication-, and jurisdiction-specific; consult the full current label and a licensed clinician/pharmacist.
Mounjaro (T2D): Initiate at 2.5 mg Administered into the tissue layer under the skin. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 once weekly; increase to 5 mg after 4 weeks. If additional glycemic control needed, may escalate in 2.5 mg increments after ≥4 weeks to max 15 mg once weekly. 2.5 mg is titration only; therapeutic doses are 5/7.5/10/12.5/15 mg.
Zepbound (weight management): Same titration schedule. Continue 5, 10, or 15 mg as the maintenance dose.
Zepbound (OSA): Same titration schedule; 10 or 15 mg maintenance.
Studied regimens (not recommendations)
All SURPASS and SURMOUNT trials used once-weekly subcutaneous dosing starting at 2.5 mg with 4-week dose-escalation steps. Some Phase 1 and 2 studies also explored fixed-dose and rapid-titration regimens; these are not included in the approved label.
What is not established
No data support safety or efficacy above 15 mg weekly. Tirzepatide has not been studied in combination with other incretin-based therapies. No data on compounded, oral, or non-subcutaneous routes.
Safety
Established label risks
Boxed warning: Thyroid C-cell tumors observed in rodents; relevance to humans unknown. Contraindicated in patients with personal or family history of medullary thyroid carcinoma or MEN2.
Contraindications: MTC/MEN2; history of serious hypersensitivity to tirzepatide or any excipient.
Warnings/precautions: Acute pancreatitis, hypoglycemia (especially with concomitant insulin/sulfonylurea), acute kidney injury, severe GI disease (gastroparesis), diabetic retinopathy (rapid improvement in glycemic control), hypersensitivity, cholelithiasis/cholecystitis, suicidal ideation/behavior.
Human-study signals
GI adverse events (nausea, diarrhea, vomiting) most common, dose- and titration-dependent.
Gallbladder-related events (cholelithiasis, cholecystitis) increased vs An inactive comparator used in a controlled study. 定义来源: Neutral gloss; usage context: Evidence grading methodology · 术语表 in SURMOUNT.
Heart rate increase of 2–4 bpm observed.
Unknowns and product-quality risks
Long-term (≥5 year) safety data not yet published.
Carcinogenicity signal from rodent thyroid C-cell tumors not resolved.
Data on compounding quality variability are not available.
Interactions and special populations
Drug–drug: Delays gastric emptying, potentially reducing absorption of oral medications. Monitor oral contraceptives and drugs requiring rapid GI absorption.
Pregnancy: Not recommended; no adequate human data. Weight loss offers no benefit and may cause fetal harm.
Lactation: No data on presence in human milk.
Pediatric: Approved for T2D age ≥10 (SURPASS-PEDS).
Renal/hepatic impairment: No dose adjustment; limited data in severe impairment.
Regulatory, compounding, and sport notes
FDA: Approved as Mounjaro (T2D) and Zepbound (weight management, OSA).
EMA: Approved for T2D and weight management.
MHRA: Approved.
WADA: Tirzepatide is not prohibited, but its markers are included in the 2026 Monitoring Program in- and out-of-competition. Monitoring is not prohibition. See the WADA and sport regulation brief.
Compounding: FDA has issued warnings about counterfeit and compounded tirzepatide.
Evidence gaps
No long-term (≥5-year) safety or cardiovascular outcome data have been published. Direct comparisons to semaglutide 2.0 mg and the newest incretin triple agonists are absent.
Real-world persistence and adherence data are emerging but not yet systematically reviewed. The clinical significance of the rodent C-cell tumor signal remains unresolved.
Search notes
Databases and registries: FDA Drugs@FDA, DailyMed, ClinicalTrials.gov, PubMed, EMA public assessment reports.
Search terms: "tirzepatide", "LY3298176", "Mounjaro", "Zepbound", "SURPASS", "SURMOUNT", "SURMOUNT-OSA", "SURPASS-CVOT".
Last searched: 2026-08-06.
Inclusion emphasis: FDA-approved labeling, pivotal Phase 3 trials, published peer-reviewed primary reports.
Sources
FDA. Mounjaro (tirzepatide) prescribing information. Revised Jun 2024. DailyMed. Accessed 2026-08-06. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d2d7da5d-ad07-4228-955f-cf7e355c8cc0
FDA. Zepbound (tirzepatide) prescribing information. Revised Jun 2024. DailyMed. Accessed 2026-08-06. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=487cd7e7-434c-4925-99fa-aa80b1cc776b
Frias JP, Davies MJ, Rosenstock J, et al. Tirzepatide versus semaglutide once weekly in patients with type 2 diabetes (SURPASS-2). N Engl J Med. 2021;385(6):503–515. DOI: 10.1056/NEJMoa2107519. PMID: 34170647. https://doi.org/10.1056/NEJMoa2107519
Jastreboff AM, Aronne LJ, Ahmad NN, et al. Tirzepatide once weekly for the treatment of obesity (SURMOUNT-1). N Engl J Med. 2022;387(3):205–216. DOI: 10.1056/NEJMoa2206038. PMID: 35658024. https://doi.org/10.1056/NEJMoa2206038
Malhotra A, Grunstein RR, Fietze I, et al. Tirzepatide for the treatment of obstructive sleep apnea and obesity (SURMOUNT-OSA). N Engl J Med. 2024;391(13):1193–1205. DOI: 10.1056/NEJMoa2404881. PMID: 38985183. https://doi.org/10.1056/NEJMoa2404881
ClinicalTrials.gov. SURPASS-CVOT (NCT04255433). Updated 2025-12. Accessed 2026-08-06. https://clinicaltrials.gov/ct2/show/NCT04255433
FDA. Mounjaro (tirzepatide), NDA 215866/S-039 supplement approval letter: expansion to pediatric patients aged 10 years and older with type 2 diabetes. 2025. https://www.accessdata.fda.gov/drugsatfda_docs/appletter/2025/215866Orig1s039ltr.pdf
WADA. 2026 Monitoring Program. https://www.wada-ama.org/en/resources/monitoring-program