
Bottom line
GHRP-2 (pralmorelin) is a synthetic hexapeptide ghrelin-receptor agonist. It received regulatory approval in Japan in 2004 as a diagnostic agent for growth hormone deficiency. A separate 48-week, randomized intranasal-treatment trial in 126 children found no significant improvement in growth despite increasing GH secretion; that treatment study was not the basis for the diagnostic evidence summarized below. Human pharmacology studies report that GHRP-2 can also affect ACTH, cortisol, and prolactin.
Identity and composition
| Field | Verified information |
|---|---|
| Preferred name | GHRP-2 (Pralmorelin) |
| Key aliases | KP-102, GPA-748, Growth Hormone Releasing Peptide-2, pralmorelin |
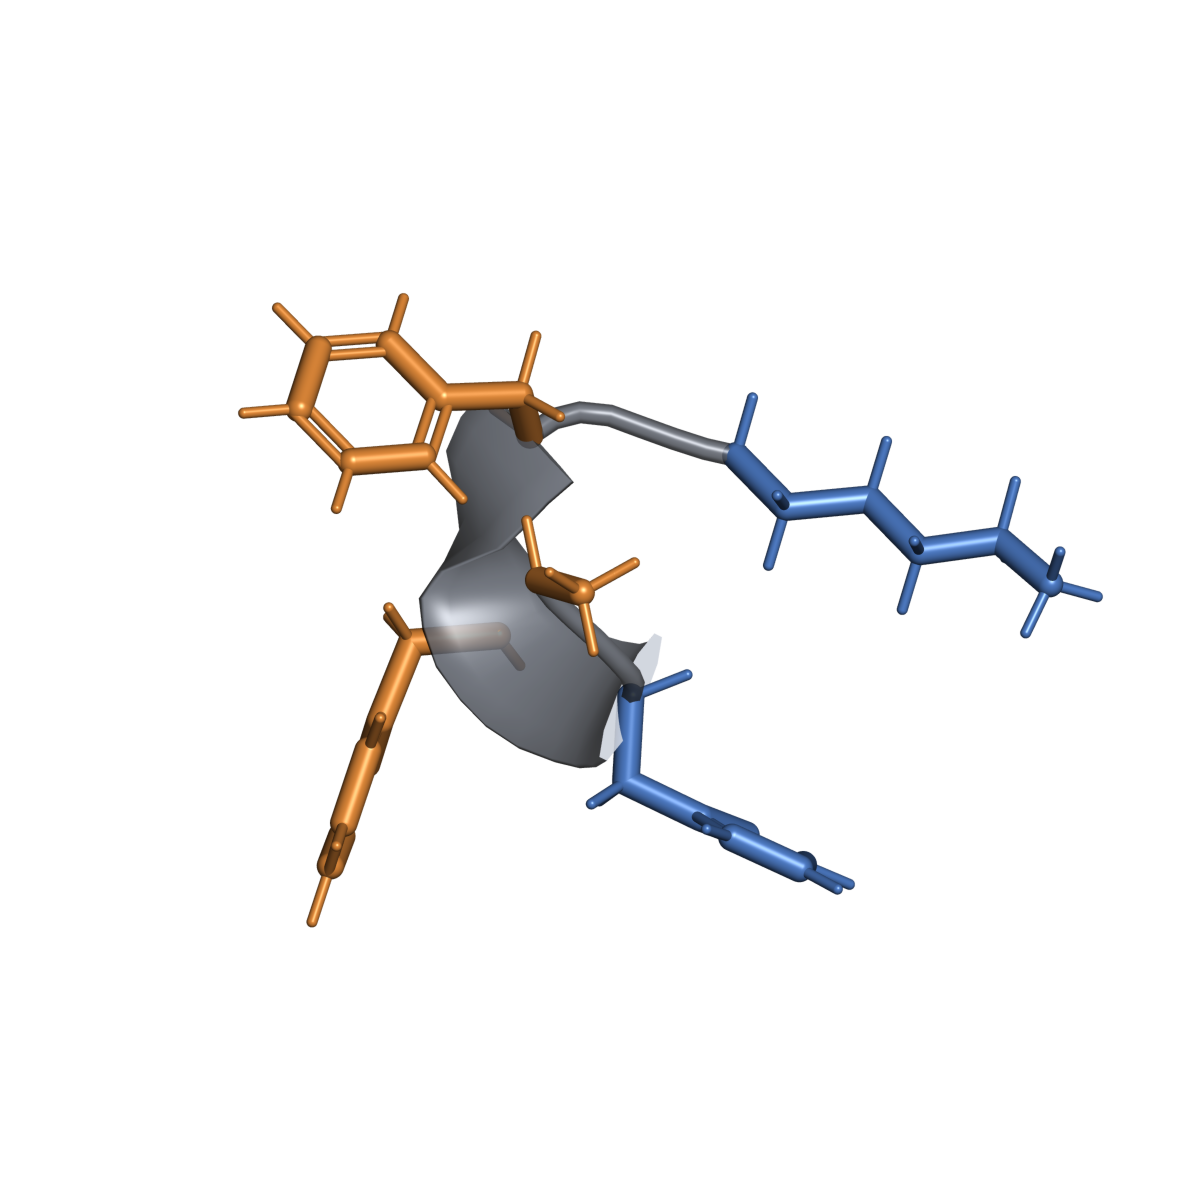
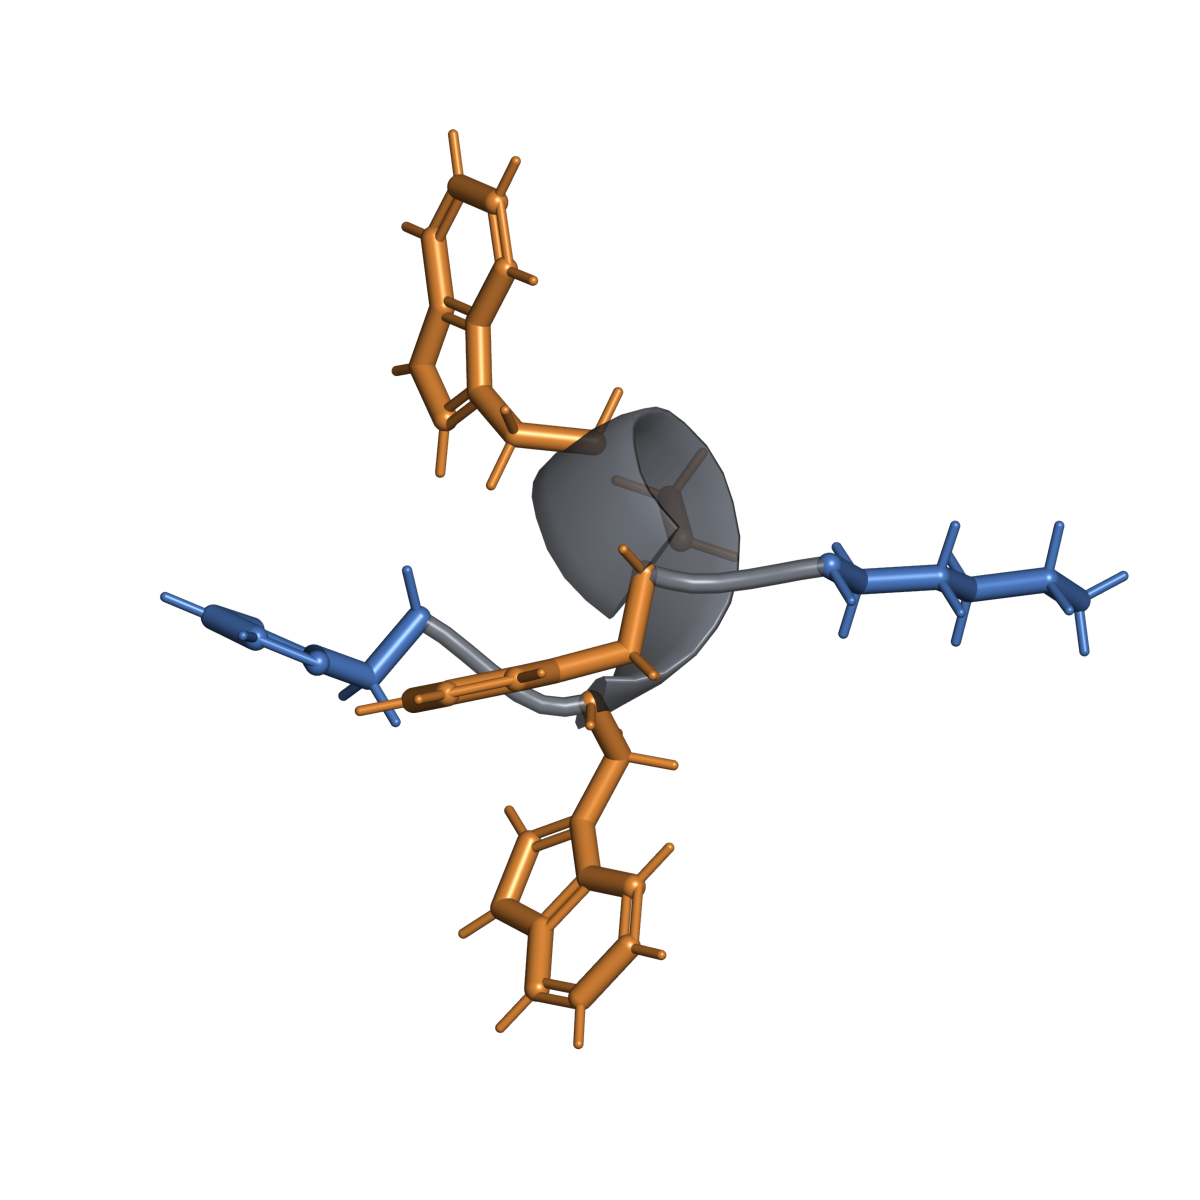
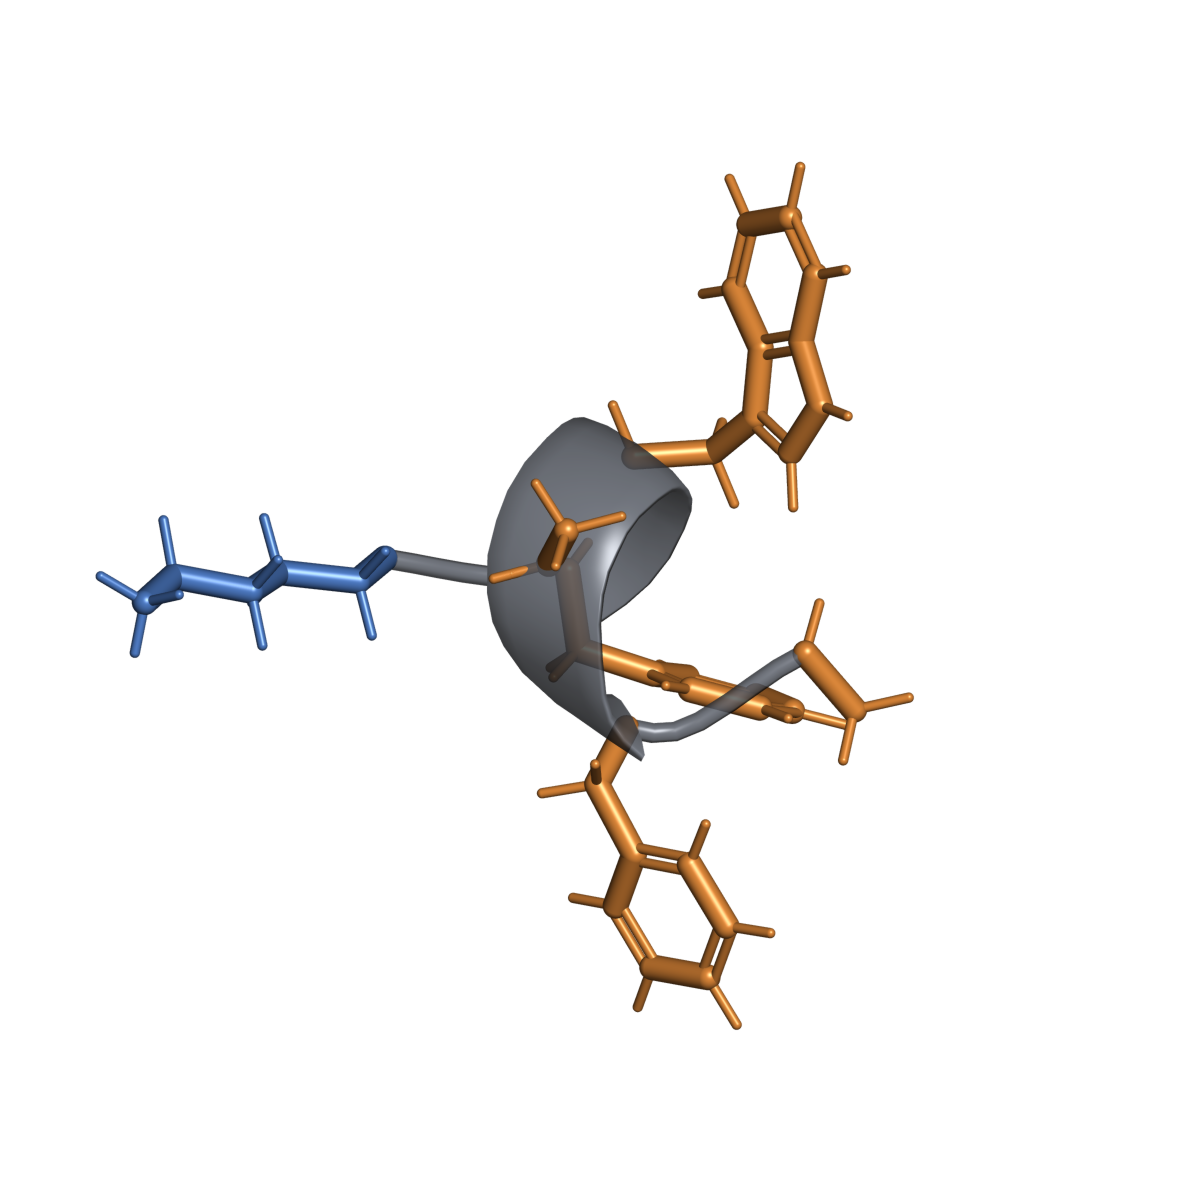
| Molecular/sequence identity | Hexapeptide: D-Ala-D-2-Nal-Ala-Trp-D-Phe-Lys-NH2 |
| Modifications/form | D-amino acids at positions 1, 2, and 5 confer metabolic stability; D-2-naphthylalanine (D-2-Nal) at position 2 enhances binding affinity |
| Stable identifiers | The record number of a compound in PubChem, the atlas's primary structure-asset source. A registry record or depiction does not authenticate a commercial sample. 定义来源: Identity and structure assets methodology · 术语表: 6918245; CAS: 158861-67-7; MW ~818 Da |
| Identity caveats | Not to be confused with GHRP-6 (His-D-Trp-Ala-Trp-D-Phe-Lys-NH2, ~873 Da). Assay-specific potency comparisons should not be converted into human-dose equivalence. |
Development and approval status
| Jurisdiction | Status and indication | Product/source | As of |
|---|---|---|---|
| Japan (PMDA) | Approved 2004 for diagnostic testing of GH deficiency | Pralmorelin (Kaken Pharmaceutical) | 2026-08-06 |
| US (FDA) | No approved indication; development discontinued | — | 2026-08-06 |
| EU (EMA) | No marketing authorization | — | 2026-08-06 |
- UNITED STATES
- US (FDA): No approved indication; development discontinued
- EU/EEA
- EU (EMA): No marketing authorization
- UNITED KINGDOM
- No UNITED KINGDOM row is present in the source status table
- OTHER DOCUMENTED
- Japan (PMDA): Approved 2004 for diagnostic testing of GH deficiency
Sport status: Pralmorelin is a prescription diagnostic in Japan. The 2026 WADA Prohibited List explicitly names GHRP-2 (pralmorelin) among GH-releasing peptides in section S2.2.4; it is prohibited at all times. It has been detected in seized nutritional supplements (Thomas et al., Drug Test Anal 2010; PMID: 20878896).
Mechanism and pharmacology
GHRP-2 is an agonist at the ghrelin receptor (GHS-R1a) on pituitary somatotroph cells and can provoke an acute GH response. Human pharmacology studies also report effects on ACTH, cortisol, and prolactin. Route-specific How a substance is absorbed, distributed, metabolized, and eliminated by the body; atlas pages report pharmacokinetic data such as half-life, metabolism, and clearance. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 observations from small studies should not be generalized to unapproved therapeutic use.
Evidence by claim
| Claim/indication | Stage | Grade | Best human evidence | Main result | Important limitations |
|---|---|---|---|---|---|
| GHD diagnosis (adults and children) | Approved (Japan) | A | PMDA product record and 2014 re-examination report; 503 postmarketing cases from 19 institutions, with 502 in the effectiveness analysis | Against clinician diagnosis based on at least two other GH-stimulation agents, the 9 ng/mL criterion for severe GHD had sensitivity 0.853 and specificity 0.885; ROC AUC 0.939 | Japan-specific product and indication; postmarketing comparison was retrospective and does not establish therapeutic use |
| Short stature treatment | Phase II (discontinued) [1] | X | Tanaka et al., 2014; intranasal GHRP-2 in short GHD children | Increased GH secretion but no clinically significant growth promotion | Intranasal route; therapeutic program discontinued |
| GH release (acute pharmacology) | Phase I [1] | C | Pihoker et al., J Clin Endocrinol Metab 1998; ten prepubertal short children | Acute GH response and PK/PD parameters characterized after one Administered into a vein. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 exposure | Pharmacology endpoints only; small, selected pediatric population |
| Food intake/metabolism | Human study | C | Laferrère et al., J Clin Endocrinol Metab 2005; seven lean healthy men | A 270-minute Administered into the tissue layer under the skin. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 infusion increased buffet-meal energy intake by 35.9% versus saline | Acute crossover experiment; small N |
Text alternative for the claim-evidence diagram. Each grade is defined below:
- A — Established for a specific labeled use
- 1 claim: GHD diagnosis (adults and children)
- B — Moderate human evidence
- 0 claims
- C — Preliminary human evidence
- 2 claims: GH release (acute pharmacology); Food intake/metabolism
- D — Preclinical only
- 0 claims
- E — Anecdotal/marketing claim
- 0 claims
- X — Evidence contradicts or does not support the claim
- 1 claim: Short stature treatment
Key studies
| Study | Design/population | Exposure studied | Endpoints and result | Limitations |
|---|---|---|---|---|
| PMDA re-examination report (2014) | Official regulatory reassessment; 503 postmarketing cases from 19 Japanese institutions, 502 in effectiveness analysis | Japan-labeled single diagnostic administration | At the 9 ng/mL severe-GHD criterion, sensitivity was 0.853, specificity 0.885, and ROC AUC 0.939 versus clinician diagnosis using at least two other stimulation agents | Retrospective postmarketing comparison; not a randomized trial or therapeutic study |
| Drugs R&D drug profile (2004); PMID: 15230633 | Secondary, unsigned development-profile article summarizing pralmorelin's pharmacology and then-current development status [1] | Not a primary trial report | Described the diagnostic rationale and reported a 15 mcg/L peak-GH threshold from the development record | Secondary source; published before Japanese approval and should not be cited as the primary multicenter diagnostic trial |
| Pihoker et al., J Clin Endocrinol Metab 1998; PMID: 9543135 | Phase I PK/PD; ten prepubertal short children (nine boys and one girl; mean age 7.7 years) [1] | One 1 mcg/kg Administered into a vein. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 exposure over 1 minute | Terminal The time for the amount of a substance in the body to fall by half. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 0.55 hours; GH reached maximum concentration at 0.42 hours | Pharmacology study only; small, selected pediatric population |
| Tanaka et al., Clin Pediatr Endocrinol 2014; PMID: 25148835 | Phase II; short children with GHD [1] | Intranasal GHRP-2 spray | Increased GH but no significant height velocity improvement | Therapeutic program discontinued |
| Laferrère et al., J Clin Endocrinol Metab 2005; PMID: 15699539 | Randomized within-subject comparison; seven lean healthy men [1] | Administered into the tissue layer under the skin. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 infusion at 1 mcg/kg/hour for 270 minutes | Food intake increased 35.9% versus saline; serum GH also increased | Acute setting only; small N; not a therapeutic dose-finding study |
Dose and administration evidence
Approved labeled regimen
The label summary below is product-, indication-, and jurisdiction-specific; consult the full current label and a licensed clinician/pharmacist.
Japan-approved diagnostic exposure (PMDA): 2 mcg/kg by slow Administered into a vein. 定义来源: Neutral gloss; usage context: Routes, devices, and absorption primer · 术语表 injection for ages 4–17 years, capped at 100 mcg; 100 mcg by slow IV injection for adults, administered fasting. A peak GH cutoff of 16 ng/mL is used for children; 9 ng/mL for adults. This is a single-administration diagnostic test for GH deficiency — not a therapeutic regimen and not guidance for self-administration.
Studied regimens (not recommendations)
No established or recommended human dose. This sentence concerns therapeutic and other unapproved use; it does not erase the separate Japan-specific, single-administration diagnostic label above. Published nontherapeutic pharmacology studies used protocol-specific exposures under research oversight; they do not establish a therapeutic regimen.
What is not established
Effective therapeutic dose for any non-diagnostic indication
Safety or efficacy of chronic daily administration
Dose finding for body composition or performance claims
Safety
Established label risks
The PMDA re-examination report recorded no adverse drug reactions among 503 postmarketing cases, while the preapproval Japanese trials recorded adverse drug reactions in 86 of 227 participants (37.9%), most commonly borborygmi, feeling hot, sweating, and increased white-blood-cell count. These product-specific diagnostic data do not establish chronic-use safety.
Human-study signals
At higher or repeated doses, GHRP-2 can elevate cortisol and prolactin. Mild injection-site reactions, transient flushing, and increased appetite have been reported.
Unknowns and product-quality risks
Long-term safety (beyond single/diagnostic administration) is not established. No Phase III therapeutic safety data exist. Research-grade material is unregulated.
Interactions and special populations
No formal drug-interaction studies. Diagnostic use should avoid concomitant GH-suppressing medications.
Regulatory, compounding, and sport notes
Pralmorelin is a prescription diagnostic in Japan. The 2026 The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. 定义来源: WADA and sport regulation brief · 术语表 Prohibited List explicitly names GHRP-2 (pralmorelin) among GH-releasing peptides in section S2.2.4; it is prohibited at all times. It has been detected in seized nutritional supplements (Thomas et al., Drug Test Anal 2010; PMID: 20878896).
Evidence gaps
No Phase III therapeutic efficacy trial
No long-term safety data beyond diagnostic single-dose use
No adequate human body-composition data
No studies in women for most endpoints
No approved therapeutic indication outside Japan
Search notes
Databases and registries: PubMed, ClinicalTrials.gov, PMDA (Japan), FDA Drugs@FDA
Search terms: "GHRP-2", "pralmorelin", "KP-102", "growth hormone releasing peptide 2"
Last searched: 2026-08-06
Inclusion emphasis: Human studies; regulatory documents; primary peer-reviewed data
Sources
Drugs R&D. Pralmorelin: GHRP 2, GPA 748, growth hormone-releasing peptide 2, KP-102 D, KP-102 LN. 2004;5(4):236-239. PMID: 15230633. PubMed classifies this unsigned article as a review; it is a development profile, not the primary multicenter diagnostic trial report. https://pubmed.ncbi.nlm.nih.gov/15230633/
Pihoker C et al. Pharmacokinetics and pharmacodynamics of GHRP-2: a phase I study in children. J Clin Endocrinol Metab. 1998;83(4):1168-1172. https://pubmed.ncbi.nlm.nih.gov/9543135/
Tanaka T et al. Intranasal GHRP-2 in short children with GH deficiency. Clin Pediatr Endocrinol. 2014;23(4). https://pubmed.ncbi.nlm.nih.gov/25148835/
Laferrère B et al. Growth hormone-releasing peptide-2 (GHRP-2), like ghrelin, increases food intake in healthy men. J Clin Endocrinol Metab. 2005;90(2):611-614. PMID 15699539. https://pubmed.ncbi.nlm.nih.gov/15699539/
Thomas A et al. Identification of GHRP-2 in a nutritional supplement. Drug Test Anal. 2010;2(3):144-148. https://pubmed.ncbi.nlm.nih.gov/20878896/
WADA. 2026 Prohibited List, section S2.2.4. https://www.wada-ama.org/sites/default/files/2025-09/2026list_en_final_clean_september_2025.pdf
PubChem CID 6918245. https://pubchem.ncbi.nlm.nih.gov/compound/6918245
Pharmaceuticals and Medical Devices Agency. GHRP Kaken 100 (pralmorelin hydrochloride), current product information. https://www.pmda.go.jp/PmdaSearch/rdDetail/iyaku/7223407D2023_1?user=1
Pharmaceuticals and Medical Devices Agency. Re-examination report for GHRP Kaken 100 (approved indication and labeled diagnostic administration). https://www.pmda.go.jp/drugs_reexam/2014/P201400051/20002200_21600AMZ00573_A100_1.pdf