
Bottom line
Synthetic GHRH analog approved for reduction of visceral adipose tissue (VAT) in HIV-infected adults with lipodystrophy. NOT indicated for weight loss or for improving ART compliance. The current US labels specify Egrifta WR 1.28 mg daily from its 11.6-mg single-patient multidose vial and Egrifta SV 1.4 mg daily from its 2-mg vial. The products are not substitutable.
Identity and composition
| Field | Verified information |
|---|---|
| Preferred name | Tesamorelin |
| Key aliases | Egrifta, Egrifta SV, Egrifta WR, TH9507 |
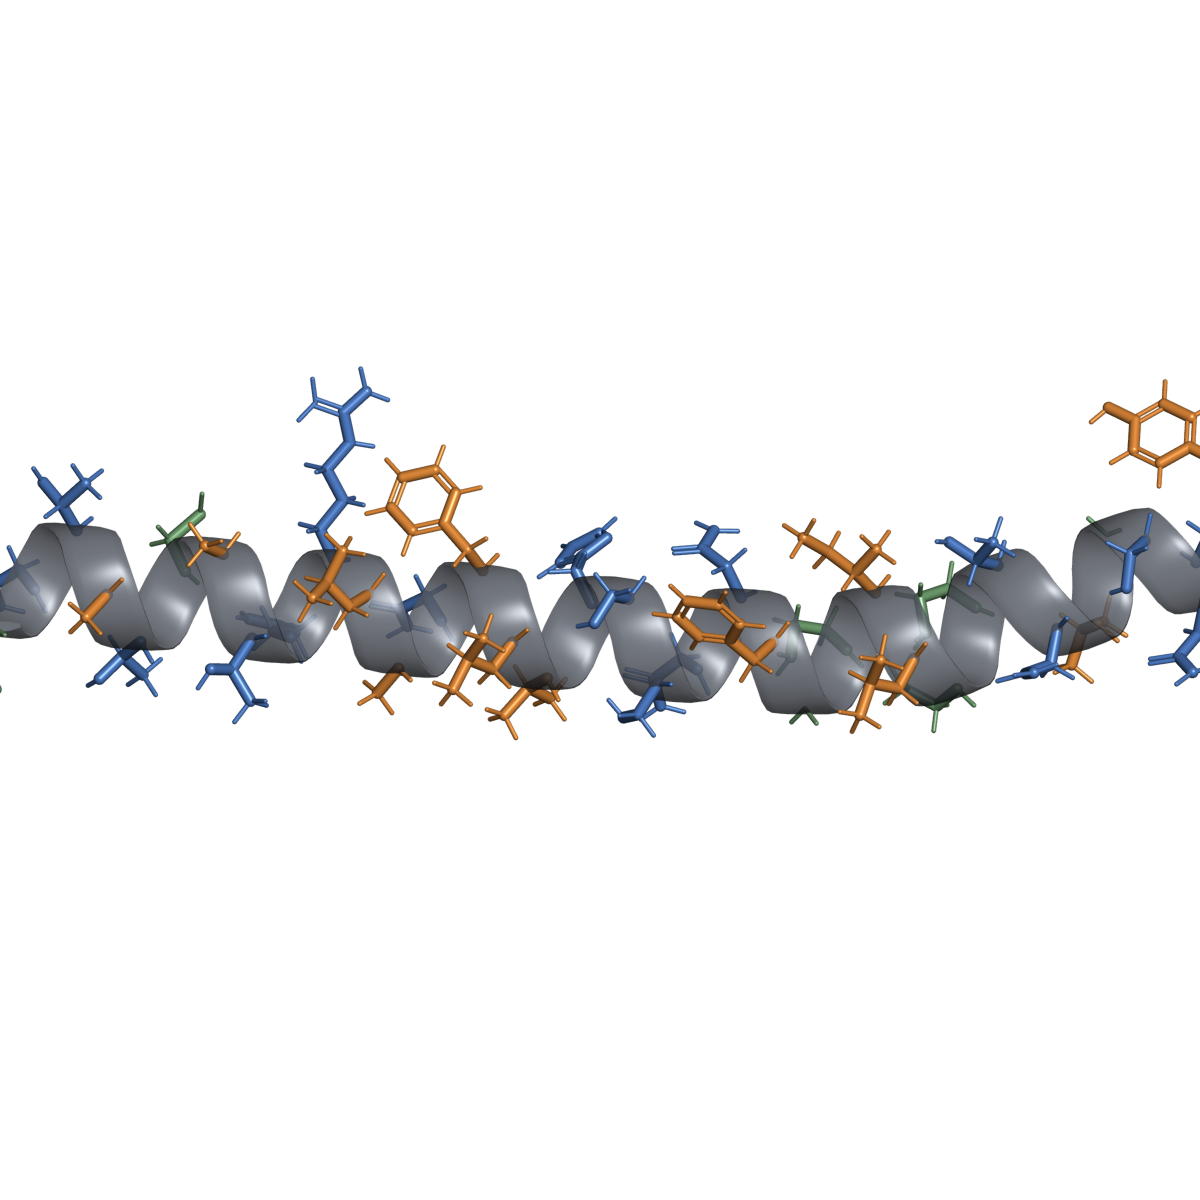
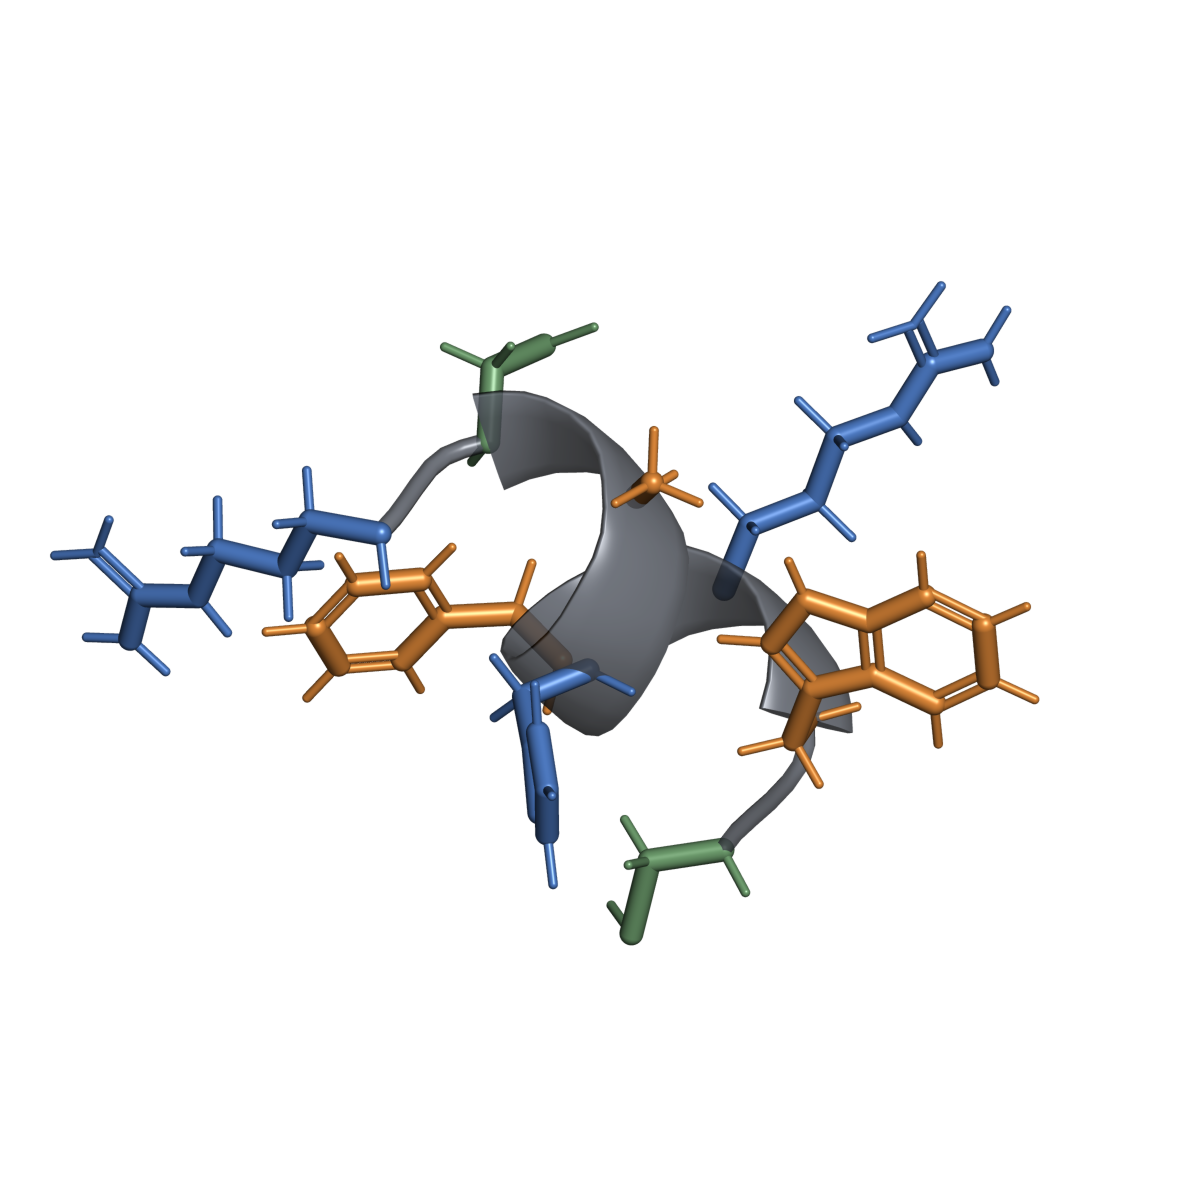
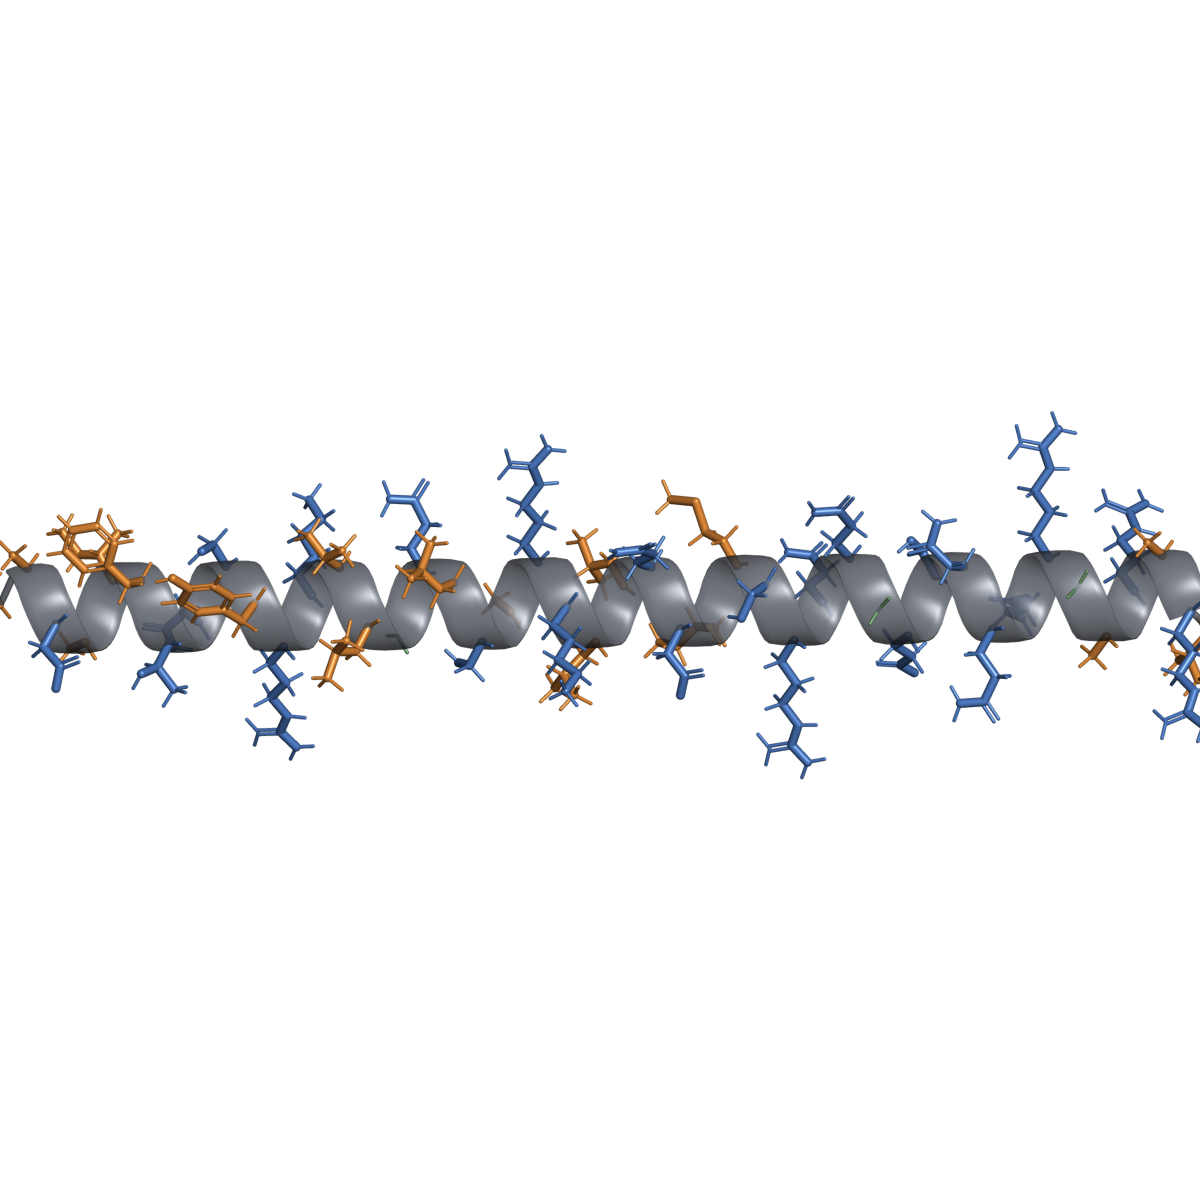
| Molecular/sequence identity | YADAIFTNSYRKVLGQLSARKLLQDIMSRQQGESNQERGARARL-NH2 (44 amino acids; synthetic human GHRH(1–44)-NH2 with a hexenoyl moiety at the N-terminus) |
| Modifications/form | C-terminal amide; N-terminus modified with trans-3-hexenoyl group |
| Stable identifiers | The record number of a compound in PubChem, the atlas's primary structure-asset source. A registry record or depiction does not authenticate a commercial sample. Источник определения: Identity and structure assets methodology · Глоссарий: 16137828; CAS 866933-46-4; WHO ATC H01AC06; DrugBank DB06232; USAN: tesamorelin |
| Identity caveats | The legacy Egrifta 1-mg/vial formulation differs from the currently labeled Egrifta SV 2-mg/vial and Egrifta WR 11.6-mg/vial formulations. The hexenoyl modification enhances metabolic stability compared with native GHRH. |
Development and approval status
| Jurisdiction | Status and indication | Product/source | As of |
|---|---|---|---|
| US (FDA) | Approved Nov 2010 — reduction of excess abdominal fat in HIV-infected adults with lipodystrophy | Current Egrifta SV and Egrifta WR labels (Theratechnologies) | Aug 2026 |
| EU (EMA) | Not approved | — | Aug 2026 |
| Canada (Health Canada) | Approved — same indication | Egrifta (Theratechnologies) | Aug 2026 |
| The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. Источник определения: WADA and sport regulation brief · Глоссарий | Prohibited at all times (GH-releasing factor class WADA Prohibited List class S2 (peptide hormones, growth factors, related substances and mimetics): prohibited at all times, with subsections of materially different scope. Источник определения: WADA and sport regulation brief · Глоссарий) | — | Aug 2026 |
- UNITED STATES
- US (FDA): Approved Nov 2010 — reduction of excess abdominal fat in HIV-infected adults with lipodystrophy
- EU/EEA
- EU (EMA): Not approved
- UNITED KINGDOM
- No UNITED KINGDOM row is present in the source status table
- OTHER DOCUMENTED
- Canada (Health Canada): Approved — same indication
Sport status: Prohibited at all times (GH-releasing factor class S2)
Mechanism and pharmacology
Tesamorelin is a synthetic analog of human growth hormone-releasing hormone (GHRH) that binds to the GHRH receptor on pituitary somatotroph cells, stimulating the pulsatile secretion of An entry with substantial scientific visibility or identity value. Biological rationale and non-human evidence do not establish patient benefit. Источник определения: Scope and selection methodology · Глоссарий GH. The resulting increase in GH and hepatic IGF-1 reduces visceral adipose tissue (VAT) and improves the lipid profile. Unlike rhGH, tesamorelin preserves the pulsatile GH secretion pattern and does not suppress endogenous somatostatin tone.
Evidence by claim
| Claim/indication | Stage | Grade | Best human evidence | Main result | Important limitations |
|---|---|---|---|---|---|
| VAT reduction in HIV lipodystrophy | Approved | A | Two 26-wk A study in which participants are assigned to the study material or a comparator by chance. Источник определения: Neutral gloss; usage context: Evidence grading methodology · Глоссарий (n=816 pooled), 26-wk A study in which participants and investigators know what is administered. Источник определения: Neutral gloss; usage context: Evidence grading methodology · Глоссарий extension | VAT reduced by 15–17% by CT vs An inactive comparator used in a controlled study. Источник определения: Neutral gloss; usage context: Evidence grading methodology · Глоссарий (~2–4%); VAT remained reduced in extension | Long-term CV benefit not established; GH/IGF-1 exposure a theoretical safety concern |
| Reduction of non-alcoholic fatty liver disease (NAFLD) in HIV | Phase 2 (exploratory) | C | Small 6-mo pilot in HIV+ with NAFLD (n=40) | Decreased liver fat by MRI-PDFF (~30% relative reduction) | Small; no histology; not replicated in larger trial |
| Fat reduction in non-HIV populations | No adequate study | X | No controlled trials | Not indicated | FDA-approved indication explicitly limited to HIV lipodystrophy |
- AУровень A: Установлен для конкретного зарегистрированного применения
- BУровень B: Умеренные данные на людях
- CУровень C: Предварительные данные на людях
- DУровень D: Только доклинические
- EУровень E: Анекдотическое/маркетинговое утверждение
- XУровень X: Данные противоречат утверждению или не подтверждают его
Text alternative for the claim-evidence diagram. Each grade is defined below:
- A — Established for a specific labeled use
- 1 claim: VAT reduction in HIV lipodystrophy
- B — Moderate human evidence
- 0 claims
- C — Preliminary human evidence
- 1 claim: Reduction of non-alcoholic fatty liver disease (NAFLD) in HIV
- D — Preclinical only
- 0 claims
- E — Anecdotal/marketing claim
- 0 claims
- X — Evidence contradicts or does not support the claim
- 1 claim: Fat reduction in non-HIV populations
Key studies
| Study | Design/population | Exposure studied | Endpoints and result | Limitations |
|---|---|---|---|---|
| Falutz J, et al. (NEJM 2007) — Phase 3 | Two 26-wk A study in which participants are assigned to the study material or a comparator by chance. Источник определения: Neutral gloss; usage context: Evidence grading methodology · Глоссарий, HIV+ adults with lipodystrophy (n=816) | Tesamorelin 2 mg Administered into the tissue layer under the skin. Источник определения: Neutral gloss; usage context: Routes, devices, and absorption primer · Глоссарий qd vs An inactive comparator used in a controlled study. Источник определения: Neutral gloss; usage context: Evidence grading methodology · Глоссарий | VAT reduction 15–17% by CT (p<0.001); triglycerides improved | No CV outcomes; 24% discontinuation due to IGHCs cause attrition |
| Stanley TL, et al. (AIDS 2009) — 26-wk extension | A study in which participants and investigators know what is administered. Источник определения: Neutral gloss; usage context: Evidence grading methodology · Глоссарий extension of Phase 3 (n=489) | Tesamorelin 2 mg SC qd continued | VAT reduction sustained; IGF-1 returned to baseline after discontinuation | Open-label; no control group |
| Fourman LT, et al. (CID 2021) — NAFLD pilot | 6-mo open-label, HIV+ NAFLD (n=40) | Tesamorelin 2 mg SC qd | Liver fat reduction by MRI-PDFF 30% relative; ALT decreased | No confirmatory Phase 3; small |
Dose and administration evidence
Approved labeled regimen
The label summary below is product-, indication-, and jurisdiction-specific; consult the full current label and a licensed clinician/pharmacist.
The entries summarize the cited US FDA Egrifta labels for the approved HIV-associated lipodystrophy indication.
Egrifta SV: 1.4 mg Administered into the tissue layer under the skin. Источник определения: Neutral gloss; usage context: Routes, devices, and absorption primer · Глоссарий once daily from the 2-mg/vial formulation.
Egrifta WR (approved Apr 2025): 1.28 mg SC once daily from the 11.6-mg single-patient-use multidose vial.
Egrifta SV and Egrifta WR are NOT interchangeable or substitutable. Different vial sizes, The product-specific pharmaceutical process by which a lyophilized (freeze-dried) solid returns to a liquid dispersion. It is not evidence that the resulting material is suitable for administration. Источник определения: What reconstitution means primer · Глоссарий procedures, deliverable doses, and administration devices.
Subcutaneous administration into the abdomen with site rotation per label instructions.
Studied regimens (not recommendations)
Same daily dose used across all Phase 3 trials (2 mg SC).
No data for higher or less frequent dosing.
What is not established
Not indicated for weight loss, improved ART compliance, idiopathic short stature, frailty, or any non-HIV-related fat redistribution.
Safety
Established label risks
Contraindication: Active malignancy; active pregnancy.
Warnings/precautions: Elevated IGF-1 (risk monitor; long-term theoretical malignancy risk); glucose intolerance (GH effect); injection-site reactions (up to 35%); arthralgia (17%); peripheral edema; carpal tunnel syndrome.
No boxed warning on current label but malignancy precaution is prominent.
Human-study signals
Hypersensitivity reactions, antibody formation (19% developed anti-tesamorelin antibodies; did not affect efficacy).
Small increase in fasting glucose (mean +2 mg/dL).
Unknowns and product-quality risks
Long-term CV safety beyond 2 years not established.
Theoretical risk of neoplastic progression (GH/IGF-1 axis).
Switching between Egrifta and Egrifta WR formulations may require dose adjustment.
Interactions and special populations
Glucose-lowering drugs: tesamorelin may reduce insulin sensitivity; monitor glucose.
Concomitant estrogen may reduce IGF-1 response; concomitant testosterone may augment.
Not studied in severe renal or hepatic impairment.
Pregnancy Category X (contraindicated).
Regulatory, compounding, and sport notes
FDA-approved — no REMS program. Malignancy monitoring is a label precaution, not a REMS requirement.
Approved in Canada (Health Canada) but not in the EU.
The World Anti-Doping Agency; its Prohibited List classifies many peptides as prohibited substances in sport. Источник определения: WADA and sport regulation brief · Глоссарий: prohibited at all times (in and out of competition) as a GH-releasing factor (category WADA Prohibited List class S2 (peptide hormones, growth factors, related substances and mimetics): prohibited at all times, with subsections of materially different scope. Источник определения: WADA and sport regulation brief · Глоссарий).
Evidence gaps
No CVOT demonstrating reduced cardiovascular events with VAT reduction.
No confirmatory Phase 3 for hepatic outcomes (NAFLD/NASH).
Long-term (5+ year) safety data limited.
Comparative effectiveness vs lifestyle intervention not studied.
Search notes
Databases and registries: DailyMed (Egrifta WR label), ClinicalTrials.gov, PubMed, FDA, Health Canada.
Search terms: "tesamorelin" OR "Egrifta" OR "TH9507" OR "Egrifta WR".
Last searched: 2026-08-06.
Inclusion emphasis: FDA label, pivotal Phase 3 trials, post-market data.
Sources
Egrifta WR (tesamorelin 11.6-mg/vial formulation) prescribing information. FDA/DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=839334d3-8c1d-4c26-9036-2ab524a6ea75
Egrifta SV (tesamorelin 2-mg/vial formulation) prescribing information. FDA/DailyMed. https://dailymed.nlm.nih.gov/dailymed/lookup.cfm?setid=3d783378-b02d-4f19-99dd-0fc91a042224&version=8
Falutz J, et al. Effect of tesamorelin on visceral adipose tissue in HIV-infected patients with abdominal fat accumulation. N Engl J Med. 2007;357(23):2359–2370. DOI: 10.1056/NEJMoa072375. PMID: 18057338. https://doi.org/10.1056/NEJMoa072375
Stanley TL, et al. Long-term safety and effects of tesamorelin, a growth hormone-releasing factor analogue, in HIV patients with abdominal fat accumulation. AIDS. 2008;22(14):1717–1725. DOI: 10.1097/QAD.0b013e32830a5058. PMID: 18690162. https://doi.org/10.1097/QAD.0b013e32830a5058
Fourman LT, et al. Tesamorelin for NAFLD in HIV+ adults: a pilot study. Clin Infect Dis. 2021;73(7):e1450–e1457. https://doi.org/10.1093/cid/ciaa1569
DrugBank DB06232 — Tesamorelin. https://go.drugbank.com/drugs/DB06232. Accessed 2026-08-06.
WADA Prohibited List 2026. World Anti-Doping Agency. https://www.wada-ama.org/en/prohibited-list. Growth-hormone-releasing factors are prohibited at all times (category S2).